because prevention is better than cure.

because prevention is better than cure.

Mini Cart 0

Your cart is empty.

Mini Cart 0

Your cart is empty.

Amyloid isn’t Alzheimer’s – How NOT to Study a Disease

Amyloid isn’t Alzheimer’s – How NOT to Study a Disease

by Patrick Holford
alzheimers drugs

Alzheimer’s disease has, for decades, been framed primarily as a problem of amyloid plaques building up in the brain.

It is a compelling idea. It is measurable, visible on brain scans, and has shaped billions in research funding and drug development. There’s just one problem.

It doesn’t adequately explain what we see in people.

Many individuals with significant amyloid in their brains remain cognitively normal. Others develop clear dementia with little or no amyloid present (1). Treatments that successfully reduce amyloid have, at best, produced only modest effects on slowing decline, with no meaningful reversal of symptoms (2).

Amyloid is associated with Alzheimer’s disease, but association is not the same as causation.

And that distinction changes everything.

This growing tension between theory and evidence is explored in depth by neurobiologist Karl Herrup in How Not to Study a Disease, where he challenges how the field has come to define and pursue Alzheimer’s.

Some people develop increasingly severe cognitive decline as they age. This affects roughly one in ten older adults. We call this dementia. In some cases, brain scans show clear shrinkage in key regions, particularly the medial temporal lobe, which is then used to diagnose Alzheimer’s disease. So we have two observable features: a decline in cognitive function and measurable loss of brain tissue.

The question that follows is simple, but critical.

What is actually causing this process?

What causes Alzheimer’s?

Amyloid has long been positioned as the answer. Yet the evidence tells a more complicated story.

A significant proportion of older adults have amyloid plaques in their brains and remain cognitively normal. At the same time, some individuals with clear dementia show little or no amyloid pathology. Amyloid is associated with Alzheimer’s, but that is not the same as being the cause.

If amyloid were the primary driver, then reducing it should meaningfully change the course of the disease. However, interventions designed to reduce amyloid have consistently lowered amyloid burden in the brain, yet produced, at best, modest effects on slowing decline, often measured as very small changes on cognitive scales. There has been no meaningful reversal of symptoms. In some cases, safety concerns have emerged, including brain bleeding and swelling.

Recent large-scale evidence (6) now reinforces this point. A 2026 Cochrane review concluded that although anti-amyloid monoclonal antibodies can remove amyloid from the brain, this does not appear to translate into clinically meaningful effects for people with mild cognitive impairment or mild dementia due to Alzheimer’s disease, while increasing the risk of amyloid-related imaging abnormalities.

From a scientific perspective, this adds to an already substantial body of evidence suggesting that amyloid accumulation, on its own, does not explain the disease process. It may be part of the picture, but it is not the engine driving it.

And yet, the field has remained heavily focused on this single pathway.

When a hypothesis becomes a lens

Research tends to follow what is measurable, fundable, and already established. Over time, this can narrow the lens rather than expand it.

Amyloid has become that lens. As Karl Herrup argues in his book, once a hypothesis becomes dominant, it can begin to shape not just what is studied, but how results are interpreted and what gets funded next.

The result is that vast resources have been invested in understanding and modifying amyloid biology, while other avenues have received comparatively less attention. We have learned a great deal about amyloid itself, but we are not significantly closer to preventing or reversing the condition that matters most to patients, which is cognitive decline.

This is not unusual in science. Once a model becomes dominant, it shapes the direction of funding, research questions, and even how people interpret results.
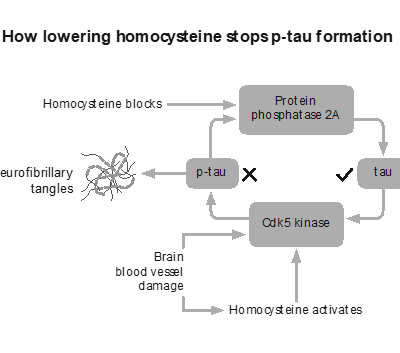
Fig. 1. How lowering homocysteine stops p-tau formation.

A similar pattern is now emerging with another biomarker, p-tau.

Tau is a normal protein that, under certain conditions, becomes altered and associated with the tangles seen in Alzheimer’s pathology. Higher levels of p-tau are linked with increased risk, but again, association does not establish causation. Many individuals have elevated levels without clinical symptoms.

As with amyloid, the risk is that a marker becomes mistaken for the mechanism.

What does influence the disease process?

This is where the picture becomes more interesting.

There are factors that sit upstream of both amyloid and tau, influencing the environment in which brain cells function or fail. One of the most studied is homocysteine, a marker of methylation and B vitamin status.

Unlike amyloid, intervention trials have shown that homocysteine influences outcomes. In the VITACOG study, lowering elevated homocysteine with targeted B vitamins significantly slowed the rate of brain atrophy in individuals with mild cognitive impairment, with corresponding effects on cognitive decline. This is much closer to what we would describe as a disease-modifying effect (3,4). It also raises questions explored in Apparently healthy but diagnosed with Alzheimer’s about whether current diagnostic models are identifying true disease drivers or simply biomarkers.

That does not mean homocysteine is the only cause. It is one piece of a larger system. But it illustrates an important point. When you influence the underlying biology of the brain, rather than a downstream marker, you begin to see meaningful change.

A systems problem, not a single cause

Alzheimer’s does not behave like a single-cause disease.

It is better understood as the result of multiple interacting processes. These include inflammation, oxidative stress, insulin resistance, mitochondrial dysfunction, and impaired methylation, among many others (5). Each of these affects how brain cells are built, maintained, and powered.

Individually, they may not be sufficient to cause disease. Together, they can create the conditions in which the brain becomes vulnerable.

This is closer to how we understand most chronic conditions. Not as a single fault, but as a convergence of pressures that eventually exceed the system’s ability to compensate. A more useful way to think about it is not as one switch flipping, but as several dials turning in the wrong direction at the same time.

Why this matters

If we continue to focus primarily on downstream markers such as amyloid or p-tau, we risk missing the broader picture.

If instead we look at the upstream drivers, the factors that influence brain structure, function, and energy supply, we open up a different set of possibilities. Not just for treatment, but for prevention.

These are not fringe ideas. They are part of a growing shift in how Alzheimer’s is being understood, questioned, and re-examined. Researchers like Karl Herrup are helping to bring that conversation into the open, challenging long-held assumptions and asking more useful questions about what truly drives the disease.

It’s a conversation that is only just beginning to reach wider audiences.

This is exactly what we’ll be exploring at Alzheimer’s Prevention: New Frontiers conference, where leading researchers and clinicians will come together to look beyond single-cause models and towards a more complete understanding of brain health and cognitive decline.

Is prevention the real solution?

The prevailing model in medicine has been to identify a single cause and target it with a treatment. That works well for some conditions. It is less suited to complex, multifactorial diseases like Alzheimer’s.

A systems-based approach asks a different question.
What combination of factors leads to decline, and how do we shift that combination in the opposite direction?

This is the approach we take at Food for the Brain. By combining cognitive testing with blood testing and lifestyle information, it becomes possible to see patterns, not just isolated variables. Over time, this allows us to understand what drives resilience as well as risk.

It is likely that we will not find a single primary cause of Alzheimer’s. What we may find is something more useful: a set of modifiable factors that, together, determine whether the brain maintains function or begins to decline.

In that sense, prevention may not just be part of the solution.

It’s the solution.

Find out more with Alzheimer’s: Prevention is the Cure book here

Learn more about our Alzheimer’s Prevention: New Frontiers Conference here.

References
  1. Jack CR Jr, Bennett DA, Blennow K, et al. NIA-AA Research Framework: Toward a biological definition of Alzheimer’s disease. Alzheimers Dement. 2018;14(4):535–562.
  2. van Dyck CH, Swanson CJ, Aisen P, et al. Lecanemab in early Alzheimer’s disease. N Engl J Med. 2023;388:9–21.
  3. de Jager CA, Oulhaj A, Jacoby R, et al. Cognitive and clinical outcomes of homocysteine-lowering B-vitamin treatment in mild cognitive impairment. Int J Geriatr Psychiatry. 2012;27(6):592–600.
  4. Livingston G, Huntley J, Sommerlad A, et al. Dementia prevention, intervention, and care: 2020 report of the Lancet Commission. Lancet. 2020;396(10248):413–446.
Further info

Homocysteine and Dementia: The Evidence They Don’t Want You to See

Imagine if a simple, well-researched nutrient protocol could prevent cognitive decline in millions of people worldwide. Imagine further that this protocol has been known for years, supported by multiple clinical trials and global experts, yet systematically ignored by the very institutions meant to protect public health. That is precisely the case when it comes to homocysteine, B vitamins, and dementia.

Last year, the UK-based Lancet Commission on Dementia Prevention, Intervention and Care released its third major report, once again omitting any mention of homocysteine as a modifiable risk factor. This was despite direct submissions of evidence and letters from leading scientists demonstrating that lowering homocysteine with B vitamins can slow brain shrinkage and cognitive decline.

Now, in response to this silence, six of the leading dementia researchers, Professors Joshua Miller (Rutgers), David Smith (Oxford), Helga Refsum (Oslo), Jin-Tai Yu (Fudan), Babak Hooshmand (Karolinska), and Andrew McCaddon (Wrexham), have published a powerful rebuttal in the Journal of Alzheimer’s Disease. Many of these experts serve in the Alzheimer’s Prevention Expert Group (APEG) at Food for the Brain.

They wrote:

“In 2018, we published an ‘International Consensus Statement on Homocysteine and Dementia’ in this journal, in which we concluded that elevated plasma total homocysteine is a modifiable risk factor for the development of cognitive decline, dementia, and Alzheimer’s disease (AD) in older persons. (1)

We further stated that intervention trials in elderly people with cognitive impairment show that homocysteine-lowering treatment with B vitamins markedly slows the rate of both wholeand regional brain atrophy, and also slows cognitive decline. We were therefore puzzled as to why the Lancet Commission on Dementia Prevention, Intervention and Care, failed to discuss the possible role of homocysteine and B vitamins in any of their three reports, including the most recent one.” (2)

A Systematic Omission

The UK-based Lancet Commission on Dementia Prevention is meant to objectively consider the evidence on dementia prevention. Yet each edition, despite being sent the relevant papers, has ignored the evidence concerning homocysteine.

Furthermore, it’s expected to uphold the standards for critical debate which allows for experts to question Published findings. That is exactly what these experts did – yet it declined to publish their letter, instead printing a rebuttal from its own Commission while refusing to let readers see the original letter. (3, 4)

The experts wrote to The Lancet again to respond to the Commission’s letter, but their second letter was also rejected. 

Thatetter has now been published in the leading Alzheimer’s journal where the authors finally have their rightful say. It includes the following:

We wish to reply to the Commission and continue the debate with the aim of reaching a common view on homocysteine, B vitamins and dementia. This is an important matter of public health.”

In other words, The Lancet published the ‘case for the defence’ for the exclusion of homocysteine without allowing readers to even read the ‘case for the prosecution’. (5)

So, what was The Lancet’s case against B vitamins? It rested on three criticisms – each of which these leading dementia researchers refute with scientific precision in their recent journal paper.

Criticism 1: Misunderstanding Who Benefited in the VITACOG Trial

The Lancet Commission questioned the relevance of the VITACOG trial, arguing that the results “do not show benefits in populations already consuming B vitamins in their food or through supplements.” But this fundamentally misrepresents the study population.

In the VITACOG trial, participants with mild cognitive impairment were given high doses of B6, B12, and folic acid for two years. The result was a 31% reduction in whole brain shrinkage and significantly slower rate of cognitive decline in those with raised homocysteine (6). In participants with levels above 11.3 μmol/L – the median – both cognitive and clinical improvements were observed. Importantly, key Alzheimer’s-related brain regions shrank seven times more slowly in these individuals (7, 8).

The Lancet Commission implied that participants were already supplementing, but that is incorrect. The study excluded anyone taking more than 300 mcg of folic acid, 3 mg of vitamin B6, or 1.5 mcg of vitamin B12 – doses lower  than those found in many common multivitamins. Only 16 to 20 percent were taking low-dose supplements, while the majority were not.. No one was excluded based on their dietary intake of B vitamins.

The experts respond:“The Commission authors’ comment is analogous to expecting additional drug treatment to provide benefits over and above the benefits being obtained in people already taking a high dose of the drug, which is why it puzzles us.”

Criticism 2: No Benefit in the Hong Kong Trial?

The Commission’s response also cited a Hong Kong trial that reported no benefit of B vitamins over two years in people with mild cognitive impairment (MCI) (9). However, this overlooks several important confounders.

Firstly, 22% of participants were taking aspirin, which the study authors themselves found to impair the effect of B vitamins. This interference has since been confirmed in further research (10).

Secondly, the authors of The Lancet response failed to consider another critical factor: omega-3 status. Numerous studies show that B vitamins only deliver cognitive benefits when omega-3 fatty acid levels are sufficient. The Hong Kong study did not measure or control for omega-3 status, which likely explains the lack of consistent benefit over the two-year period.

Thus, the absence of effect in this trial does not disprove the role of B vitamins.  The experts go on to demonstrate in their article the overwhelming body of evidence –  reported by us – that homocysteine-lowering B vitamins do not work optimally in individuals with low omega-3 status.

Criticism 3: No Benefit in the VITAL Trial in Alzheimer’s Patients?

The Lancet authors also referenced the VITAL trial, which reported no overall cognitive benefit from B vitamins in patients already diagnosed with Alzheimer’s disease (11). But again, this conclusion overlooks key details.

In a subgroup analysis, those in the early stages of Alzheimer’s disease did show significant benefit (12). The authors of the VITAL trial themselves highlighted this in their paper, suggesting that earlier intervention is more effective. This finding aligns with multiple other studies showing that B vitamin treatment is most effective in the pre-dementia stages (13).

Furthermore, participants in the VITAL trial began with an average homocysteine level of 9 μmol/L, which is below the threshold (>10–11 μmol/L) associated with brain atrophy.  It is extremely rare to find a group of people with Alzheimer’s disease that start with such a low homocysteine level.  While the B vitamins did reduce homocysteine further to 7μmol/L, there was no overall cognitive benefit observed. But this is akin to giving painkillers to people who are not in pain and then reporting no change in pain levels. At Food for the Brain, we consider a homocysteine level above 10μmol/L as in need of correction with B vitamins.

There are also concerns about conflicts of interest. The lead author, Paul Aisen, is described as “a consultant to the following pharmaceutical companies involved in the development of potential treatments for Alzheimer’s disease”. with more than a dozen firms listed. These companies would certainly favour a trial designed to fail – especially if it were widely publicised.

Additionally, when an anti-amyloid drug trial for lecanemab was published – now licensed in the US and UK – the names of Paul Aisen and Christopher Van Dyck appeared once again as lead authors. In other words, the paid pharmaceutical consultants, responsible for running the drug trial were also tasked with overseeing a trial – designed to fail – on a competing approach: lowering homocysteine with B vitamins. The conflict of interest here is both clear and concerning.

What Does the Evidence Really Say?

You can read the full expert response published in the Journal of Alzheimer’s Disease here. 

Their conclusion is clear:

“We hope that the Lancet Commission will consider the substantial existing evidence of raised homocysteine as an important risk factor for dementia and the possibility of modifying its harm by supplementation with B vitamins.”

They emphasise that the evidence for B vitamin intervention is as strong – or stronger than –  many of the risk factors the Commission did include in its 2024 report. To continue ignoring the proven impact of homocysteine, and the benefits of lowering it through B vitamins is not merely a scientific oversight –  it is a missed opportunity with major implications for medicine and public health.

Remember, prevention is better than cure, and there is so much you can do to protect your brain health

The perfect time to start? Today.

What Can You Do?

  1. Test your homocysteine (and omega-3 status) TODAY –  especially if you’re over 50 or at risk of cognitive decline. At Food for the Brain, we offer an accurate at-home test kit that reliably measures plasma homocysteine reliably. 

    You can order your single Homocysteine test here or save money and test both omega-3 index and homocysteine (plus other markers) as part of our DRIfT tests here. International shipping available.
  2. Act on your results –  if your level is above 10 μmol/L, supplementation with vitamin B6 (20 mg), methylfolate (400 µg), and vitamin B12 (500 µg) is recommended.
    Read more on supplements and homocysteine here.
  3. Support our mission – become a FRIEND of Food for the Brain! Your donation helps us advance prevention-focused brain health research and education.

    As a Friend, you’ll also gain access to:
    • Monthly group coaching
    • Your personalised brain upgrade programme: COGNITION™
  4. Share the knowledge – public awareness can change public health.
    We need a paradigm shift, and it starts with us.

References

1. Smith AD, Refsum H, Bottiglieri T, et al. Homocysteine and dementia: an international consensus statement. J Alzheimers Dis 2018; 62: 561–570.

2.Livingston G, Huntley J, Liu KY, et al. Dementia prevention, intervention, and care: 2024 report of the Lancet standing Commission. Lancet 2024; 404: 572–628.

3.Miller JW, McCaddon A, Hooshmand B, et al. The Lancet ‘Omission’: Why are  homocysteine and B vitamins missing from the Lancet Commission’s Report on Dementia Prevention, Intervention and Care? https://foodforthebrainorg/lancet-commission-letters/ (2024).

4.Livingston G, Costafreda SG, Kivimaki M, et al. B vitamins and the 2024 Lancet Commission on dementia. Lancet 2025; 405: 623.

5. Miller JW, McCaddon A, Yu J-T, Hooshmand B, Refsum H, Smith AD. Concerning the debate about homocysteine, B vitamins, and dementia. Journal of Alzheimer’s Disease. 2025;0(0). doi:10.1177/13872877251350297

6. Smith AD, Smith SM, de Jager CA, et al. Homocysteine-lowering by B vitamins slows the rate of accelerated brainatrophy in mild cognitive impairment. A randomized controlled trial. PLoS One 2010; 5: e12244.

7. de Jager CA, Oulhaj A, Jacoby R, et al. Cognitive and clinical outcomes of homocysteine-lowering B-vitamin treatment in mild cognitive impairment: a randomized controlled trial. Int J Geriatr Psychiatry 2012; 27: 592–600.

8. Douaud G, Refsum H, de Jager CA, et al. Preventing Alzheimer’s disease-related gray matter atrophy by B-vitamin treatment. Proc Natl Acad Sci U S A 2013; 110: 9523–9528.

9. Kwok T, Wu Y, Lee J, et al. A randomized placebo- controlled trial of using B vitamins to prevent cognitive decline in older mild cognitive impairment patients. ClinNutr 2020; 39: 2399–2405.

10. Wu Y, Smith AD, Refsum H, et al. Effectiveness of B vitamins and their interactions with aspirin in improving cognitive functioning in older people with mild cognitive impairment: pooled post-hoc analyses of two randomized trials. J Nutr Health Aging 2021; 25: 1154–1160.

11. Aisen PS, Schneider LS, Sano M, et al. High-dose B vitamin supplementation and cognitive decline in Alzheimer disease: a randomized controlled trial. JAMA 2008; 300: 1774–1783.

12. Smith AD and Homocysteine RH. B vitamins, and cognitive impairment. Ann Rev Nutr 2016; 36: 211–239.

13. Chen H, Liu S, Ge B, et al. Effects of folic acid and vitamin B12 supplementation on cognitive impairment and inflammation in patients with Alzheimer’s disease: a randomized, single-blinded, placebo-controlled trial. J Prev Alzheimers Dis 2021; 8: 249–256.

Further info

Can the Symptoms of Autism be Reversed? Conference report.

Can the Symptoms of Autism be Reversed? Conference report.

There is no doubt that autism diagnoses, both across the UK and US are escalating at a worrying rate.

A clear illustration of this is the recently published Scottish Schools Census, showing a year by year steady increase in the percentage of Scottish schoolchildren with a diagnosis. Last year, one in 21 schoolchildren had an autism diagnosis, of which one in 14 are boys. This represents a 43-fold increase in 20 years.

As discussed at Food for the Brain’s Smart Kids conference, research is consistently showing that serum homocysteine, which you can test with us at home here, is a reliable indicator of both folate and B12 status and with each unit increase in homocysteine pre-conceptually, the core symptoms required for an autism diagnosis go up. (1)

The majority of studies show that lack of pre-natal folic acid supplementation or low folate, increase the risk of aspects of neurodivergence. Studies on B12 are less clear however. Further studies are under way which will help determine both the optimal level of folate and B12 and whether they are synergistic, as has been found in Alzheimer’s prevention. Our view is that homocysteine should be measured and high levels lowered with appropriate diet and supplementation.

A recent study of 3,000 EU children reported that one third had B12 levels below 200pg/ml, (2) with deficiency more prevalent in vegan children. Another EU survey reports than only one in ten overweight women supplement folic acid in pregnancy. This is really concerning.

It’s the total load – not just one thing

The over-arching theme of this excellent conference was that of ‘total load’ and the interaction between predisposing genes and a nutritional deficient diet and/or toxic overload. It stressed the need to think in terms of the ‘total load’ on a child at critical stages of development, starting in pregnancy. A study of 192 twin pairs, published in the Archives of General Psychiatry, concluded that environmental factors were a greater contributor than heritability, contributing 55% of risk (3). 

Additionally, there are many gene variations which don’t cause, but do increase the risk of neurodivergence. An example is a methylation gene variant MTHFR677TT, which increases risk for both autism and Alzheimer’s. Healthy methylation requires B vitamins, especially vitamin B12 and folate, found in ‘foliage’ – vegetables and greens. A study in China in the journal ‘Frontiers in Paediatrics’(4), comparing several thousand with or without this gene variation found that having it “… was associated with the increased risk of autism. For those mothers and children who are generally susceptible to autism, prenatal folate and vitamin B12 may reduce the risk that children suffer from autism.” This is just one example of the gene-environment interplay.

smart kids confernce

The results of a survey by the Autism Research Institute of over 27,000 parents who rated different nutritional interventions they tried, rating whether their child got better or worse, reported some clear winners of diet changes and supplements. The following had 10:1 or better ratings. 

Removed milk/dairy 32:1

Removed wheat 30:1

Essential fatty acids 30:1

Removed chocolate 28:1

Removed sugar 27:1

Food allergy treatment 27:1

Feingold diet (no wheat or milk) 26:1

Zinc 24:1

Rotation diet 23;1

Candida diet 20:1

Removed eggs 20:1

Vitamin C 20:1

Vitamin A 16:1

Cod liver oil 14:1

Vitamin B6/magnesium 11:1

Specific carbohydrate diet 10:1

Life-changing’ improvement through dietary changes…

Another parent-reporting survey conducted by the UK charity Thinking Autism in 2014 (5), involving similar dietary guidance, and written up into a report by academics at Queen Mary, University of London in 2016, found that, out of 237 families who reported using various dietary interventions with their children with autism, 170 families reported either ‘life-changing’ or ‘significant’ improvements, while only 12 children were reported as having  no noticeable change.

If you are a practitioner and would like a deep dive into the Smart Kids conference, recordings are now available.

If you are a parent or are neurodivergent yourself and would like to hear from clinicians who have considerable experience in helping those with symptoms get better, the Optimising Neurodivergence webinar is now available.

But first, do complete the COGNITION for Smart Kids test (or the COGNITION test if you are a parent or practitioner) to help both our research and help yourself at the same time. 

Here’s an example report.

smart kids cognition
Test Your Cognitive Function Now green banner.

References:

1 Roigé-Castellví J, Murphy M, Fernández-Ballart J, Canals J. Moderately elevated preconception fasting plasma total homocysteine is a risk factor for psychological problems in childhood. Public Health Nutr. 2019 Jun;22(9):1615-1623. doi: 10.1017/S1368980018003610. Epub 2019 Jan 14. PMID: 30636652; PMCID: PMC10261079.
2 Kara İS, Peker NA, Dolğun İ, Mertoğlu C. Vitamin B12 Level in Children. J Curr Pediatr. 2023 Aug;21(2):127-134. doi:10.4274/jcp.2023.75688.
3 https://pmc.ncbi.nlm.nih.gov/articles/PMC4440679/
4 https://pmc.ncbi.nlm.nih.gov/articles/PMC7987783/
5 https://www.thinkingautism.org.uk/taking-action/resources-and-publications/health-and-service-provision-for-people-with-autism/

Further info

Could ‘Statins Cut The Risk Of Dementia For All’?

By Patrick Holford

do statins increase the risk of dementia picture of tablets in hand

Recently, the Telegraph reported: “Statins can reduce the risk of dementia among those who already have low cholesterol.” The article claimed that those on statins were less likely to develop dementia – even Alzheimer’s – and that low LDL cholesterol was somehow protective.

Frankly, this is dangerous misinformation.

Why? Because it contradicts robust scientific evidence that low cholesterol – particularly below 4 mmol/l – increases the risk for dementia. That’s hardly surprising when you consider that 25% of the cholesterol in your body is in your brain. Cholesterol is a vital component of neuronal membranes – it’s not just blood fat, it’s brain fuel.

And as for statins? There’s no credible evidence that they prevent dementia. Quite the opposite: the evidence points to statins lowering brain-essential cholesterol and raising dementia risk. So I asked cholesterol expert Dr Malcolm Kendrick for his take on the study in question.

His response was blunt but justified: “This study is horseshit. Here’s why…

Dr Kendrick Key Critiques:

  1. LDL measurement was vague. It’s unclear if they even measured LDL directly- most studies use the Friedewald formula, known to be wildly inaccurate, especially with high triglycerides or low HDL.
  2. Only one measurement. LDL was recorded once at the study’s start – never again. That’s like measuring someone’s blood pressure once and claiming to predict their lifetime stroke risk.
  3. Bizarre cohort overlap. Somehow, 170,174 participants were in both high and low LDL groups? That’s statistically and biologically nonsensical.
  4. Alzheimer’s exclusion unexplained. Those with pre-existing Alzheimer’s were removed, but with no breakdown of their LDL levels – crucial missing data.
  5. Propensity score manipulation. This “retrospective matching” excluded over 350,000 people, distorting the natural associations. Diabetes and hyperlipidaemia were artificially balanced between groups, masking real-world relationships.
  6. Key confounder: statin timing. Participants were only included after being prescribed statins, meaning LDL levels were already artificially lowered. So “low LDL” here is post-drug, not natural. The entire premise collapses.

This study, like too many others published today, exemplifies what Drummond Rennie famously criticised:

There is no study too fragmented, no hypothesis too trivial, no design too warped, no analysis too self-serving for it to be published.

So what do we actually know? Here is an extract from Patrick’s new book – Alzheimers: Prevention is the Cure.

Cholesterol and the Brain – The Real Story

Your brain needs cholesterol. Low cholesterol (<4 mmol/l) is a clear risk factor for dementia. One biomarker study found that high homocysteine and low cholesterol were the best predictors of dementia risk【1】.

And what’s a common cause of low cholesterol in the elderly? Statins. These drugs have consistently failed to show benefits in preventing cognitive decline【2】.

This fits what we know genetically. The ApoE gene governs how cholesterol gets into neurons. Those with ApoE4 are less efficient at this – that’s why they’re more prone to cognitive decline.

It’s not high cholesterol itself that’s dangerous – it’s cholesterol mismanagement in the brain.

Yes, very high cholesterol (above 6.5 mmol/l) is statistically linked to increased dementia risk – but modest elevations, particularly with a healthy lifestyle, are not a problem【3】. And even that data is shaky. One meta-analysis of over a million people showed only a 14% increased dementia risk with “high” cholesterol. But the thresholds varied – some studies defined “high” as anything over 6.2 mmol/l【3】.

More importantly, people with higher cholesterol often eat more sugar, processed foods, and trans fats – all factors known to fuel inflammation and oxidative stress in the brain.

The Lancet Commission, which makes the anti-cholesterol case, even acknowledged this diet–dementia link: in a cohort of 94,184 Danes, poor diet predicted both high LDL and dementia risk【4】.

So maybe it’s not the cholesterol – it’s what comes with it.

Statins and the Hope for Vascular Dementia 

Originally, statins were hyped for vascular dementia – about 20% of all dementia cases – because of their supposed blood vessel–protective effects. But that theory has fallen flat. A Cochrane review found no benefit from statins for dementia prevention【6】.

And the best independent trial – not funded by drug companies – also found no cardiovascular benefit for statins in older adults【5】.

There’s no data supporting the notion that statins protect the brain. Yet the Lancet Commission listed “high cholesterol” as contributing 7% to dementia risk, which will no doubt spur even more statin prescriptions【4】.

The Optimum Nutrition Perspective

From an optimum nutrition standpoint, we view cholesterol differently.

If your total cholesterol is up to 6.5 mmol/l – but you have high HDL, low triglycerides, low homocysteine, and a healthy diet low in sugar and refined carbs – you’re not at risk. In fact, you’re likely protected.

One recent study showed that higher HDL in midlife predicted significantly lower future dementia risk【7】. Low HDL, not high total cholesterol, is a hallmark of metabolic syndrome – the precursor to diabetes, heart disease, and yes, dementia.

The evidence is clear: cholesterol is essential for brain health. Statins do not prevent dementia – and may contribute to cognitive decline by pushing cholesterol levels too low.

Instead of dumbing down the brain with unnecessary statins, we need to smarten up with nutrients that build brain health: omega-3 fats, phospholipids, B vitamins, and a low-sugar diet.

Doctors prescribing statins as dementia prevention are not only missing the mark – they may be making things worse.

Let’s change the narrative. Let’s put nutrition – not cholesterol fear – at the top of the brain health agenda. Find out more in Patrick’s new book – Alzheimer’s: Prevention is the Cure.

Alzheimer's prevention is the cure book by Patrick Holford image
Test Your Cognitive Function Now green banner.

References

1  Gong, Q., Xie, L., Bi, M., & Yu, L. (2021). A probability formula derived from serum indicators, age, and comorbidities as an early predictor of dementia in elderly Chinese people. Brain and Behavior 11, e2236. https://doi.org/10.1002/brb3.2236

2 Peters, R, Breitner, J, James, S, et al. Dementia risk reduction, why haven’t the pharmacological risk reduction trials worked? An in-depth exploration of seven established risk factors. Alzheimer’s Dement. 2021; 7:e12202. https://doi.org/10.1002/trc2.12202 

3 Wee J, Sukudom S, Bhat S, Marklund M, Peiris NJ, Hoyos CM, Patel S, Naismith SL, Dwivedi G, Misra A. The relationship between midlife dyslipidemia and lifetime incidence of dementia: A systematic review and meta-analysis of cohort studies. Alzheimers Dement (Amst). 2023 Mar 8;15(1):e12395. doi: 10.1002/dad2.12395. PMID: 36911359; PMCID: PMC9993469.

4  Kjeldsen EW, Thomassen JQ, Rasmussen KL, Nordestgaard BG, Tybjærg-Hansen A, Frikke-Schmidt R. Adherence to dietary guidelines and risk of dementia: a prospective cohort study of 94 184 individuals. Epidemiol Psychiatr Sci 2022; 31: e71. 

5  Han BH, Sutin D, Williamson JD, Davis BR, Piller LB, Pervin H, Pressel SL, Blaum CS; ALLHAT Collaborative Research Group. Effect of Statin Treatment vs Usual Care on Primary Cardiovascular Prevention Among Older Adults: The ALLHAT-LLT Randomized Clinical Trial. JAMA Intern Med. 2017 Jul 1;177(7):955-965. doi: 10.1001/jamainternmed.2017.1442. PMID: 28531241; PMCID: PMC5543335.

6  McGuinness B, Craig D, Bullock R, Passmore P. Statins for the prevention of dementia. Cochrane Database Syst Rev 2016;1: CD003160. 

7 Zhang X, Tong T, Chang A, Ang TFA, Tao Q, Auerbach S, Devine S, Qiu WQ, Mez J, Massaro J, Lunetta KL, Au R, Farrer LA. Midlife lipid and glucose levels are associated with Alzheimer’s disease. Alzheimers Dement. 2023 Jan;19(1):181-193. doi: 10.1002/alz.12641. Epub 2022 Mar 23. PMID: 35319157; PMCID: PMC10078665.

Further info

Can the Symptoms of Autism be Reversed?

By Patrick Holford

Something concerning is happening to our children – an increasing number are experiencing psychological and behavioural challenges, often diagnosed as autism. 

These challenges range from reduced eye contact and language delays to social difficulties, cognitive struggles, emotional meltdowns, aggression, and in some cases, depression. But what is driving this surge?

Is it down to genetics & better diagnosis?

While mainstream medicine largely attributes autism to genetics, explaining the rise as improved diagnostic recognition, a growing body of independent researchers and clinicians in the US and UK suggests otherwise. The rapid increase in cases across multiple countries cannot be solely explained by genetics, as genes do not change so quickly. In the US, autism rates have skyrocketed from 2 in 10,000 to 1 in 36 over 50 years. In the UK, official government data estimates 1 in 62 children are classified as autistic; an eightfold increase in 20 years.  Meanwhile, school census data from Scotland and Northern Ireland report even higher rates, with 1 in 20 children diagnosed. These numbers strongly indicate that environmental factors, including diet, play a key role. This also suggests that proactive steps could help reduce risk.

That is why we are launching COGNITION for Smart Kids &Teens in April with the online ‘Smart Kids’ conference. We are bringing together leading experts to examine ways to prevent and potentially mitigate the impact of autism through environmental and nutritional interventions. In addition, we also have our ‘Optimising Neurodivergence public webinar for parents, caregivers or any non-practitioners who want to learn how to support our children to reach their full potential.

New Approaches Show Encouraging Results

Dr. Chris D’Adamo, Assistant Professor at the University of Maryland School of Medicine and Director of the Centre for Integrative Medicine, has been at the forefront of research into environmental influences on autism. His recent paper, published in Personalized Medicine, estimates a 300% rise in autism cases since 2000. The study also documents a case where early intervention reversed autism symptoms by addressing modifiable lifestyle and environmental factors.

The case involved twin toddler girls exhibiting classic autistic traits;limited communication, repetitive behaviours, resistance to change and severe gastrointestinal issues. Under a comprehensive programme, led by a team of physicians, they implemented tailored interventions focused on diet, environment and lifestyle. The results were striking; within months, both girls showed dramatic improvements. Their autism severity scores dropped significantly, with one twin’s score reducing from 76 to 32 and the other from 43 to just 4. (Read more on this case here)

In the UK, Dr. Lorene Amet, a functional nutritionist and founder of The Lauriston Centre, has been applying similar integrative approaches. She has worked with hundreds of families, with remarkable success. A survey conducted with the charity Thinking Autism, assessed 220 children who followed her recommendations. 169 families reported either ‘life-changing’ or ‘very beneficial’ improvements, while only 11 children saw no noticeable change. 

Yet, despite such promising results, the NHS maintains that autism has no cure and advises against interventions such as vitamins, minerals, and dietary modifications.  The NICE guidelines currently offer no targeted nutritional strategies for autism management, leaving many parents with limited options. 

Can Autism Risk Be Reduced Before Birth?

Another key topic at the Smart Kids Conference is prevention; reducing the likelihood of autism before birth. Research led by Associate Professor Michelle Murphy of the Universitat Rovira I Virgili in Spain, has revealed a crucial link between B vitamin deficiencies in early pregnancy and a child’s likelihood of developing autism-related traits. Her studies show that children of mothers who were low in B vitamins before conception were significantly more likely to display withdrawn behaviour, anxiety, depression or aggression by age six. 

The connection between maternal nutrition and neurological development is well established. For decades, pregnant women have been advised to take folic acid to prevent neural tube defects; a policy delayed by 25 years, resulting in hundreds of thousands of avoidable birth defects. Children with autism are six times more likely to have neural tube defects, further linking B vitamin deficiencies to neurodevelopmental issues.

This aligns with earlier research from Oxford University’s Professor David Smith, one of our scientific advisors.  His work demonstrated that B vitamins lower homocysteine, a toxic amino acid linked to autism, depression, cognitive impairments in children and Alzheimer’s in adults.  Professor Murphy’s research further suggests that even mildly elevated homocysteine levels before pregnancy strongly predict neurodivergent traits in children. This underscores the importance of nutritional screening and intervention before conception.

There Is So Much That Parents Can Do…

We are inviting parents to take part in a free online assessment of their child’s cognitive, emotional, and behavioural function, alongside a diet and lifestyle questionnaire to help optimise brain health. Parents can also access a home test kit for homocysteine levels, providing valuable insight into potential nutritional deficiencies that may affect brain function.

The Smart Kids conference will provide further guidance on evidence-based interventions, bringing together researchers, clinicians, and parents seeking practical solutions to support children’s cognitive development.

“People come in assorted shapes and sizes, with brains that are unique,” says Dr Rona Tutt, OBE, a trustee of Food for the Brain and past President of the National Association of Head Teachers. “A significant minority who are neurodivergent need to be recognised, valued, and supported to maximise their strengths and overcome challenges. Understanding the factors driving the rise in neurodivergence is key to ensuring the best outcomes for future generations.”
For more information on all the events relating to Smart Kids – visit foodforthebrain.org/smartkids.

References:

1 https://www.cdc.gov/mmwr/volumes/72/ss/ss7202a1.htm?s_cid=ss7202a1_w

2 https://researchbriefings.files.parliament.uk/documents/POST-PN-0612/POST-PN-0612.pdf; see also Russell G, Stapley S, Newlove-Delgado T, Salmon A, White R, Warren F, Pearson A, Ford T. Time trends in autism diagnosis over 20 years: a UK population-based cohort study. J Child Psychol Psychiatry. 2022 Jun;63(6):674-682. doi: 10.1111/jcpp.13505

3 https://www.gov.scot/publications/pupil-census-supplementary-statistics/

4 https://www.health-ni.gov.uk/news/publication-prevalence-autism-including-aspergers-syndrome-school-age-children-northern-ireland-a nnual-report-2023

5 D’Adamo C et al., Reversal of Autism Symptoms among Dizygotic Twins through a Personalized Lifestyle and Environmental Modification Approach: A Case Report and Review of the Literature. J Pers Med. 2024 Jun 15;14(6):641. doi: 10.3390/jpm14060641

6 Survey conducted in collaboration with the charity Thinking Autism. The full survey results will be shown at the Smart Kids conference, April 24th 20025.

7 https://www.nhs.uk/conditions/autism/autism-and-everyday-life/treatments-that-are-not-recommended-for-autism/

8  https://www.nice.org.uk/guidance/cg142/chapter/Recommendations#interventions-for-autism-2

9 Roigé-Castellví J, Murphy M, Fernández-Ballart J, Canals J. Moderately elevated preconception fasting plasma total homocysteine is a risk factor for psychological problems in childhood. Public Health Nutr. 2019 Jun;22(9):1615-1623. doi: 10.1017/S1368980018003610; see also Murphy MM, Fernandez-Ballart JD, Molloy AM, Canals J. Moderately elevated maternal homocysteine at preconception is inversely associated with cognitive performance in children 4 months and 6 years after birth. Matern Child Nutr 2017;13,e12289 . doi: 10.1111/mcn.12289

10 Hasler M, Fideli ÜS, Susi A, Hisle-Gorman E. Examining the relationship between autism spectrum disorder and neural tube defects. Congenit Anom (Kyoto). 2023 Jul;63(4):100-108. doi: 10.1111/cga.12516. Epub 2023 Apr 18. PMID: 37073427.11 Smith AD, Refsum H. Homocysteine – from disease biomarker to disease prevention. J Intern Med. 2021 Oct;290(4):826-854. doi: 10.1111/joim.13279

Further info

‘Amyloid: A legacy of lies in Alzheimer’s science,’ says The New York Times

By Patrick Holford, in response to the New York Times essay here.

Recently, investigator Charles Piller exposed the fraudulent claims behind the amyloid theory of Alzheimer’s, that has caused heads to roll.

The article, based on his new book Doctored: Fraud, Arrogance, and Tragedy in the Quest to Cure Alzheimer’s, presents evidence of fraud. It reveals that Dr Masliah, the Head of the National Institute on Ageing (a division of the US National Institutes of Health) and responsible for billions in funding, had for decades included improperly manipulated images of brain tissue and other technical visuals in his research. 

With roughly 800 papers to his name, many of them considered highly influential, Dr. Masliah seemed a natural choice to steer the funding for Alzheimer’s research. He hailed the moment as the dawning of “the golden era of Alzheimer’s disease research”. The National Institutes of Health announced that it had found that Dr. Masliah engaged in research misconduct and that he no longer held his leadership position.

Marc Tessier-Lavigne, the former president of Stanford University, was known as a global leader in research on the brain’s circuitry in Alzheimer’s and other neurological conditions. He resigned in 2023 after an intrepid student journalist revealed numerous altered images in the research of his lab, in papers he co-authored. A Stanford University investigation, however, didn’t find evidence to conclude that he personally engaged in research misconduct. They did note that at various times when concerns with his papers emerged— between 2001 and 2021—Dr. Tessier-Lavigne failed to decisively and forthrightly correct mistakes in the scientific record.

Amyloid exaggerations

What isn’t being fully exposed, is just how bad the results of the anti-amyloid drug treatments are and how the drug companies who run these trials manage to squeeze a result, just enough to get a medical licence for their treatment. Everyone is aware of this exaggeration by bigging up the results. 

For example, the Alzheimer’s Society described the miniscule difference in effect of the anti-amyloid drug as follows:  ‘Lecanemab slowed down the speed at which memory and thinking skills got worse by 27%’. 

This is economical with the truth.

The British Medical Journal Editorial on the trial, in relation to a clinically meaningful effect, said it ‘fell well short, representing only around a third of what a minimum clinically important difference might look like’. Those on the drug just hit the same rock bottom about 3 months later than those on the placebo and the difference was so small that no-one is likely to notice.

No-one got better. They all got worse. Quite a few had adverse effects, with brain bleeding and swelling. More than a quarter had adverse reactions. A few died as a consequence. 

Is three months of ‘slightly less worse’ symptoms worth the suffering of adverse events by one in four participants including death (about one in 500) – and all this at vast expense? 

Expensive, ineffective and rejected by NICE

If such treatment was started before a person was put into care, at best it could mean putting them in a care home three months later, potentially saving £3,000. If treatment were given whilst in a care home it would mean three months more time in a care home, potentially costing £3,000 more. Either way, at a treatment cost likely to be in the region of £50,000 per year this is clearly not cost effective for the NHS, which is why the National Institute for Health and Care Excellence (NICE) quite rightly rejected it.

The greatest missed opportunity is that we already know how to reduce Alzheimer’s risk – through targeted diet, lifestyle and nutrient optimisation – yet far less funding and attention goes toward implementing these strategies at scale.

The power is in your hands and it’s never too late or too early to start.

Prevention is key and you can start today – so please encourage everyone you know to take the Cognitive Function test here.

Get started today:
  • Take the Cognitive Function Test: Assess your brain health today and gain personalised insights. 
  • Get personalised data on your body and join our research by ordering your DRIfT 5 in 1 test here so you can join our research and find out what your unique body needs.
  • Become a Friend & join the COGNITION Programme: Support our mission with a small monthly donation and receive tailored steps to improve your brain resilience and track your progress.
Further info

The Lancet Report Omission! World Experts Criticise Latest Alzheimer Report

The Lancet Report Omission! World Experts Criticise Latest Alzheimer Report

The recent Lancet dementia commission has ignored the best nutrition prevention evidence. (See the Lancet Commission Report here)

The Alzheimer’s Prevention Expert Group has accused the Lancet Commission of bad science for knowingly ignoring two highly effective and firmly evidence-based ways to reduce risk factors for dementia – high dose supplements of B vitamins and omega-3 fish oils as well as the impact of a low sugar diet. 

Alzheimer’s prevention  expert group

We support this group of eleven leading scientists and have called on the Lancet to revise their report, which hit the headlines in the past weeks, minimising the effectiveness of nutrition and lifestyle interventions.

(Click here to read the three letters sent to The Lancet asking for a revision in this report.)

The major benefit of B vitamins is their ability to lower levels of the damaging amino acid homocysteine, found in the brain of Alzheimer’s patients. A comprehensive Chinese review of Alzheimer’s prevention research in 2020, described homocysteine lowering as ‘the most promising intervention for Alzheimer’s disease prevention’ (1).

Last month, a review in the Journal of Prevention of Alzheimer’s Disease, listed reducing homocysteine among the top five evidence-based actions (2).  A US National Institutes of Health review attributes almost a quarter (22%) of the risk of Alzheimer’s to raised homocysteine and a further 22% to lack of seafood and omega-3 fish oils (3). 

The combination of high homocysteine, low omega-3 and vitamin D is present in the majority of those over 50 and quadruples dementia risk, according to research in Holland earlier this year, led by Professor Annick van Soest at Wageningen University (4). 

“Remarkably, a suboptimal status of all three nutrients was associated with a four-fold increased risk of dementia,” she says.  These common combined deficiencies, so easily corrected, could have a bigger impact on dementia risk than any of the 14 risk factors listed in the Lancet Commission’s report.

The Lancet Alzheimer Report Omission

Yet, for the third time since the first Lancet Commission report in 2017, and despite being sent all the evidence, the report’s scientists, headed by Professor Gill Livingston, have ignored it. 

Instead, two far less significant risk factors have been added – cholesterol and cataracts. The report claims cataract surgery would eliminate a very modest 2% of overall risk. In stark contrast, reducing high homocysteine, which affects one in two of over 65 ‘s could potentially eliminate a quarter of all risk, “saving the UK economy approximately £60 million per year,” says Oxford University health economist, Professor Apostolos Tsiachristas.

Why has important science been missed out?

Asked why she continued to deny any benefit from homocysteine lowering, Professor Gill Livingston commented: “high homocysteine only affects a small number of people and there are no trials that show that lowering it has any benefit.” 

This is simply not true.

Studies in Holland (5), Norway (6), the UK (7) and China (8), have additionally reported a synergistic effect between B vitamins and omega-3, with several times better clinical benefit than any dementia drug. A study at Oxford University showed two thirds less brain shrinkage in those with mild cognitive impairment given B vitamins with sufficient omega-3 compared to placebo and one third of trial participants were clinically dementia-free at the end of one year (9). These studies were sent to Professor Gill Livingston in 2023.

The commission has also ignored studies showing a benefit from improving omega-3 status by eating fish or taking supplements. The Lancet Report cited only one study linking higher blood levels of omega-3 fatty acids with risk for dementia which concluded that this study provided “compelling evidence for a relationship between long-chain omega-3 fatty acids levels and lower risks for dementia and related outcomes .” 

Essentially, the same conclusions were reached by at least eight other similar studies. “Why were these studies ignored?” asked Professor William Harris of the Fatty Acid Research Institute, a leading omega-3 expert in the US. “The vast majority of adults in the western world have suboptimal blood omega-3 fatty acid levels. Increased consumption of marine omega-3 is safe, simple, cheap and effective.”   

By ignoring these well established, easy to change risk factors the Lancet Commission was able to reduce the claimed preventable risk to 45%. Something that China’s leading prevention expert Professor Jin-Tai Yu of Fudan University in Shanghai strongly disputes. “It may be possible to prevent up to 80% of dementia cases if all known risk factors, including homocysteine lowering B vitamins and omega-3, found in oily fish, were targeted.” he says. 

He was co-author of a study in the journal Nature, together with Oxford University’s leading prevention expert Professor David Smith, analysing data from the UK BioBank which concluded that ‘up to 73% of dementia cases can be prevented.” However, even this may be an under-estimate as this study excluded blood test measures, says Professor David Smith. “This figure could be higher if a person’s omega-3 and B vitamin status, measured by a blood test for homocysteine, were taken into account.”

Homocysteine, omega-3 and vitamin D blood levels attribute 45% of modifiable risk to a deficiency of B vitamins and brain fats. 

The Lancet Omission – what can we do?

That is why we offer our free online Cognitive Function Test. In addition, our accurate, at home pin prick blood tests are available internationally, helping you understand your future dementia risk and what you can do to lower it.

We are ‘citizen science’ in action and gathering independent research on the effectiveness of diet, supplements and lifestyle change that anyone can join. 

Simply put – the cultural bias against nutrition, demonstrated by the Lancet Commission’s omissions, isn’t science-based. 

And it certainly isn’t helping those at risk take easy, positive actions to reduce it.

Action steps

The next steps you need to take to reduce your risk:

References:

1 Yu JT, et al. J Neurol Neurosurg Psychiatry. 2020 Nov;91(11):1201-1209
2 He S.-Y, et al. Prev Alzheimers Dis. 2024 Aug;11:917–927
3 Beydoun MA, et al. BMC Public Health. 2014 Jun 24;14:643
4 van Soest APM, et al. Am J Clin Nutr. 2021 Apr 6;113(4):801-809
5 van Soest APM, et al. Eur J Nutr. 2022 Jun;15:61 3731–3739
6 Jernerén F, et al. J Azheimers Dis. 2019;69(1):189-197
7 Oulhaj A, et al. J Alzheimers Dis. 2016;50(2):547-57
8 Li M, et al. Eur J Nutr. 2021 Jun;60(4):1795-1808
9 Jernerén F, et al. Am J Clin Nutr. 2015 Jul;102(1):215-21
10 Zhang Y, et al. Nature Human Behaviour. 2023;7:1185–1195

Further info

WHO says Vitamins B, PUFA (Omega-3) & Multivitamins Should Not Be Recommended

Do supplements really help when it comes to cognitive decline or are they money wasted down the toilet?!

We believe that the science supports the use of correct supplementation in order to reduce risk of dementia and Alzheimer’s – so what is going on and what does the research really say?

The WHO report saying supplements are ‘not recommended’

A 2018 report by the WHO states: ‘Vitamins B and E, PUFA and multi-complex supplementation should not be recommended to reduce the risk of cognitive decline and/or dementia.’ 

This 2018 WHO review makes no reference at all to the effect of B vitamins in slowing brain atrophy (1) and in improving cognition (2) in the rather large sub-group, estimated to be up to half of those over 65, with raised homocysteine. After all, why would B vitamins be expected to have an effect in those not deficient?

On closer inspection, three of the four cited studies in the WHO document are actually one meta-analysis (which is a statistical process of analysing and combining results from several similar studies). It cites only one paper which considered B vitamins (the one part-funded by Alzheimer’s Research UK) which showed a clear effect of B vitamins improving cognition in those with raised homocysteine, and one study on omega-3 DHA, which also shows clear benefit as stated in the studies summaries. Thus, it misrepresented the study that ARUK part funded on B vitamins as negative, when they had a clearly positive effect. 

The only cited B vitamin study (2) states, “The mean plasma total homocysteine was 30% lower in those treated with B vitamins relative to placebo. B vitamins stabilised executive function (CLOX) relative to placebo. There was significant benefit of B-vitamin treatment among participants with baseline homocysteine above the median in global cognition, episodic memory and semantic memory. Clinical benefit occurred in the B-vitamin group for those in the upper quartile of homocysteine at baseline in global clinical dementia rating score… In this small intervention trial, B vitamins appear to slow cognitive and clinical decline in people with mild cognitive impairment (MCI), in particular in those with elevated homocysteine.”

The only cited study on omega-3 fish oils (3) states, “The fish oil group showed significant improvement in short-term and working memory.” The 12-month change in memory was significantly better in the fish oil group. This study suggested the potential role of fish oil to improve memory function in MCI subjects.

So, even based on its own cited evidence, the benefit of both B vitamins and omega-3 fish oils is supported.

How the WHO statement then recommends the opposite, ‘Vitamins B and E, PUFA and multi-complex supplementation should not be recommended to reduce the risk of cognitive decline and/or dementia.’ beggars belief. But the real problem is not the shoddy research, from 2015, used to produce this report but that it is out of date. The WHO ‘rules’ for this report was to ignore any study that was more than 5 years old, yet the WHO authors republished this same report, with the same conclusions, in 2022, by then redundant according to its own rules!

What we’ve learned since 2018

Also, much has been learnt, and published, since 2018. There is now evidence that homocysteine lowering B vitamins are most effective in those with sufficient omega-3 status and omega-3 fish oils are most effective in those with low homocysteine. This is clinical confirmation of the known mechanism of co-dependence and illustrates why the WHO document is now out of date. We prefer published, peer-reviewed reviews such as the editorial in the American Journal of Clinical Nutrition in 2021 (4) and a meta-analysis in 2023 (5).

Additionally, since 2018, there have been at least 17 studies (6-22), including both randomised controlled trials and cohort studies which show benefit of either omega-3 fish oil supplementation, or higher intake from seafood with resultant higher omega-3 blood levels, in reducing risk for and incidence of dementia or cognitive decline.

This is another example showing why the WHO document is no longer current and relevant. Yet leading Alzheimer’s charities such as the Alzheimer’s Society and Alzheimer’s Research UK (ARUK – who part funded the highly effective B vitamin trial) still refer to this redundant report.

With regard to multivitamins, the latest meta-analysis states (7), “The meta-analysis of COSMOS substudies showed clear evidence of multivitamin-mineral benefits on global cognition and episodic memory; the magnitude of effect on global cognition was equivalent to reducing cognitive ageing by 2 years”. B vitamins, given to those with raised homocysteine, are much more effective than multivitamins given to all – and more effecctive in those with sufficient omega-3 status.

Summary

In conclusion, the 2018 WHO report is so sloppy, and out of date – by its own rules. It would be wise for WHO to withdraw this misleading report and certainly for both ARUK and the Alzheimer’s Society and any other Alzheimer’s or dementia organisations to stop referring to it in the context of omega-3, B vitamins or multivitamins, if they are to maintain credibility in being science-based.

Note: Many people are not aware that the WHO is no longer only funded by donations from the countries that it is supposed to serve but is now also privately funded, with the second largest funder being the Bill Gates Foundation, which accounts for 10% of its budget, leading to questions over influences on its agenda. 


References

1. Smith AD, Smith SM, de Jager CA, Whitbread P, Johnston C, Agacinski G, et al. Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment: a randomized controlled trial. PloS one 2010;5(9):e12244.

2. de Jager CA, Oulhaj A, Jacoby R, Refsum H, Smith AD. Cognitive and clinical outcomes of homocysteine-lowering B-vitamin treatment in mild cognitive impairment: a randomized controlled trial. International journal of geriatric psychiatry 2012;27(6):592-600.

3. Lee et al 2013 – https://pubmed.ncbi.nlm.nih.gov/22932777/

4. Smith AD, Jernerén F, Refsum H. ω-3 fatty acids and their interactions. Am J Clin Nutr 2021;113(4):775-8.

5. Fairbairn P, Dyall SC, Tsofliou F. The effects of multi-nutrient formulas containing a combination of n-3 PUFA and B vitamins on cognition in the older adult: a systematic review and meta-analysis. The British journal of nutrition 2023;129(3):428-41.

6. Liu X, Zhuang P, Li Y, Wu F, Wan X, Zhang Y, et al. Association of fish oil supplementation with risk of incident dementia: A prospective study of 215,083 older adults. Clinical nutrition (Edinburgh, Scotland) 2022;41(3):589-98.

7. Vyas CM, Manson JE, Sesso HD, Cook NR, Rist PM, Weinberg A, et al. Effect of multivitamin-mineral supplementation versus placebo on cognitive function: results from the clinic subcohort of the Cocoa Supplement and Multivitamin Outcomes Study (COSMOS) randomized clinical trial and meta-analysis of 3 cognitive studies within COSMOS. Am J Clin Nutr 2024;119(3):692-701.

8. Jerneren F, Cederholm T, Refsum H, Smith AD, Turner C, Palmblad J, et al. Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. Journal of Alzheimer’s disease : JAD 2019.

9. Rouch L, Virecoulon Giudici K, Cantet C, Guyonnet S, Delrieu J, Legrand P, et al. Associations of erythrocyte omega-3 fatty acids with cognition, brain imaging and biomarkers in the Alzheimer’s disease neuroimaging initiative: cross-sectional and longitudinal retrospective analyses. Am J Clin Nutr 2022;116(6):1492-506.

10. He X, Yu H, Fang J, Qi Z, Pei S, Yan B, et al. The effect of n-3 polyunsaturated fatty acid supplementation on cognitive function outcomes in the elderly depends on the baseline omega-3 index. Food & function 2023;14(21):9506-17.

11. Doughty KN, Blazek J, Leonard D, Barlow CE, DeFina LF, Omree S, et al. Omega-3 index, cardiorespiratory fitness, and cognitive function in mid-age and older adults. Prev Med Rep 2023;35:102364.

12. Loong S, Barnes S, Gatto NM, Chowdhury S, Lee GJ. Omega-3 Fatty Acids, Cognition, and Brain Volume in Older Adults. Brain Sci 2023;13(9).

13. Maltais M, Lorrain D, Léveillé P, Viens I, Vachon A, Houeto A, et al. Long-chain Omega-3 fatty acids supplementation and cognitive performance throughout adulthood: A 6-month randomized controlled trial. Prostaglandins, leukotrienes, and essential fatty acids 2022;178:102415.

14. Andriambelo B, Stiffel M, Roke K, Plourde M. New perspectives on randomized controlled trials with omega-3 fatty acid supplements and cognition: A scoping review. Ageing Res Rev 2023;85:101835.

15. Wei BZ, Li L, Dong CW, Tan CC, Xu W. The Relationship of Omega-3 Fatty Acids with Dementia and Cognitive Decline: Evidence from Prospective Cohort Studies of Supplementation, Dietary Intake, and Blood Markers. Am J Clin Nutr 2023;117(6):1096-109.

16. Grande de França NA, Díaz G, Lengelé L, Soriano G, Caspar-Bauguil S, Saint-Aubert L, et al. Associations Between Blood Nutritional Biomarkers and Cerebral Amyloid-β: Insights From the COGFRAIL Cohort Study. The journals of gerontology Series A, Biological sciences and medical sciences 2024;79(1).

17. Sasaki N, Jones LE, Carpenter DO. Fish consumption and omega-3 polyunsaturated fatty acids from diet are positively associated with cognitive function in older adults even in the presence of exposure to lead, cadmium, selenium, and methylmercury: a cross-sectional study using NHANES 2011-2014 data. Am J Clin Nutr 2024;119(2):283-93.

18. van Soest APM, van de Rest O, Witkamp RF, Cederholm T, de Groot L. DHA status influences effects of B-vitamin supplementation on cognitive ageing: a post-hoc analysis of the B-proof trial. European journal of nutrition 2022;61(7):3731-9.

19. Gao J, Fan H, Wang X, Cheng Y, Hao J, Han S, et al. Association between serum omega-3 PUFAs levels and cognitive impairment in never medically treated first-episode patients with geriatric depression: A cross-sectional study. J Affect Disord 2024;346:1-6.

20. He Y, Huang SY, Wang HF, Zhang W, Deng YT, Zhang YR, et al. Circulating polyunsaturated fatty acids, fish oil supplementation, and risk of incident dementia: a prospective cohort study of 440,750 participants. GeroScience 2023.

21. Chedid G, Malik A, Amangurbanova M, Khraishah H, Welty FK. Docosahexaenoic Acid Levels and Omega-3 Index, but Not Eicosapentaenoic Acid Levels, Are Associated With Improved Cognition in Cognitively Healthy Subjects With Coronary Artery Disease. Arteriosclerosis, thrombosis, and vascular biology 2022.

22. Duchaine CS, Fiocco AJ, Carmichael P-H, Cunnane SC, Plourde M, Lampuré A, et al. Serum ω-3 Fatty Acids and Cognitive Domains in Community-Dwelling Older Adults from the NuAge Study: Exploring the Associations with Other Fatty Acids and Sex. The Journal of nutrition 2022;152(9):2117-24.

Further info

Are Blood Tests for Alzheimer’s a “Misguided Waste of Money”?

You may have heard of a search for new tests to find those most likely to get Alzheimer’s disease? But is this misdirected?

Perhaps so, according to the Alzheimer’s Prevention Expert Group (APEG) –  a collaboration of top UK, American and Chinese academics (which we are a part of – find out more here) who consider this to be “..a misguided waste of money”. 

Controversially, their stance challenges the major thrust of charities such as Alzheimer’s Research (ARUK), which strongly supports search for a reliable test for the disease.

APEG explains that there is already a widely used way to spot failing memory and thinking skills  – hallmarks for dementia and Alzheimer’s. These include a neuropsychological test battery (NTB) and a validated Cognitive Function Test (CFT) similar to the one we provide free. Both are routinely used in memory clinics to diagnose mild cognitive impairment and support the diagnosis of dementia.

Over the last decade the charity Food for the Brain has used the Cognitive Function Test to find people at risk and advise them how to reduce their risk with simple dietary and lifestyle changes. 

Nearly half a million people to date have been tested, with someone taking the test every 2 minutes!

When does Cognitive Decline begin?

Cognitive function declines steadily from the age of 18. This means that it is possible to spot individuals whose cognitive function is dropping off faster than the average, giving time to encourage preventative actions with personalised advice on their diet and lifestyle changes.

Alzheimer’s, which makes up two-thirds of dementia cases, involves the shrinking of certain areas of the brain as neurons die off. It can be detected with a specialised brain scan several years before a diagnosis. These ‘PET’ scans can be used to diagnose Alzheimer’s and/or vascular dementia.  The trouble is that such scans are expensive and not likely performed early enough to discover those ‘at risk’. 

What about p-tau?

As well as shrinkage, another marker for Alzheimer’s is a toxic protein called p-tau. This creates clumps of tangled nerves in the brain. These can be found in the fluid that bathes the brain but again there is a problem. Detecting it can be done with a lumbar puncture, but this is a risky and expensive process and certainly not suitable to test tens of thousands of people. 

At first sight, if a blood test could identify those heading towards Alzheimer’s earlier this could be a cheaper and less invasive alternative to such scans. However, the search is likely driven by a quite different ulterior motive – to create and sell drugs – much like cholesterol and statins. What’s more it’s unlikely to be an improvement!

A recent New York Times article pointed out that such a test would result in people being diagnosed with ‘pre’ Alzheimer’s, even if they have no obvious symptoms. That’s because having the marker would be considered enough to justify a diagnosis of the disease or, at least, the prescription of a drug.

This is what happens with amyloid protein. Amyloid forms plaque in the brains of those with Alzheimer’s. The latest drugs, such as lecanemab and aducanumab, remove this. But not all those with Alzheimer’s have plaque, and people can develop dementia without plaque. What’s more none of these drugs have a clinically significant effect, and they come with the risk of severe adverse effects, including death from brain bleeding and swelling, especially in those with a history of stroke.

A very cheap and safe alternative

Perhaps the most convincing reason why the new blood marker hunt is “misguided” is that there is something very cheap and very safe that can prevent the accumulation of p-tau tangles in the brain – B vitamins.

Suppose you are not taking in enough B6, folate or B12, which becomes harder to absorb as you get older, blood levels of a toxic amino acid called homocysteine rise. This increases the level of p-tau and inhibits the brain from clearing it. According to pharmacology professor David Smith, a member of APEG and our Scientific Advisory Board: “Homocysteine is not a diagnostic marker for dementia but it is a modifiable risk factor. Raised levels of homocysteine account for some 20% of dementia cases and homocysteine testing is relatively inexpensive and available.”

Smith, who was second in charge at Oxford University’s School of Medical Sciences, ran the VITACOG trial which found that high doses of B vitamins given to people with Mild Cognitive Impairment (MCI) and high homocysteine, not only slowed the rate of brain cell death by up to 73% but also arrested cognitive decline.

He, and his APEG colleagues, favour using a Cognitive Function Test, to identify those at risk. Then, testing risk factors and biomarkers such as homocysteine to be included in the research, with funds being made available for testing blood biomarkers because this is one thing you can actually do something about. 

Other useful tests for risk factors include omega-3 and vitamin D levels, since low levels of these nutrients also increase risk; also HbA1c, the standard measure used to diagnose diabetes, since lower levels help protect the brain and high levels indicate those who need to reduce their intake of sugar and processed foods. These tests are corroborative rather than diagnostic but importantly identify prevention actions that people can take. 

We offer at home, accurate pin prick testing for Vitamin D, HbA1c, Omega-3 and Homocysteine (available in US, EU & UK) – order here to be a part of our research and to support our charitable work 

The new paradigm.

This two-step paradigm of:

1. Testing cognitive function early – you can do so here.

2. Then do further blood tests such as homocysteine, omega-3, vitamin D and HBA1c for glucose control that help guide diet and lifestyle prevention, which is available right now. Order your DRIfT test here

So keep things simple and start today!

Complete our validated Cognitive Function Test, then order your blood tests and be a part of our Citizen Science research and movement.

A green Citizen Scientist badge, with the quote "optimum nutrition is the future of medicine".
References

The VITACOG trials, evidence for homocysteine as causal and lowering it with B vitamins as disease modifying and a consensus statement regarding this evidence, in the Journal of Alzheimer’s Disease, is here: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5836397/

The validation of foodforthebrain.org’s Cognitive Function Test in the International Journal of Geriatric Psychiatry is here: https://onlinelibrary.wiley.com/doi/abs/10.1002/gps.3993

The evidence in relation to p-tau and homocysteine is here: https://brainhealthcheck.foodforthebrain.org/the-p-tau-delusion/

Further info

The P-Tau Delusion

Tau is a structural protein that helps build the skeleton, much like pipes, through which nutrients and nerve signals are delivered to different parts of the brain. Our brains contain a balance of tau protein and phosphorylated-tau, abbreviated to p-tau. An abnormal accumulation of p-tau makes these tubular channels tangled and dysfunctional and triggers brain-cell death.1

Too much p-tau also messes up the mitochondria, the cells’ energy factories, potentially leading to brain fatigue. The more p-tau accumulates, the greater the risk of cognitive problems and Alzheimer’s dementia. Also, those with memory decline have been shown to have relatively more p-tau to tau protein.

The next target for dementia drugs is reducing p-tau. Consequently, drugs are being developed and tested that block the kinase enzyme and activate the phosphatase enzyme,2 which is exactly what the homocysteine-lowering B vitamins do. But so far, there are no human clinical trials reporting significant benefit.

The critical prevention question is what stops too much of the tau protein from turning into the potentially harmful p-tau in the first place and what helps restore p-tau to normal tau protein.

The answer is remarkably simple – a lack of B vitamins raises the blood levels of homocysteine, which activates an enzyme, Cdk5 kinase, which adds the bad ‘p’ to tau and blocks another enzyme, protein phosphatase A2, which removes the dangerous ‘p’.3,4 High homocysteine levels also damage the tiny blood vessels in the brain, leading to ‘mini strokes’ or transient ischemic attacks (TIAs), which further raise the levels of p-tau. Homocysteine not only raises the levels of the dangerous p-tau,5 but can also bind to tau,6 further generating the neurofibrillary tangles that then trigger brain-cell death.

So, the simplest way to stop the formation of p-tau, and neurofibrillary tangles, and keep your brain healthy, is to keep your plasma homocysteine level below 10mcmol/l. Half of those above 65 have a homocysteine level higher than this.

By now you’re surely wondering why, if these natural approaches are at least as good, if not better, than drug treatments, and without adverse effects, why this isn’t common knowledge and common practice, especially if the cost is a fraction of the drug treatments. For example, supplementing B vitamins and omega-3 fish oils might cost you £100 a year while anti-amyloid drugs are pitched at around £20,000 a year.

I’m convinced that it is exactly this last point that explains the anomaly. Naturally occurring nutrients cannot be patented; only a man-made invention, such as a drug, can be. Holding a patent means only the company making that product can sell it, and they can determine the price. The price of a drug will include a hefty margin for marketing the drug and creating all the hype to get you, the media and the medical profession to buy into it. Once the patent expires, the price plummets. The price of a leading branded statin dropped by 93 per cent, from close to £30 down to just over £2 a month,7 That’s a lot of margin for marketing. By then, the manufacturers are on to the next ‘new’ patented drug. Up to 2022 $45 billion8 has been spent so far developing the latest ineffective dementia drugs, but the real cost, including the most recent trials and marketing, could be double this. That’s a lot of money to recoup. The first stage is to develop a test that convinces you and your doctor that you ‘need’ the drug. That’s what these tests in the £10 million trial are all about. If you test high, instead of taking an ineffective drug why not do prevention? That’s what the free Cognitive Function Test at foodforthebrain.org is all about.

Extract, used with permission, from Patrick Holford’s Upgrade Your Brain (Thorsons 2024)

REFERENCES

1. Balasu S et al. Science14 Sep 2023 Vol 381, Issue 6663 pp. 1176-1182 DOI: 10.1126/science.abp9556

2. Xia, Y., Prokop, S. & Giasson, B.I. “Don’t Phos Over Tau”: recent developments in clinical biomarkers and therapies targeting tau phosphorylation in Alzheimer’s disease and other tauopathies. Mol Neurodegeneration 16, 37 (2021). https://doi.org/10.1186/s13024-021-00460-5.

3. Smith AD, Refsum H. Homocysteine, B Vitamins, and Cognitive Impairment. Annu Rev Nutr. 2016 Jul 17;36:211-39. doi: 10.1146/annurev-nutr-071715-050947. PMID: 27431367.

4. LiJ-G,ChuJ,BarreroC,MeraliS,Pratico`D.2014.Homocysteine exacerbatesβ-amyloid, tau pathology, and cognitive deficit in a mouse model of Alzheimer’s disease with plaques and tangles. Ann. Neurol. 75:851–63.

5. Shirafuji N et al Homocysteine Increases Tau Phosphorylation, Truncation and Oligomerization. Int J Mol Sci. 2018 Mar 17;19(3):891. doi: 10.3390/ijms19030891. PMID: 29562600; PMCID: PMC5877752.

6. Bossenmeyer-Pourié C et al. N-homocysteinylation of tau and MAP1 is increased in autopsy specimens of Alzheimer’s disease and vascular dementia. J Pathol. 2019 Jul;248(3):291-303. doi: 10.1002/path.5254. Epub 2019 Mar 19. PMID: 307349

8. Cummings JL, Goldman DP, Simmons-Stern NR, Ponton E. The costs of developing treatments for Alzheimer’s disease: A retrospective exploration. Alzheimers Dement. 2022 Mar;18(3):469-477. doi: 10.1002/alz.12450. Epub 2021 Sep 28. PMID: 34581499; PMCID: PMC8940715.

Further info

Leading the Hunt for Alzheimer’s Biomarkers

Everyone knows that Alzheimer’s and cognitive decline are preventable IF you can find out who is at risk. 

While those selling anti-amyloid or p’tau drugs will exaggerate the importance of blood testing for amyloid or p’tau, which are damaged proteins found in the brains of people with Alzheimer’s, so far lowering these markers hasn’t worked. In other words, they are a marker, but not a cause.

So, what is a biomarker that predicts risk? 

And therefore what biomarkers, if corrected, reduce risk?

To date, there are four:

Homocysteine, a toxic amino acid, which goes up when your intake of B vitamins (B6, B12, folate, as well as zinc) is low. If you then lower homocysteine with B vitamins, it stops the brain shrinkage associated with Alzheimer’s and improves cognitive function. Brain shrinkage stops below 10 mcmol/l, and that’s what you’re aiming for. So that’s both ‘biomarker’ and ‘causal’ ticked.

At Food for the Brain, we are offering the first accurate at home, pinprick test for homocysteine that is both painless and accurate.

Omega-3 index is another. This is the % of your red blood cell membranes that are omega-3 EPA and DHA. The higher your % (ideally above 8) the better your cognition. Low levels also predict risk. So that’s also two boxes ticked. 

Vitamin D is another. Low levels predict risk and supplementing it reduces risk. Again, two boxes ticked but we don’t really know how it does this.

Combining these three to make a ‘nutritional index’ shows that the better you score, the lower a person’s future risk of dementia is.

HBA1c is another. This is a measure of your blood sugar resilience. It measures the spikes in your blood sugar that then damage red blood cells. Below 5.4% (or 37 mmol/mol) is the idea.

We divide your scores across four levels – worst is RED, then ORANGE, then YELLOW, then GREEN, which is what you’re shooting for. 

That’s what our DRIfT test measures – all four as a Dementia Risk Index functional Test.

This chart shows you why these four measures are so essential. 

What about antioxidants?

But you might have noticed there’s no ‘antioxidant’ measure.

Well, actually there is. It’s the body’s most important antioxidant called glutathione. Think of it like the body’s fire department with glutathione being the water. Every time there’s an oxidant fire, glutathione rushes in to put the fire out. The water, then, turns into steam. Glutathione is called GSH. It’s not bad as a measure of ‘antioxidant potential’. That’s why most functional medicine doctors measure red blood cell glutathione. But what if it all gets used up? It becomes oxidised or spent, much like the water putting out a fire turns into steam. This is called oxidised glutathione or GSSG. Think of the fully loaded glutathione (GSH) as cold water. It’s going to protect you much better from inflammation than spent (oxidised) glutathione (GSSH), a highl level of which means you’ve been trying to put out a lot of inflammatory fires in your brain and body. Neuro-inflammation is a key driver of brain degeneration and dementia, as well as ageing in general, which is why this is important to know.

We’ve been researching the ratio that is your GSH/GSSG. If you’ve got lots of fully loaded glutathione, and very little oxidised/spent glutathione, your GSH/GSSG ratio or index is high. That’s good news. If you’ve got very little fully loaded glutathione and lots of oxidised glutathione then you’re ‘oxidising’ –  which is an aspect of ageing that we want to prevent.

We want to be able to research this and test your Glutathione Index. This is exactly what we are working on right now with the hope of releasing another ‘world first’ home test kit for your Glutathione Index soon. This kind of research is funded by you, as a Friend of Food for the Brain.

An example would be a person who smokes a lot, lives in a polluted environment, eats no fresh veg, berries, herbs and spices. Their Glutathione Index will be low and their body and brain will likely be ageing faster. If you did smoke but also ate well and took vitamin C daily, (they say you need 50mg of vitamin C for each cigarette) would that mitigate the effect? 

Would you join our research, support our charitable work and upgrade your own brain by ordering one of our DRIftT tests?

If you’ve also done the Cognitive Function Test and Dementia Risk Index questionnaire (which we strongly recommend) that’s even better because we can see how you score in the ANTIOXIDANT domain and in future, how that will correlate with your Glutathione Index (which is coming soon).

Further info

Alzheimer’s drugs – like statins for your brain?

Last month’s newspaper headlines pitched the new anti-amyloid Alzheimer’s drug as a ‘turning point’. The pitch has a lot in common with the statin story.

Last month’s newspaper headlines pitched the new anti-amyloid Alzheimer’s drug as a ‘turning point’. (Read our response here) The pitch has a lot in common with the statin story.

Is high cholesterol the cause of heart disease? No. 

Do statins lower it? Yes.

Are amyloid deposits the cause of cognitive decline? No. 

Do anti-amyloid drugs lower it? Yes.

No doubt there will be a blood test soon for amyloid, just like a blood test for cholesterol, the effect of which pushed millions into taking statins.

Both statins, given to people with very high cholesterol, and anti-amyloid drugs, given to people with very high amyloid levels, do have marginal benefit but not enough to establish causation. In the case of the new Alzheimer’s drug, the benefit is considerably less than half that shown by the combination of B vitamins and omega-3. 

But, even more than statins, they come with a high risk of quite serious adverse effects – over a third in the recent trial got brain bleeding or swelling and three died. Also, the whole brain shrinkage accelerated by twenty percent compared to placebo, a fact not reported in any newspaper. Any vitamin showing such adverse effects would be immediately banned.

But the important question is: what’s causing these diseases, be it cognitive decline or heart disease? To the extent that cholesterol or amyloid is relevant, what makes them go up? Cholesterol gets damaged by sugar and oxidants and is protected by antioxidants such as vitamin C and a low-carb diet. Brain cells get damaged by homocysteine and are protected by B vitamins and omega-3.

Mind the gap 

Also, in those with cognitive decline, there’s an energy deficit in brain cells. Ironically, they can’t get the glucose they need due to ‘insulin resistance’ which is driven by eating too much sugar and ultra-processed carbs. So, the effect of too much sugar is to starve the brain of fuel which then leads to mental tiredness and cognitive decline. 

There is a way around this – and that is to give the brain an alternative fuel – ketones. 

Ketones can either be supplied as ketone salts or esters, both of which taste disgusting or made from a type of fat – principally C8 oil, which is a medium-chain triglyceride. About 7 percent of coconut oil is C8. Studies giving people with cognitive decline a C8-rich MCT oil have shown clear improvements in cognition by increasing the brain’s energy supply and production. Ripping out amyloid deposits isn’t going to fill this energy gap. Eating less carbs, reversing diabetes, which is a big risk factor for dementia, and having C8 oil will. Our podcast with Professor Stephen Cunnane, who heads the Brain Research Team at Sherbrooke University in Sherbrooke, Quebec, Canada and holds the clinical research chair in ketotherapeutics and on the Food for the Brain Scientific Advisory Board, discusses this area with Patrick Holford – listen to the podcast here.

Also, in those with cognitive decline, there’s an energy deficit in brain cells. Ironically, they can’t get the glucose they need due to ‘insulin resistance’ which is driven by eating too much sugar and ultra-processed carbs. So, the effect of too much sugar is to starve the brain of fuel which then leads to mental tiredness and cognitive decline. 

An increase in amyloid in the brain is really a consequence of the disease, not the cause. It’s part of an inflammatory reaction, much like the nodules in joints that occur from inflammation resulting in arthritis. Should you cut out the nodules or reduce inflammation? Do you eliminate the root cause or target the consequences? Inflammation is both a function of a bad diet high in ultra-processed and fried food, smoking, lack of antioxidants, omega-3 fats and vitamin C to name a few key nutrients. Having an active lifestyle is also important.

The same story exists with all major diseases. Cancer cells thrive on sugar. Do you starve them and in the process protect healthy cells, or cut or drug them out?

The big difference in approach – treat the cause or the consequences – is money.  You can’t patent nutrients, but you can patent drugs that stop you from making cholesterol or amyloid. More than $1 billion has been spent on the anti-amyloid approach and the push isn’t going to stop. Pharma needs a return on their investment. This latest drug treatment, according to the Financial Times, will be sold for $26,000 a year. Taking B vitamins, eating fish and/or supplementing omega-3, which has shown more clinical benefit and reduced the rate of brain shrinkage by over 70% with no side-effects – actually side-benefits – might cost £100 a year. Which would you choose?

Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.

Test Your Cognitive Function Now green banner.
Further info

How the Guardian halves impact of prevention – and what steps make the biggest difference.

Friday’s Guardian article on ‘I refuse to get old’ about how readers strive to keep dementia at bay, on the face of it, seems like a good message. Most cases given focussing on people increasing physical and mental activity, as an active lifestyle is certainly a positive step towards prevention. But these two prevention steps reduce risk by less than B vitamins, omega-3 and reducing sugar and carbs.

The first error is the extent to which dementia can be prevented. The article says by 40%, which is based on the inaccurate Lancet Commission’s Livingston report which, despite being sent all the evidence, doesn’t even mention B vitamins and homocysteine, which is the single most important prevention step. There’s also only one mention of omega-3 from a redundant study so this risk factor is also ignored to arrive at the ‘40% preventable’ figure.

80% of dementia cases could be prevented, not 40%

The latest assessment of how much can be prevented, based on UK Biobank data is “47%–73% of dementia cases could be prevented.” This was published last week in Nature and even this is an underestimate because, while including B vitamins, it excludes the impact of omega-3 and seafood. If that modifiable risk factor were included it is likely that around 80% of dementia cases could be prevented. This would mean that the Guardian is halving the impact of prevention.

The next error is no-one quoted in the article mentions diet, let alone B vitamins or omega-3, except for Professor David Smith. He rightly says: ‘The large leap forward in what we know about preventability has informed his own retirement lifestyle: he walks for half an hour a day, spends at least 15 minutes on an exercise bike, drinks alcohol sparingly, and follows a Mediterranean diet.

Having led a clinical trial into the benefits of B vitamins in people with mild cognitive impairment – a memory-loss condition that increases the chance of those who have it developing dementia – Smith takes 500mcg of vitamin B12 daily and fish oil with Omega 3. Nutrition, he believes, is not given enough prominence when we talk about prevention.’

When we calculated the attributable risk for each risk factor for our online Dementia Risk Index questionnaire each domain scores as follows, adding up to 100%:

B Vitamins           18%

Brain Fats             17%

Glycemic Load     15%

Active Body          15%

Active Mind          10% 

Sleep & Calm       10%

Antioxidants         10%

Gut  Health          5%

So, the biggest impact you can have on your risk is to supplement B vitamins, especially B12, and omega-3 fish oils, as David Smith does. But the Guardian article then downplays the role of supplements with this statement ‘Alzheimer’s Research UK does not recommend any supplements in particular, but says “there is no harm in people taking a supplement to reduce the risk of deficiency”.

B12 Reference Ranges are wrong

This is not only wrong because brain shrinkage occurs well within the ‘normal’ range of either B12 dietary intake or blood tests, but also ARUK, who largely promotes drug-based solutions, happened to know what they are saying is wrong because they funded, back in 2010, a top level, randomised placebo controlled trial on B vitamins that, virtually stopped cognitive decline and reduced brain shrinkage by 52% – in the group with higher omega 3 , by 73% – that is the most effective disease modifying treatment to date! In fact, David Smith and I have written to ARUK to stop making this inaccurate statement. Here’s why it’s wrong:

The reason so many people are low in B12 is less to do with dietary intake and more due to malabsorption which often becomes worse with age, due to lack of stomach acid secretions which are needed to absorb B12. So relying only of analysing what someone eats (meat, fish, eggs, dairy being the only sources of B12) doesn’t prove sufficiency. Note that David Smith says he supplements 500mcg of B12 daily, while the basic ‘Nutrient Reference Value’ (NRV) that you’ll see on the back of a vitamin supplement is 2.5mcg. So, why does he take two hundred times this amount? Because you cannot rely on your dietary intake to confirm sufficiency. Also, there is growing body of evidence from well designed studies showing that supplements giving nutrients at levels beyond the basic ‘recommended intakes’ delay, eliminate or ameliorate symptoms of dementia.

So, what about blood tests? One UK study reports that 2 in five people over 61 have insufficient levels of B12 to prevent accelerated brain shrinkage. Serum B12 is the ‘standard’ test used by doctors. The UK reference range of above 180pg/ml being sufficient (and the US lower level of 200pg/ml) is out of date and in need of revision. In Europe and Japan anything below 500pg/ml is considered deficient. Accelerated brain shrinkage due to a lack of B12 does happen with B12 levels below 500pg/ml.

In conclusion, while it is good to recommend a physically and intellectually lifestyle, ignoring the need to supplement B vitamins, especially B12, eat fish and supplement omega-3, and cut your intake of carbs and sugar, is not doing anyone any favours.


Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.
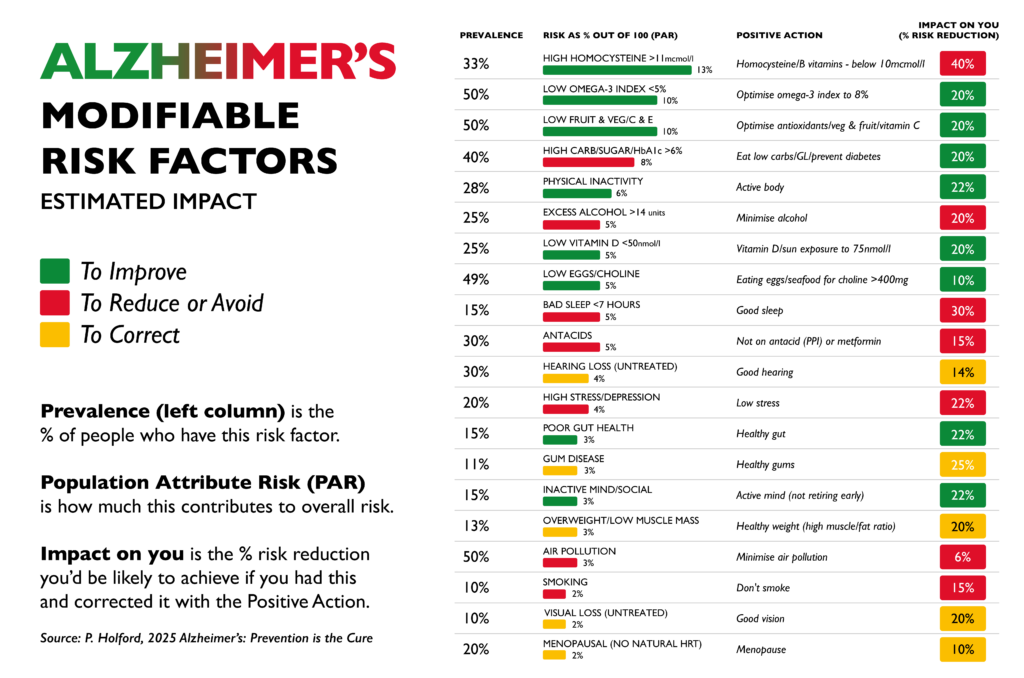

Test Your Cognitive Function Now green banner.
Further info

Is Autism Genetic?

Autism is one disease where there is a very high ‘inherited’ component.

In studies with genetically identical twins, if one twin has it, the odds of another having a diagnosis is about 60%. But it’s not in the ‘in the genes’ since we share the same ‘environment’ as our siblings.

Perhaps the more interesting question is why the number of children diagnosed with Attention-deficit /hyperactivity disorder (ADHD), autism and other neurodevelopmental disorders classifying them as ‘neurodivergent’, has rocketed in both the UK and US.

One in six children is ‘neurodivergent’ as autism numbers quadruple.

UK figures (see here) which show that just under 1.5 million pupils in England have special educational needs which is one in six children. Autism is the biggest part of this, has been steadily rising in both the Uk and US.

“Now, one in six children in the US are classified as neurodivergent and one in 36 as autistic – a fourfold increase in 20 years.” says pediatric Professor Alessio Fasano from Massachusetts General Hospital for Children, Harvard Medical School.  

All down to our increased awareness & better diagnosis?

According to Dr Rona Tutt OBE, past president of the UK’s National Association of Head Teachers “There has been a dramatic increase in the number of people being diagnosed with ASD. Although some of this is due to a broader definition of autism as well as better diagnosis, it raises the question of whether it may also be the result of environmental changes, which have also been dramatic.” 

Some UK schools are reporting as many as one in four children having problems.

Have our genes changed in the past few decades?

Since the genes cannot have changed this rapidly, the increase points to the influence of environmental factors of which there are many candidates.

The main suspects are:

  • Gut problems
  • Wheat, milk and sugar
  • Vaccines
  • Environmental anti-nutrients and toxins
  • Social media overuse and social issues
  • Maternal nutrition and brain formation essential fats 
The gut’s role

World-renowned pediatric gastroenterologist, and research scientist Professor Alessio Fasano, MD, directs the Center for Celiac Research and Treatment at Massachusetts General for Children thinks something is going wrong in the gut, with many ASD children reporting gut problems including diarrhoea, constipation, belching and excessive flatulence and ‘dysbiosis’ – abnormal patterns of gut bacteria. In some children, wheat and milk may contribute to these symptoms. His research finds that neurodivergent children show high levels of ‘zonulin’, a family of proteins that regulate the barrier between intestinal cells in the digestive tract that can lead to “leaky gut.” ASD children are often found to have opioid-like wheat and milk proteins in their urine, making these foods especially ‘addictive’.

Prenatal nutrition?

Professor Michael Crawford, who heads the Institute of Brain Chemistry and Human Nutrition at the Chelsea & Westminster Hospital says “We can predict which babies are going to have developmental problems from the fats in the mother’s blood. When omega-3 levels are low, the mother produces a non-functional ‘brain fat substitute’ to build their baby’s brain during pregnancy, high levels of which predict problems. The brain is 50% fat, and omega-3 DHA should make up most of the structural fat in brain cells.” Less than 5 per cent of children in the UK achieve the basic dietary recommendations for omega-3 and fish.

Methylation & B vitamins

Vitamins may help. ‘A high level of homocysteine, a marker for B vitamin deficiency, predicts ASD and studies have shown that giving homocysteine-lowering vitamin B6, B12 and folate help reduce symptoms.” says Patrick Holford from the Food for the Brain Foundation, which is hosting the masterclass. “Vitamin A improves eye coordination and vision, helping those with autism who don’t look you in the eye and have visual problems.”

A 12-month randomised controlled trial giving omega-3, vitamins, digestive enzymes and a healthy gluten-free, casein-free diet showed major improvement in both autistic symptoms and raising IQ.

Nutrition and functional medicine therapist Anne Pemberton, who specialises in helping those with ASD, is spoke at the Autism Masterclass reports considerable success, not just by improving nutrition but by addressing the psychological and social circumstances of neurodivergent children. “It is critical to work with both mother and child, and not only address critical nutritional issues, stress triggers including early life traumas, and suppressed emotions as a result of their condition and conditioning, and to help them develop a sense of self and mindset. I have seen hundreds of children and adults who usually have major improvements. Peter, age 8, is a case in point. He was diagnosed with ASD and classified as needing special education. 15 months later he’s no longer even classified as ASD.”

So, as you can see, there are many layers to Autism and Neurodivergence.

For more information you can:

Further info

Why aren’t Alzheimer’s charities taking prevention research seriously?

In the UK progress in putting these breakthroughs into action is slow. The two leading charities, the Alzheimer’s Society and Alzheimer’s Research UK (ARUK) fail to mention the importance of homocysteine lowering B vitamins and omega-3 at all and have confirmed that they are not funding any research on their use in prevention or planning to do so. ARUK’s chief medical officer Professor Jon Schott and the Alzheimer’s Society’s associate director of research, Richard Oakley, declined to comment.

ARUK’s Brain Health Check-In, a short 13 question check list, with only one very basic question on diet, says nothing at all about B vitamins or whether or not a person supplements omega-3 fish oils despite ARUK having part-funded the Oxford University research. According to Professor Smith, who was the first Chair of their Scientific Advisory Board “ARUK part-funded our trial on B vitamins, and are aware of the results. I don’t understand why they make no mention of such an effective preventive intervention, that is taking a 10p a day B vitamin supplement if your homocysteine is high. Now we know that those who also supplement with omega-3 fish oil, or eat fish regularly, reduce their risk. These are the easiest two prevention actions anyone can take, with a significant impact on reducing the risk for dementia. Everyone needs to know this.”

“We’ve been applying to UK and EU agencies for the past 8 years to fund the obvious next trial – testing the effects of B vitamins and omega-3 combined to see if they slow, or prevent, conversion from cognitive impairment to dementia, but to no avail.” Says Professor Smith.

Neither the Alzheimer’s Society, nor ARUK are funding any vitamin or omega-3 research and spend virtually none of their annual research pot, which exceeded £37 million last year, on diet or lifestyle prevention which offer the most potential, despite these representing up to half of the risk for Alzheimer’s. Neither would confirm the percentage of their research funds that were being spent on prevention research.

UK Government have pledged to deliver ‘Dementia Moonshot’, doubling dementia research funding to £160 million to ‘fast-track the development of new treatments’, meanwhile ignoring the biggest breakthroughs in diet and lifestyle prevention. Most support is feeding failed drug research. With an estimated $50 billion [12] spent so far on amyloid drugs and research, all of which have failed to produce any clinical benefit, isn’t it time governments and Alzheimer’s charities took prevention seriously?

In contrast, the Food for the Brain Foundation are doing just that. “At Foodforthebrain.org we are testing almost 4,000 people every month on our free online Cognitive Function Test, and assessing all risk factors on a 140 question questionnaire, including the need for B vitamins and omega-3. We hope, soon, to introduce a pinprick blood test for both omega-3 and homocysteine. We don’t know why the most evidence-based, easy to action and inexpensive prevention steps are being ignored” says Holford. “Why world class scientists such as Professor David Smith’s team at Oxford University have been unable to get funding for the most essential research is shameful. Right now we know enough to cut the average person’s risk of developing Alzheimer’s by up to two thirds and the number of people developing dementia by a third if only there was the political will to do so.”

One of the reasons for complacency in the UK is the Lancet’s commissioned report on Alzheimer’s prevention chaired by Gillian Livingston, Professor of Psychiatry for Older  People, at the University College London (UCL). The report, first published in 2017, didn’t include B vitamins. Despite being sent all the evidence by Smith. The 2020 revised report still excluded this vital research, as did a follow up report specifically on supplements in 2022. “There are no trials that show that lowering homocysteine has any benefit” she told us yet she had been sent the unequivocal evidence that the B vitamins reduced brain shrinkage by up to 73%, compared to the 2% reduction of anti-amyloid drugs and the combination of omega-3 and B vitamins has lowered the Clinical Dementia Rating (CDR) in placebo controlled trials by three times that reported by the recent anti-amyloid drug, Lecanemab. (see charts below).

When asked about the recent finding of a synergistic effect of B vitamins and omega-3 she said “It sounds a good hypothesis. I hope they can get the funding for it, but raised homocysteine is not common in the wider population and drug companies can’t be expected to fund nutrition trials, so money would have to come from some government agency.”

There is one prevention study, called AppleTree, underway at University College London. It focuses on reducing risk for Alzheimer’s by eating a Mediterranean style diet and lifestyle advice, including encouraging smokers to quit, which is a known risk factor for cognitive decline. One recent study shows that being a smoker increases risk for dementia by 1.5 times and quitting for at least 3 years reduces much of that risk. [13] One in twelve people over 65 smoke.

In contrast, almost half of all people over 65 have raised homocysteine [14] which increases risk for cognitive impairment by up to ten times, according to Chinese research published last year[15]. Lowering homocysteine with B vitamins, and sufficient omega-3, would virtually eliminate that risk. This suggests that targeting B vitamins and omega-3 would be about twenty times more impactful in preventing dementia than quitting smoking. Yet the need for supplemental intake of these nutrients is not part of the Apple Tree protocol.

If you’d like to test your cognitive function and find out how to reduce your risk, register here and join our citizen science campaign.

References

[3] van Soest, A.P.M., van de Rest, O., Witkamp, R.F. et al. DHA status influences effects of B-vitamin supplementation on cognitive ageing: a post-hoc analysis of the B-proof trial. Eur J Nutr (2022). https://doi.org/10.1007/s00394-022-02924-w

[4] Jernerén F, Cederholm T, Refsum H, Smith AD, Turner C, Palmblad J, Eriksdotter M, Hjorth E, Faxen-Irving G, Wahlund LO, Schultzberg M, Basun H, Freund-Levi Y. Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. J Alzheimers Dis. 2019;69(1):189-197. doi: 10.3233/JAD-181148. PMID: 30958356.

[5] Walsh S, Merrick R, Richard E, Nurock S, Brayne C. Lecanemab for Alzheimer’s disease. BMJ. 2022 Dec 19;379:o3010. doi: 10.1136/bmj.o3010. PMID: 36535691.

[6] Li M, Li W, Gao Y, Chen Y, Bai D, Weng J, Du Y, Ma F, Wang X, Liu H, Huang G. Effect of folic acid combined with docosahexaenoic acid intervention on mild cognitive impairment in elderly: a randomized double-blind, placebo-controlled trial. Eur J Nutr. 2021 Jun;60(4):1795-1808. doi: 10.1007/s00394-020-02373-3. Epub 2020 Aug 28. PMID: 32856190.

[7] Yu JT, Xu W, Tan CC, Andrieu S, Suckling J, Evangelou E, Pan A, Zhang C, Jia J, Feng L, Kua EH, Wang YJ, Wang HF, Tan MS, Li JQ, Hou XH, Wan Y, Tan L, Mok V, Tan L, Dong Q, Touchon J, Gauthier S, Aisen PS, Vellas B. Evidence-based prevention of Alzheimer’s disease: systematic review and meta-analysis of 243 observational prospective studies and 153 randomised controlled trials. J Neurol Neurosurg Psychiatry. 2020 Nov;91(11):1201-1209. doi: 10.1136/jnnp-2019-321913. Epub 2020 Jul 20. PMID: 32690803; PMCID: PMC7569385.

[8] Huang Y, Deng Y, Zhang P, Lin J, Guo D, Yang L, Liu D, Xu B, Huang C, Zhang H. Associations of fish oil supplementation with incident dementia: Evidence from the UK Biobank cohort study. Front Neurosci. 2022 Sep 7;16:910977. doi: 10.3389/fnins.2022.910977. PMID: 36161159; PMCID: PMC9489907.

[9] Jeong SM, Park J, Han K, Yoo J, Yoo JE, Lee CM, Jung W, Lee J, Kim SY, Shin DW. Association of Changes in Smoking Intensity With Risk of Dementia in Korea. JAMA Netw Open. 2023 Jan 3;6(1):e2251506. doi: 10.1001/jamanetworkopen.2022.51506. PMID: 36656579; PMCID: PMC9857334.

[10] Beydoun MA, Beydoun HA, Gamaldo AA, Teel A, Zonderman AB, Wang Y. Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 2014 Jun 24;14:643. doi: 10.1186/1471-2458-14-643. PMID: 24962204; PMCID: PMC4099157.

[11] Witte AV, Kerti L, Hermannstädter HM, Fiebach JB, Schreiber SJ, Schuchardt JP, Hahn A, Flöel A. Long-chain omega-3 fatty acids improve brain function and structure in older adults. Cereb Cortex. 2014 Nov;24(11):3059-68. doi: 10.1093/cercor/bht163. Epub 2013 Jun 24. PMID: 23796946.

[12] Cummings JL, Goldman DP, Simmons-Stern NR, Ponton E. The costs of developing treatments for Alzheimer’s disease: A retrospective exploration. Alzheimers Dement. 2022 Mar;18(3):469-477. doi: 10.1002/alz.12450. Epub 2021 Sep 28. PMID: 34581499; PMCID: PMC8940715.

[13] Lu Y, Sugawara Y, Zhang S, Tomata Y, Tsuji I. Smoking cessation and incident dementia in elderly Japanese: the Ohsaki Cohort 2006 Study. Eur J Epidemiol. 2020 Sep;35(9):851-860. doi: 10.1007/s10654-020-00612-9. Epub 2020 Feb 15. PMID: 32060675; PMCID: PMC7525275.

[14] Pfeiffer CM, Osterloh JD, Kennedy-Stephenson J, Picciano MF, Yetley EA, Rader JI, Johnson CL. Trends in circulating concentrations of total homocysteine among US adolescents and adults: findings from the 1991-1994 and 1999-2004 National Health and Nutrition Examination Surveys. Clin Chem. 2008 May;54(5):801-13. doi: 10.1373/clinchem.2007.100214. Epub 2008 Mar 28. PMID: 18375482.

[15] Teng Z, Feng J, Liu R, Ji Y, Xu J, Jiang X, Chen H, Dong Y, Meng N, Xiao Y, Xie X and Lv P (2022) Cerebral small vessel disease mediates the association between homocysteine and cognitive function. Front. Aging Neurosci. 14:868777. doi: 10.3389/fnagi.2022.868777


Further info

Most Dementia is Driven by Diet, Not Genes: The ApoE4 Exaggeration

Originally published on Orthomolecular Medicine News Service [15th February 2023]

In the days of Hippocrates, diseases were blamed on the gods. He didn’t buy that and explored the causes of disease saying ‘let food be thy medicine’. Nowadays a lot of diseases are being blamed on genes – because knowledge about genes and their effects has advanced tremendously over the last several decades. Genes are the code, or instructions, to assemble proteins, for example to make an enzyme, a hormone or a biochemical such as cholesterol or phospholipids.

Take Alzheimer’s, which accounts for two thirds of dementia, as an example. There are only three genes that can cause Alzheimer’s (APP, PSEN1, PSEN2), and these account for considerably less than one in a hundred cases of Alzheimer’s. [1]

There are, however, 76 other genes [2] which appear to confer a very small additional risk. Taken together, estimates suggest that 75-85% of the risk can be explained by combining these into a polygenic risk score. [3] The single greatest predictor is the presence of the ApoE4 variant of the ApoE gene, carried by about one in five people. It is considered to contribute 4 to 6% of the absolute risk for Alzheimer’s disease. [4,5]

This is often exaggerated as a risk factor because, if a person has the ApoE4 gene, and changes nothing, they have about a 20% greater chance of developing Alzheimer’s later in life than someone who doesn’t. This is called ‘relative risk’. It doesn’t mean, however, that someone with the ApoE4 gene has a 20% chance of developing Alzheimer’s. This is because, as an example, a person without the ApoE4 gene at a certain age might have a 5% chance of developing Alzheimer’s, while someone with the ApoE4 gene might have a 6% chance, so their risk has gone up by, in this example, 20%. In absolute terms, the risk would be only 1% higher.

Predicting risk and actually reducing risk with modifications of diet and lifestyle are two different things. The predictive risk for Alzheimer’s of having a low intake of seafood and/or omega-3 fats is 22%, and so is having a low intake of B vitamins resulting in a high blood homocysteine level. Smoking confers a similar risk. [6] Other big risk factors are an inactive lifestyle and low level of education. Add in predictive genes and apparent risk adds to well over 100% partly because there is overlap.

But the only way to find out how much you can actually reduce a person’s risk by is to either conduct ‘observational’ studies looking at, e.g. smokers vs non-smokers, or people with a good versus a bad diet, and see how many develop dementia. Even better is to change something, such as looking at what happens when a person stops smoking, or supplements omega-3 fish oils or homocysteine lowering B vitamins.

Modifying ApoE4 with orthomolecular medicine

All these so-called Alzheimer’s genes, with the exception of the causative ones, can only exert effects via non-genetic mechanisms and these mechanisms are often susceptible to modification with a person’s nutrition having the most direct influence. In other words, gene variants that are present are not either active or inactive. Even if you have a gene variant such as ApoE4 it is more like a dimmer switch and can be ‘over-expressed’ or ‘down-regulated’, turned up or dimmed down. That is why approximately half of women with the BRCA gene develop breast cancer and half don’t. The environment the gene is exposed to makes all the difference.

The expression and harmful effects of the ApoE4 gene appear to be downregulated by eating a low-glycemic load (GL) diet or a more ketogenic diet with specific Mediterranean-style food choices including fatty fish, cruciferous vegetables, olive oil, and low alcohol consumption. Six supplemental nutrients have reasonably good evidence of down-regulating ApoE4. These are omega-3 DHA, B vitamins (B2, B6, B12 and folate) vitamins D3 and K2, quercitin and resveratrol. [7] This approach to modifying the effects of the genes we inherit with personalised nutrition is a fundamental tenet of orthomolecular medicine, sometimes called personalised, precision or optimum nutrition.

But what happens to risk if a person is doing these things already? A good example of this is a recent study in China, involving 29,072 people of which 20% had the ApoE4 gene. [8] Each participant had their diet and lifestyle assessed over the 10 year period of the study to see who would or wouldn’t develop cognitive decline or dementia.

The study showed that whether or not a person had the ApoE4 ‘Alzheimer’s gene’ made no difference to the positive reduction in risk achievable by simple diet and lifestyle changes. “These results provide an optimistic outlook, as they suggest that although genetic risk is not modifiable, a combination of more healthy lifestyle factors is associated with a slower rate of memory decline, regardless of the genetic risk,” wrote the study authors.

Eating a healthy diet was the most important prevention step, followed by an active lifestyle, with one’s intellectual life, then physical activity, then social interactions being the next most important steps. Eating a healthy diet was about twice as important as exercise in predicting cognitive decline. Those with a healthy diet were about seven times less likely to have age-related cognitive decline or dementia than those with an ‘average’ diet and about nine times less likely to develop dementia than those with an unfavorable diet.

The assessment of a healthy diet was based on intake of fish, eggs, fruits, vegetables, legumes, nuts and tea, among other foods known to predict lower risk.

B vitamins modify methylation of genes linked to dementia

Other Alzheimer’s related genes affect a process called methylation. Healthy methylation depends on adequate B vitamin intake, primarily B6, B12 and folate. Inheriting a variant of a key methylation gene, MTHFR 677TT increases risk for Alzheimer’s. [9-11] About one in three people have this gene variant. It impacts risk by raising homocysteine, a toxic amino acid that damages the brain and blood vessels. Having a raised homocysteine level increases risk for cerebrovascular dysfunction 17-fold. [12]

Since methylation is needed to make phospholipids, biochemicals essential for the brain also found in eggs and fish, having a poor diet in this respect creates more methylation demand and, consequently, greater need for B vitamins.

In a placebo controlled study of older people with mild cognitive impairment, about a third of participants had the MTHFR variant that increases Alzheimer’s risk. But supplementing with B vitamins effectively lowered homocysteine in both those with and without this ‘Alzheimer’s’ gene. The B vitamin supplement almost arrested further memory decline and slowed the rate of brain shrinkage by 52%, [13,14] reducing shrinkage of the Alzheimer’s areas of the brain by 9-fold. [15] Whether a person did or didn’t have this ‘Alzheimer’s’ gene made no difference to the beneficial effect of the B vitamins.

Those with adequate omega-3 blood levels had even less brain shrinkage – 73% less than the placebo group. [16-17] Two other studies have found major protection either by giving B vitamins to those with adequate omega-3 intake, [18] or by supplementing omega-3 to those with lower homocysteine levels [19] further confirming that you need both B vitamins and omega-3 fats to keep neurons healthy – an example of synergy – regardless of one’s genes. Whether a person did or didn’t have the MTHFR variant made no significant difference.

Too often genes are blamed as drivers of disease even though (with the exception of rare causative genes) the primary drivers are what you put in your mouth or how you live your life – both factors under our control. For example, DNA genetic testing can cause panic when an individual is informed they have a dozen or more gene variants. Over-emphazing the importance of genes discourages people from preventing their own disease by improving diet and lifestyle.

Find out your dementia risk

Cognitive Function Test Results

You can find out what’s driving your risk and which diet and lifestyle changes will make the biggest difference by doing the Cognitive Function Test at foodforthebrain.org and joining COGNITION, the brain upgrade program. Not only do you help yourself, you also help the hundreds of thousands of people who would benefit from the research we support at Food for the Brain to reduce risk of dementia.

About Patrick Holford

(Patrick Holford , BSc, DipION, FBANT, NTCRP is widely published and a member of the Orthomolecular Medicine Hall of Fame. He is the director of the non-profit, UK-based “Alzheimer’s is Preventable” campaign [ foodforthebrain.org].)

References

1. Bekris LM, Yu CE, Bird TD, Tsuang DW. (2010) Genetics of Alzheimer disease. J Geriatr Psychiatry Neurol. 23:213-227. https://pubmed.ncbi.nlm.nih.gov/21045163

2. Bellenguez C, Küçük F, Jansen IE, et al. (2022) New insights into the genetic etiology of Alzheimer-s disease and related dementias. Nat Genet. 54:412-436. https://pubmed.ncbi.nlm.nih.gov/35379992

3. Escott-Price V, Myers AJ, Huentelman M, Hardy J. (2017) Polygenic risk score analysis of pathologically confirmed Alzheimer disease. Ann Neurol. 82:311-314. https://pubmed.ncbi.nlm.nih.gov/28727176

4. Heininger K (2000), A unifying hypothesis of Alzheimer’s disease. III. Risk factors. Hum Psychopharmacol Clin Exp. 15:1-70. https://pubmed.ncbi.nlm.nih.gov/12404343

5. Ridge PG, Mukherjee S, Crane PK, Kauwe JSK, (2013) Alzheimer’s Disease: Analyzing the Missing Heritability. PLoS One. 8(11): e79771. https://pubmed.ncbi.nlm.nih.gov/24244562

6. Beydoun MA, Beydoun HA, Gamaldo AA, et al. (2014) Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 14:643. https://pubmed.ncbi.nlm.nih.gov/24962204

7. Norwitz NG, Saif N, Ariza I.E, Isaacson RS (2021) Precision Nutrition for Alzheimer’s Prevention in ApoE4 Carriers. Nutrients 13:1362. https://pubmed.ncbi.nlm.nih.gov/33921683

8. Jia J, Zhao T, Liu Z et al. (2023) Association between healthy lifestyle and memory decline in older adults: 10 year, population based, prospective cohort study. BMJ 380:e072691. https://pubmed.ncbi.nlm.nih.gov/36696990

9. Morris AA, Kožich V, Santra S, et al. (2017) Guidelines for the diagnosis and management of cystathionine beta-synthase deficiency. J Inherit Metab Dis. 40:49-74. https://pubmed.ncbi.nlm.nih.gov/27778219

10. Bouguerra K, Tazir M, Melouli H, Khelil M. (2022) The methylenetetrahydrofolate reductase C677T and A1298C genetic polymorphisms and plasma homocysteine in Alzheimer’s disease in an Algerian population. Int J Neurosci. 29:1-6. https://pubmed.ncbi.nlm.nih.gov/36580407

11. Zuin M, Cervellati C, Trentini A, et al. (2021) Methylenetetrahydrofolate reductase C667T polymorphism and susceptibility to late-onset Alzheimer’s disease in the Italian population. Minerva Med. 112:365-371. https://pubmed.ncbi.nlm.nih.gov/32700867

12. Teng Z, Feng J, Liu R, et al. (2022) Cerebral small vessel disease mediates the association between homocysteine and cognitive function. Front. Aging Neurosci. 14:868777. https://pubmed.ncbi.nlm.nih.gov/35912072

13. Smith AD, Smith SM, de Jager CA, et al. (2010) Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment: a randomized controlled trial. PLoS One. 5(9):e12244. https://pubmed.ncbi.nlm.nih.gov/20838622

14. Smith AD, Refsum H. (2016) Homocysteine, B vitamins, and cognitive impairment. Annu Rev Nutr. 36: 211-239. https://pubmed.ncbi.nlm.nih.gov/27431367

15. Douaud G, Refsum H, de Jager CA, et al. (2013) Preventing Alzheimer’s disease-related gray matter atrophy by B-vitamin treatment. Proc Natl Acad Sci USA 110:9523-9528. https://pubmed.ncbi.nlm.nih.gov/23690582

16. Jernerén F, Elshorbagy AK, Oulhaj A, et al. (2015) Brain atrophy in cognitively impaired elderly: the importance of long-chain omega-3 fatty acids and B vitamin status in a randomized controlled trial. Am J Clin Nutr. 102:215-221. https://pubmed.ncbi.nlm.nih.gov/25877495

17. Oulhaj A, Jernerén F, Refsum H, et al. (2016) Omega-3 fatty acid status enhances the prevention of cognitive decline by B vitamins in Mild Cognitive Impairment. J Alzheimer’s Dis. 50:547-557. https://pubmed.ncbi.nlm.nih.gov/26757190

18. van Soest, A.P.M., van de Rest, O., Witkamp, R.F. et al. (2022) DHA status influences effects of B-vitamin supplementation on cognitive ageing: a post-hoc analysis of the B-proof trial. Eur J Nutr. 61:3731-3739. https://pubmed.ncbi.nlm.nih.gov/35704085

19. Jernerén F, Cederholm T, Refsum H, et al. (2019) Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. J Alzheimers Dis. 69:189-197. https://pubmed.ncbi.nlm.nih.gov/30958356

Further info

Does HRT help prevent dementia?

A recent study of 1,178 women found that those carrying the APOE4 gene taking Hormone Replacement Therapy (HRT) had a better delayed memory score compared to APOE4 carriers that were not taking HRT, and to non-APOE4 carriers.[1] They also had slightly larger brain volumes in certain areas. This study suggested that HRT may help to prevent Dementia. This study was an observational trial, not a clinical trial, meaning the statement remains a hypotheses and requires further randomised controlled trials to investigate further. We analysed the paper and provided our comments below.

Hormone Replacement Therapy (HRT) are synthetic hormones commonly prescribed to menopausal women to reduce menopausal symptoms

Clinical Trials on HRT

Clinical trials to date have not shown benefit of HRT with improving cognitive function. A systematic review of the clinical trial evidence for the effect of HRT on cognitive outcomes did not find benefit.[2] The Women’s Health Initiative Memory Study (WHIMS) conducted a double-blind, placebo-controlled clinical trial examining 8300 women 65 years of age or older over a 2- year period to observe the effects of HRTs and dementia progression. The trial failed to find a beneficial effect for HRT in reducing dementia risk, instead finding an increase in all types of dementia.[3]

The ApoE4 Gene

Roughly 1 in 5 people carry the ApoE4 gene, which accounts for 4 to 6% of risk for dementia and can be modified, downregulating the gene, with positive diet, nutritional supplement and lifestyle changes.[1]

Find out your risk for Dementia

In our Dementia Risk Index, as part of the Cognitive Function test, and COGNITION programme to reduce dementia, we excluded HRT because the evidence was not conclusive or consistent.


Have you tried our free Cognitive Function Test yet? Find out your Alzheimer’s disease risk using our evidence backed Dementia Risk Index. If your risk is high, our clever new programme COGNITION can help you make the right nutrition and lifestyle changes to help improve your score.

The 8 Domains of the Dementia Risk Index from The Cognitive Function Test

References

[1] Saleh RNM, Hornberger M, Ritchie CW, Minihane AM. Hormone replacement therapy is associated with improved cognition and larger brain volumes in at-risk APOE4 women: results from the European Prevention of Alzheimer’s Disease (EPAD) cohort. Alzheimers Res Ther. 2023 Jan 9;15(1):10. doi: 10.1186/s13195-022-01121-5. PMID: 36624497; PMCID: PMC9830747.

[2] Marjoribanks J, Farquhar C, Roberts H, Lethaby A, Lee J. Long-term hormone therapy for perimenopausal and postmenopausal women. Cochrane Database Syst Rev. 2017;1(1):CD004143.

[3] Shumaker SA, Legault C, Rapp SR, et al. Estrogen plus progestin and the incidence of dementia and mild cognitive impairment in post- menopausal women: the Women’s Health Initiative Memory Study: a randomized controlled trial. JAMA. 2003;289(20):2651-2662.

Further info