because prevention is better than cure.

because prevention is better than cure.

Mini Cart 0

Your cart is empty.

Mini Cart 0

Your cart is empty.

New Study: Is Red Meat Bad for Your Brain?

New Study: Is Red Meat Bad for Your Brain?

New Study: Is Red Meat Bad for Your Brain?

In a culture where the average plate still leans heavily towards meat – often processed, often excessive – it’s time to reassess the impact of our protein choices not just on our waistlines, but on our brains. A recent study in Neurology (2025) has added fresh weight to decades of evidence linking red and processed meat consumption to an increased risk of dementia and cognitive decline (1). Meanwhile, fish – particularly oily fish – continues to top the charts as the most protective food for your brain (2,3).

So, what does this mean practically for those of us trying to upgrade our brains and reduce our risk of cognitive decline? The answer may be as simple as this: eat more fish and fewer sausages.

Red Meat, Processed Meat and the Rising Risk to Brain Health

A new US cohort study, which followed over 77,000 adults across 30 years, found that:

  • Processed red meats (bacon, hot dogs, sausages, salami, bologna and other processed meat products) were clearly problematic. Consuming just 0.25 servings per day or more was associated with a 13% higher risk of developing dementia compared with those eating less than 0.1 serving (1).
  • Unprocessed red meat (e.g. beef or lamb) was linked to a 16% increased risk of subjective cognitive decline – that is people reporting that their memory or mental sharpness was worsening – when consuming more than one serving daily compared to less than half a serving per day. However, the researchers noted that this link did not reach statistical significance for diagnosed dementia overall (1).
  • More encouragingly, replacing one daily serving of processed red meat with a serving of nuts, lentils, or beans was associated with a 19% lower risk of dementia (1).

These findings are consistent with a large UK Biobank analysis of almost half a million adults, which found that each additional 25 g/day of processed meat (bacon, ham, sausages, meat pies, kebabs, burgers, chicken nuggets) was associated with a 44% higher risk of all-cause dementia and a 52% higher risk of Alzheimer’s disease. In contrast, each 50 g/day of unprocessed red meat was linked to a 19% lower risk of all-cause dementia and a 30% lower risk of Alzheimer’s disease (4).  This reinforces the idea that it is the processing – not necessarily the meat itself – that may be most harmful.

These associations were observed regardless of whether participants carried the APOE ε4 gene variant – further evidence that dietary choices have a significant impact and that Alzheimer’s is ‘not in the genes’. (4).

The Global Pattern

The irrelevance of genetics in these findings is further supported by global evidence. An ecological analysis across 204 countries found that higher national per-capita total meat supply – including both red and white meats – was significantly associated with higher dementia incidence, even after adjusting for ageing, economic development and genetic risk, including APOE ε4 prevalence where available (5). In other words, the meat-dementia link is not confined to particular genetic subgroups but is observable across populations worldwide, suggesting that the way we produce and consume meat may be influencing brain health trends on a global scale. 

What we put on our plate is powerful when it comes to reducing dementia risk – more so than any genetic variations that attract attention in the media.

Why Fish is Brain Food

The answer is not to go hungry, but to swap for something else – and when it comes to brain health, marine foods are your answer.

Unlike red meat, fish – especially oily varieties like salmon, sardines or mackerel – continue to show a strong protective effect.

A comprehensive 2024 meta-analysis found that:

  • Eating one to two servings of fish per day (roughly 150 g) is associated with a 20% reduced risk of Alzheimer’s disease and up to 30% slower cognitive decline (2).
  • Another study found that people who ate fish at least once a week had a one-third lower risk of Alzheimer’s compared with those eating fish less than weekly (3).

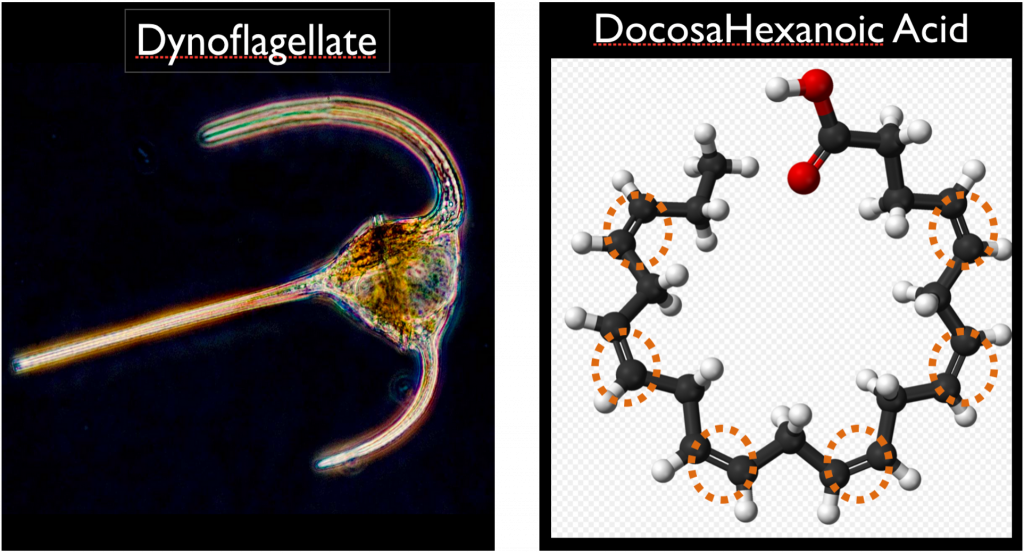
Why? Omega-3 fats, especially DHA, are critical for brain function and structure. They reduce inflammation, support synaptic plasticity and help clear beta-amyloid – a protein associated with Alzheimer’s disease.

As explained in the COGNITION™ 6-month programme, omega-3 fats from fish oil play a pivotal role in building and repairing the brain, particularly in mid-life, when early signs of cognitive decline can start to emerge.

That’s why we offer omega-3 at-home blood tests – so you can check whether you’re getting enough through your diet or if it’s time to add a supplement. You can test omega-3 on its own here, or as part of our 5-in-1 DRIfT test where you can also check your homocysteine and glutathione status at the same time.

A Simple Swap with Profound Impact

From a cognitive health perspective, the data is now hard to ignore: if you’re regularly eating red or processed meat – especially more than once a day – your brain may be paying the price. But shifting even one of those servings towards fish, eggs or plant-based proteins could make a meaningful difference.

Interestingly, the main culprit in the latest studies was processed meat. This supports a key principle in brain-friendly eating: most natural whole foods – whether meat, fish, fruit, nuts, legumes, wholegrains or dairy – are not the problem. It’s when we distort them into ultra-processed, factory-made food that health is undermined.

This isn’t about becoming vegan or pescatarian. It’s simply more evidence to reduce processed foods and ensure optimal omega-3 intake. 

So next time you’re at the supermarket make a cow happy and buy a fish.

Resources:

Order your omega-3 test today to find out if you are eating enough of these essential fatty acids. You can test omega-3 on its own here, or as part of our 5-in-1 DRIfT test. Available globally.

References:

You J, Zhang L, Zhou Y, et al. Total meat supply and incidence of dementia: an ecological study of 204 countries. Front Public Health. 2025;13:1589936. doi:10.3389/fpubh.2025.1589936.

Li Y, Li Y, Gu X, Liu Y, Dong D, Kang JH, Wang M, Eliassen H, Willett WC, Stampfer MJ, Wang D. Long-Term Intake of Red Meat in Relation to Dementia Risk and Cognitive Function in US Adults. Neurology. 2025;104(3):e210286. doi:10.1212/WNL.0000000000210286.

Godos J, Micek A, Currenti W, Franchi C, Poli A, Battino M, Dolci A, Ricci C, Ungvari Z, Grosso G. Fish consumption, cognitive impairment and dementia: an updated dose-response meta-analysis of observational studies. Aging Clin Exp Res. 2024;36(1):171-182. doi:10.1007/s40520-024-02823-6.

Beydoun MA, Beydoun HA, Gamaldo AA, Teel A, Zonderman AB, Wang Y. Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 2014;14:643. doi:10.1186/1471-2458-14-643.

Zhang Z, He P, Liu M, et al. Meat consumption and risk of incident dementia: cohort study of UK Biobank participants. Am J Clin Nutr. 2021;113(5):1228-1236. doi:10.1093/ajcn/nqaa343.

Further info

Groundbreaking New Research: The Key to Reducing Dementia Risk

by Cath Verner

A landmark study from the Centre for Healthy Brain Ageing (CHeBA) at the University of New South Wales (Sydney, Australia) has provided compelling evidence that targeted diet and lifestyle changes can improve cognitive function in older adults. 

Or put simply, what we teach and promote at Food for the Brain works when it comes to promoting brain health.

Raising awareness and providing tools to support the critical role of diet and lifestyle in long-term cognitive health is both essential and part of the solution.

This recent study affirms our approach: sustained step-by-step adjustments to diet, exercise, sleep, and social engagement significantly reduces the risk of dementia as well as maintaining – and even enhancing – cognitive function.

Study shows a holistic approach to brain health works

The CHeBA study recruited over 6000 adults aged 55 to 77, dividing them into two groups, one participating in an online lifestyle intervention programme and the other serving as a control group.

  • Physical activity (strength and balance training), 
  • Brain training (three weekly cognitive training sessions), 
  • Mediterranean diet (rich in plant foods and healthy fats with limited meat and dairy), 
  • Mental well-being (a digital anxiety and depression reduction program).

While both groups showed some cognitive improvements, those in the intervention group experienced significantly greater gains, demonstrating the added value of a structured, multi-domain approach.

Professor Brodaty, one of the study’s research team, stated:

“Participants aged 55-65 showed greater improvement than those aged 66-77, suggesting that prevention programmes should start earlier.”

Why a Multi-Domain Approach Works!

Unlike traditional approaches that focus on just one or two factors, the COGNITION® Programme, which you get access to when you become a FRIEND of Food for the Brain, is similarly built on eight interwoven pillars—including diet, physical exercise, sleep, social involvement, and even the gut microbiome—to provide a comprehensive brain health plan.

The study’s ‘Maintain Your Brain’ trial further supports this, showing that targeting multiple lifestyle domains simultaneously – including physical activity, nutrition, brain training, and mental well-being – leads to greater cognitive benefits, rather than focusing on a single risk factor.

And, as we always say, the earlier you start, the better!

Before and after images of the Cognition cog.
Your Roadmap to the 8 Pillars of Cognitive Health

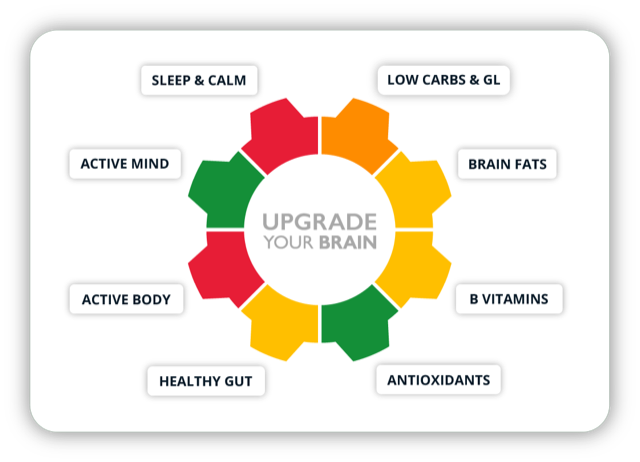
In line with this study, we focus on 8 key domains that influence brain health. These areas provide strategies to help individuals reduce their risk of cognitive decline and support long-term brain health:

Domain 1: Low Glycemic Load (GL) Diet – Managing blood sugar levels is crucial for brain function. High-sugar diets contribute to inflammation and insulin resistance, impairing cognitive performance. A low-GL diet helps stabilise energy levels and protects brain cells from damage

Domain 2: B Vitamins & Homocysteine Levels – High homocysteine levels, a by-product of metabolism, are linked to cognitive decline. Ensuring adequate B vitamins (B6, B12, and folate) supports brain function and lowers homocysteine levels.

Domain 3: Brain-Boosting Fats – Healthy fats like omega-3s (found in fish, flaxseeds, and walnuts) are essential for brain cell structure and function. They help reduce inflammation, enhance memory, and support cognition.

Domain 4: Antioxidants & Polyphenols – Free radicals damage brain cells, but antioxidants (from colourful fruits, vegetables, green tea, and dark chocolate) help combat oxidative stress and keep your brain young.

Domain 5: Healthy Gut & Microbiome – The gut-brain connection is vital for mental clarity and mood. A diverse microbiome (supported by fibre-rich foods, fermented foods, and probiotics) can reduce inflammation and improve neurotransmitter function, supporting memory and mental health.

Domain 6: Active Body (Exercise & Movement) – Regular physical activity boosts blood flow to the brain, supports neuroplasticity, and reduces the risk of dementia. Both aerobic exercise (like walking and cycling) and strength training play a role in maintaining cognitive health.

Domain 7: Active Mind – The brain thrives on challenge! Lifelong learning, problem-solving activities, and hobbies stimulate new neural connections and help build cognitive resilience.

Domain 8: Sleep & Stress Resilience Management – Poor sleep and chronic stress are major contributors to cognitive decline. Deep, restorative sleep allows the brain to clear toxins, while mindfulness, relaxation techniques, and breathing exercises help reduce stress hormones that damage brain cells.

__

We know that these 8 domains can help you protect your brain and prevent cognitive decline – but most of us need support, accountability, motivation and structure to be able to implement the necessary changes consistently.

That is why the  COGNITION® Programme exists.

It’s designed to make implementing the above easier and simpler, one step at a time. By providing tailored advice and guidance on all eight areas, the programme offers tangible, practical steps that members can take to enhance brain function, reduce dementia risk, and improve overall cognitive well-being.

Real-Life Results…

As a research charity with a stellar scientific advisory board, we care about excellent research being carried out. 

Yet the most important thing is that ‘the science’ helps to transform lives, families and communities. Citizen science in action!

Here is what can happen when you join COGNITION. One participant told us:

“I have taken the CFT for at least seven years now and find it very worthwhile.
By monitoring sensibly what I eat, as you advise and exercising within my limitations, I have found that despite being 84, my results have improved.”

This experience is echoed by another participant who found benefit in making small, sustainable lifestyle changes every day:

I’ve taken on board your recommendations and I’ve increased my vitamin B intake and started doing puzzle books every day to keep my brain active in different ways from before. I also do more exercise and yoga daily. I love the fact that I can make these small changes myself and hopefully reduce my chances of getting dementia.”

Another participant shared how working with Food for the Brain and starting with the COGNITION® Programme was a wake-up call that led to lasting changes:

Since starting with Food for the Brain, I’ve completely reshaped my lifestyle. I now attend a weekly Pilates class, work on my allotment, swim regularly, and take longer evening walks. I’ve also cut down on alcohol and meat, increased my vitamin B intake, and started doing daily puzzles to challenge my brain in new ways. My sleep has improved and I feel more energetic with fewer foggy days.”

These testimonials show how small, targeted lifestyle changes can significantly enhance cognitive resilience and well-being. The COGNITION® Programme equips individuals with the necessary tools to take charge of their brain health, which leads to improved cognitive test scores, better mental clarity, and a greater sense of control over their future.


Join the COGNITION® Programme today!

As a non-profit charity we aim to make resources affordable and accessible to all, while covering essential staff and research costs. Membership of the 8-domain COGNITION® Programme is just £50 per year or £5 per month, ensuring that everyone can benefit from the programme.

You get access to the programme when you become a FRIEND of Food for the Brain.

Members receive:

  • Guidance on which domains to target based on their test results.
  • Ongoing cognitive assessments to track progress.
  • Access to expert-backed articles for long-term brain health.
  • Access to regular group coaching and Q&A sessions.

How it works:

  • Become a FRIEND here
  • Complete the FREE Cognitive Function Test* to get personalised insights and The COGNITION Programme.
  • Pick one domain to work on each month for six months, attend live coaching calls and watch as your brain health improves!

*You do not need to be a FRIEND to do this test.

Start today!

Your brain health is in your hands.

Further info

Lack of Omega-3 is a Major Cause of Increased Aggression, New Study Shows…

Widespread omega-3 deficiency is cranking up aggression.

Children flying off the handle, fighting at school, increasing rates of ADHD, depression and violent offences, perhaps even more global conflicts – a new study suggests that something very simple could be cranking up aggression. 

Less omega-3 from seafood. 

A study of 4,000 participants over 28 years, has found a clear reduction in aggression when children and adults are given either omega-3 supplements or eat more fish. According to advisor to the US National Institutes of Health, Dr Joseph Hibbeln, a country’s incidence of homicide, depression and suicide ‘tracks’ their seafood consumption. In Australia, a prisoner’s omega-3 index, measured in a pin prick blood test predicts anger, aggression and AHDH. A study in UK prisons found that giving omega-3 supplements to prison inmates, compared to placebos, reduced violent offences by more than a third.

Omega-3 support in community, clinics and our criminal justice system

“Based on this evidence our considered opinion is that there is now sufficient evidence to begin to implement omega-3 supplementation to reduce aggression in children and adults, whether the setting is community, the clinic or criminal justice system” say the study authors Adrian Raine and Lia Brodrick from the University of Pennsylvania.

“There is now clear evidence that not only are low blood omega-3 levels associated with increased aggressive behaviour but supplementation with fish oil can reduce aggressive tendencies in adults and children.” says Professor William Harris from the Fatty Acid Research Institute in the US, one of our scientific advisors

This is why we now offer an easy, pin prick home test for omega-3 to go alongside our free online Cognitive Function Test and diet and lifestyle questionnaire that assesses omega-3 status and other factors that are important to your brain function and development.

We need to treat it the same as vitamin D

“Less than 5% of children in the UK achieve the basic recommended levels of omega-3” says Dr Simon Dyall, clinical neuroscientist at the University of Roehampton who also advises the charity “Even these recommendations are too low, according to the evidence regarding brain function. Many children eat no fish at all and don’t supplement omega-3. The evidence is more than sufficient to recommend that we take action now to protect our children’s brains.”

In the same way that GPs test vitamin D we need to test both children and adults presenting with ADHD, depression, anxiety and aggression for their omega-3 index. 

In Japan, where a lot of seafood is eaten, the level is 10% and rates of violence, depression, suicide and Alzheimer’s are a fraction of those in the UK. People in the UK and US average 4% on the pinprick omega-3 index. You need over 8% for a healthy brain. Many offenders test as low as 2%.

You can’t build a healthy brain without omega-3. Our children are suffering. There is more than enough evidence of this.

Yet there is no government recommendation in the UK of how much omega-3 we need. The advice to eat fish twice a week is neither enough, nor heeded. 

That is why we are helping people help themselves by testing their omega-3 index and advising them accordingly. But we need this done on a national scale, especially in poorer communities.

If doctors can test and prescribe vitamin D, why can’t they test and prescribe omega-3?

Actions:

References

A. Raine, L. Brodrick ‘Omega-3 supplementation reduces aggressive behavior: A meta-analytic review of randomized controlled trials’Aggression and Violent Behavior, 2024, 101956 doi.org/10.1016/j.avb.2024.101956.

Hibbeln JR. Depression, suicide and deficiencies of omega-3 essential fatty acids in modern diets. World Rev Nutr Diet. 2009;99:17-30. doi: 10.1159/000192992.

Meyer BJ, Byrne MK, Collier C, Parletta N, Crawford D, Winberg PC, et al. (2015) Baseline Omega-3 Index Correlates with Aggressive and Attention Deficit Disorder Behaviours in Adult Prisoners. PLoS ONE 10(3): e0120220. doi:10.1371/ journal.pone.0120220 

Gesch CB, Hammond SM, Hampson SE, Eves A, Crowder MJ. Influence of supplementary vitamins, minerals and essential fatty acids on the antisocial behaviour of young adult prisoners. Randomised, placebo-controlled trial. Br J Psychiatry. 2002 Jul;181:22-8. doi: 10.1192/bjp.181.1.22.

Further info

Dementia’s projected £91 billion can be ‘halved’ with prevention

Yesterday’s announcement by the Alzheimer’s Society that dementia will cost the UK almost £91bn a year by 2040 highlights why prevention has to be the way forward. (See the Guardian Article here

“Dementia’s devastating impact is colossal – on the lives of those it affects, on the healthcare system and on the economy”, said Kate Lee, the Alzheimer’s Society’s chief executive who is calling for the ‘urgent need to prioritise early diagnosis.’ We know here at Food for the Brain, that these costs, could easily be halved by focussing on prevention. A recent study from the UK Biobank data and conducted by two of the charity’s scientific advisors, China’s leading dementia prevention Professor Jin-Tai Yu from Fudan University, and by former deputy head of Oxford University’s school of medical science, Professor David Smith, concluded that “up to 73% of dementia can be prevented” right now by focussing on prevention. (1) The Biobank research, however, didn’t measure homocysteine and thus excluded one of the most easily actioned prevention steps – lowering homocysteine with B vitamins – which the US National Institutes of Health says accounts for 22% of the risk for Alzheimer’s. (2)

Patrick Holford our CEO says “the reality is that over 80 percent of dementia could be prevented right now if we took prevention seriously. The quickest wins are testing people, for free, for cognitive function then identifying those at risk and why they are at risk. Dementia is diagnosed with a cognitive function test and changes occur at least thirty years before a diagnosis. This is doable right now with no cost at all.” We have tested 425,000 people to date with 200 taking the free, validated test every day. This is followed by a ‘cognition’ questionnaire that shows the person exactly what is driving their future risk. 

The quick wins are increasing omega-3 fats from seafood and supplements, and lowering high homocysteine with B vitamins. The higher a person’s omega-3 level the better their cognition and the more brain density they have, according to research from Loma Linda University in California. (3) “Half of those over 65 have raised blood homocysteine which is easily lowered with a 10p a day B vitamin supplement.” says Holford “The health economist at Oxford University costed the saving just from this one prevention step as £50 million a year. (4) B vitamins with omega-3 have already been shown to reduce the annual rate of brain shrinkage by 73% in those at risk.” (5) The other big driver, he says, is sugar and ultra-processed foods. “Diabetes doubles dementia risk and accelerates brain shrinkage (6) but we can pick up those with the beginnings of blood sugar problems in mid-life with high but ‘normal’ levels of blood sugar which has been shown to increase Alzheimer’s risk by 14.5%. (7)” he says.

We also offer a ‘home-test kit that those at risk can use to measure homocysteine, omega-3, vitamin D and sugar balance (HbA1c – the test used by GPs to diagnose diabetes) then tells the individual what actions to take to protect their brain and improve their cognition. Research shows that having a low vitamin D level increases triples risk for Alzheimer’s (8) and those who supplement vitamin D cut Alzheimer’s risk by a third. (9)

“None of the major charities are taking prevention and the role of nutrition in brain health seriously.” says Holford, author of a new book Upgrade Your Brain which explains how to dementia-proof your diet and lifestyle. “Kate Lee of the Alzheimer’s Society told me they spend nothing on prevention. Alzheimer’s Research UK told us they spend 4.3% of all research money on non-drug prevention. When 80 percent is preventable surely at least half of research funds should be spent on non-drug prevention? We do not need to wait for more research. Dementia is diagnosed using a cognitive function test done in memory clinics. But by the time a GP refers a patient, it is often too late. We offer exactly this cognitive function test for free, online at foodforthebrain.org. There is no need to wait for a mythical blood test to ‘diagnose early’. 

This is like having a blood test to diagnose how unfit you are.” says Holford. “Even if this existed, the critical question for those at risk is how to reduce it. All that is needed is to take prevention seriously. It is not difficult. The government have pledged £166 million for dementia a year but no-one can tell us if any of this is actually to be spent on prevention research or putting prevention into action.”


We are supporting World Alzheimer’s Prevention Day see alzheimersprevention.info – on Wednesday (May 15th), with the support of thirty of the world’s leading dementia prevention experts.

Where to start in reducing your risk:
References

1 Zhang, Y., Chen, SD., Deng, YT. et al. Identifying modifiable factors and their joint effect on dementia risk in the UK Biobank. Nat Hum Behav 7, 1185–1195 (2023).
2 Beydoun MA, Beydoun HA, Gamaldo AA, Teel A, Zonderman AB, Wang Y. Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 2014 Jun 24;14:643. doi: 10.1186/1471-2458-14-643. PMID: 24962204; PMCID: PMC4099157.
3 Loong, S.; Barnes, S.; Gatto, N.M.; Chowdhury, S.; Lee, G.J. Omega-3 Fatty Acids, Cognition, and Brain Volume in Older Adults. Brain Sci.2023,13,1278. https://doi.org/ 10.3390/brainsci13091278.
4 https://doi.org/10.1016/j.trci.2016.07.0
5 Jernerén F, Elshorbagy AK, Oulhaj A, Smith SM, Refsum H, Smith AD (2015). Brain atrophy in cognitively impaired elderly: the importance of long-chain ω-3 fatty acids and B vitamin status in a randomized controlled trial. Am J Clin Nutr. 2015 Jul;102(1):215-21
6 Arvanitakis Z, Wilson RS, Bienias JL, Evans DA, Bennett DA. Diabetes mellitus and risk of Alzheimer disease and decline in cognitive function. Arch Neurol. 2004 May;61(5):661-6. doi: 10.1001/archneur.61.5.661. PMID: 15148141; see alsoYaffe K, Blackwell T, Kanaya AM, Davidowitz N, Barrett-Connor E, Krueger K. Diabetes, impaired fasting glucose, and development of cognitive impairment in older women. Neurology [Internet]. 2004 Aug 24 [cited 2022 Mar 16];63(4):658–63. Available from: https://n.neurology.org/content/63/4/658; see also Tiehuis AM, van der Graaf Y, Visseren FL, Vincken KL, Biessels GJ, Appelman APA, et al. Diabetes Increases Atrophy and Vascular Lesions on Brain MRI in Patients With Symptomatic Arterial Disease. Stroke. 2008 May;39(5):1600–3; see also Samaras K, Lutgers HL, Kochan NA, Crawford JD, Campbell LV, Wen W, et al. The impact of glucose disorders on cognition and brain volumes in the elderly: the Sydney Memory and Ageing Study. AGE [Internet]. 2014 Jan 9 [cited 2022 Aug 5];36(2):977–93. Available from: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4039246/
7 Zhang X, Tong T, Chang A, Ang TFA, Tao Q, Auerbach S, Devine S, Qiu WQ, Mez J, Massaro J, Lunetta KL, Au R, Farrer LA. Midlife lipid and glucose levels are associated with Alzheimer’s disease. Alzheimers Dement. 2023 Jan;19(1):181-193. doi: 10.1002/alz.12641. Epub 2022 Mar 23. PMID: 35319157; PMCID: PMC10078665.
8 Vitamin D deficiency increases the risk of Alzheimer’s.112 In a study in France involving 912 elderly patients followed for 12 years, a total of 177 dementia cases occurred. Those with low vitamin D levels had a nearly three-fold increased risk of Alzheimer’s.113
9 Ghahremani M, Smith EE, Chen HY, Creese B, Goodarzi Z, Ismail Z. Vitamin D supplementation and incident dementia: Effects of sex, APOE, and baseline cognitive status. Alzheimers Dement (Amst). 2023 Mar 1;15(1):e12404. doi: 10.1002/dad2.12404. PMID: 36874594; PMCID: PMC9976297.

Further info

Alzheimer’s: Why Prevention is Better than Cure

Everybody wants a cure for Alzheimer’s. 

The medical industry has spent around $100 billion searching for one and so far, come up relatively empty-handed with over thirty failed drug trials. The focus has been on drugs that lower two of the chemical compounds associated with Alzheimer’s and dementia in general – amyloid and p-tau, a pair of messed up proteins that can lead to plaques in the brain and tangled nerves. There is a third compound – an amino acid called homocysteine – that becomes toxic if you have too much, that the drug industry and the Alzheimer charities don’t talk about, for reasons that will become clear.

The actual clinical measures that are used to diagnose Alzheimer’s are a decline in cognitive function and shrinkage of the central area of the brain called the medial temporal lobe. Both changes in cognitive function and brain shrinkage can be picked up thirty years before a diagnosis of Alzheimer’s is made.  

So now a £10 million study is underway to see if a blood test for p-tau, or amyloid, will ‘predict’ if you are more likely to develop the disease and there are plans for a major programme to identify those at risk so they can be treated as early as possible.  This sounds sensible but there are serious drawbacks. To begin with not everyone with raised p-tau or amyloid go on to develop Alzheimer’s. 

This means, as a recent article in the New York Times entitled, ‘Apparently healthy but diagnosed with Alzheimer’s,’ pointed out, people without a diagnosis or no brain scan showing shrinkage, could well be offered new drug treatments that are so far, only marginally better than placebos but can have awful adverse effects. 

These include brain bleeding or swelling which has occurred in more than one in four in the last two drug trials and resulted in seven deaths. Medical agencies in the US, EU and UK are reluctant to licence their use but are under a lot of pressure to do so. 

So thousands of desperate people with early stage Alzheimer’s or cognitive decline, hoping for a cure, are queuing up to join these drug trials because they perceive these drugs, that so far come with little or no benefit plus highly unpalatable side effects, are a better alternative than doing nothing.

There are alternatives – you just haven’t been told about them!

But are there really no alternatives? Well, none that patients are routinely told about. They involve changes in diet and lifestyle that are very likely to improve your overall health, including that of your brain, and very unlikely to cause damaging side effects. 

Almost all money for research, pledged by governments and raised by Alzheimer’s charities, is going in the direction of drug treatments. Alzheimer’s Research UK’s (ARUK) website says “we exist for a cure”. Most of the money is going toward amyloid and p-tau related research, neither of which have been established as causal. In other words, high levels may just be a consequence of the disease process.

The same is not true for raised blood levels of homocysteine. If levels rise in the brain, it shrinks faster and cognitive abilities decline. If it goes down, they improve, and brain shrinkage slows. This means that it is causing the damage and so would logically be a target for treatment. The only way to do it, however, is with high dose B vitamins (B6, B12 and folate). Several gold standard, placebo-controlled trials have found this to be very safe and effective. But this approach is not patentable and so yields nothing like a drug profit.

This is a much better biomarker than p-tau

But the benefits of treating homocysteine don’t stop there. It is a much better biomarker of risk for Alzheimer’s than plaque and p-tau both because it is more easily measured and more safely lowered. And when it is lowered, unlike those two, it actually improves cognitive function and slows brain shrinkage by as much as two thirds. It also helps to stop p-tau formation.

Routinely checking homocysteine levels could prevent thousands of cases. Just doing this “could save costs to the UK economy of approximately £60 million per year,” says Dr Apostolos Tsiachristas, Associate Professor in Health Economics at the University of Oxford. His research also estimated it would promote healthy longevity, adding 14 years to life expectancy. 

About half of people over 65 have a homocysteine level above 11 mcmol/l, which is where it starts to become damaging. In one study a third of those treated ended the study with no clinical dementia rating, meaning they could no longer be diagnosed with cognitive impairment. Those with sufficient omega-3 DHA, which is the most important structural fat in the brain, had 73% less brain shrinkage compared to placebo when given the B vitamin treatment. In contrast, in the last anti-amyloid treatment trial, brain shrinkage accelerated by about a fifth in those getting the drug, compared to placebo and not one person achieved a clinical dementia rating of zero.

It should be clear by now, after decades of scientific research that amyloid plaque is not a cause of Alzheimer’s, but a consequence. The same is likely to be true for p-tau tangles.

As an analogy, consider your teeth. Is plaque the cause of tooth decay?  Sure, flossing your teeth and getting the plaque scraped off by the dental hygienist helps, but what causes the plaque? The answer is a bad diet – in this case, one high in sugar and low in fibre. Despite fifty years of research, there is no ‘cure’ for tooth decay, but it can be prevented. The same concept applies to Alzheimer’s, which is as preventable as tooth decay with the right diet and nutrition and lifestyle – which also happens to include less sugar and more fibre.

Alzheimer’s Prevention

How preventable is Alzheimer’s? It accounts for two thirds of dementia cases. The most conservative figure is 40% . More optimistic estimates say around 80%. Since only one in a hundred cases is caused by genes Alzheimer’s may be entirely preventable in those 99% who do not have the rare causative genes and act early enough to optimise all diet and lifestyle factors. It is not an inevitable consequence of the ageing process as evidenced by the fact that the majority of people don’t get it.

Why the difference in figures? It’s all to do with what is or isn’t included in prevention studies. The most widely used review for dementia prevention in the UK is the 2020 report of the Lancet Commission, authored by Professor Gill Livingston. Both this and the first edition in 2017 failed to even mention homocysteine, despite being repeatedly sent all the evidence of the undeniable beneficial effects of homocysteine-lowering B vitamins by the Oxford Project to Investigate Memory and Ageing (OPTIMA) at the University, headed by former Deputy Head of Medical Science, Professor David Smith.

This is a major and damaging error and has led to the widespread belief that B vitamin supplements are not part of the usual list of preventive actions. But it should be corrected, especially considering that a US National Institutes of Health study attributes 22% of the risk of Alzheimer’s to raised homocysteine. Also, the best study of all, looking at 396 studies in total, published in 2020, concluded: ‘Homocysteine-lowering treatment seems the most promising intervention for Alzheimer’s disease prevention.’

Other prevention studies you may have read are possibly based on data from the UK Biobank. This major research data bank also ignores homocysteine, not for any malevolent reason but simply because it wasn’t measured when it was enrolling people. So, one of the single biggest risk factors and arguably the simplest to change, is repeatedly ignored.

Given that a conservative half of Alzheimer’s cases could be prevented, shouldn’t half the available research money be spent on prevention? 

This certainly doesn’t happen at the moment. Of the three leading charities, two spend nothing on prevention. ARUK claims to spend 5% but none of this goes towards B vitamins or other brain-friendly nutrients such as omega-3 or vitamin D. They, too, ignore homocysteine, and the beneficial effects of lowering it with B vitamins, as first shown in a 2010 Oxford University study they actually helped fund!

1+1=3

Prevention studies are almost always going to underestimate (never overestimate) the power of prevention due to excluding risk factors, but also because they largely ignore the ‘1+1=3’ compounding impact of interactive risk factors. B vitamins, for example, don’t work without sufficient omega-3 and omega-3 fish oils don’t work in people with raised homocysteine, because of a lack of B vitamins. This has been shown in four trials – in the UK, Holland, Sweden and China. The combination of B vitamins given to people sufficient in omega-3 DHA improved the reduction in brain shrinkage from 53% to 73%. 

Pollution exposure is a risk factor but, in those with lower homocysteine, this effect is much reduced. Poor sleep is a risk factor, but less so in those who exercise. 

For the past five years leading UK researchers, led by neurologist Professor Peter Garrard, who is the Director of the dementia research group in the St George’s, University of London Neuroscience Research Section, have tried to get funding to test the most promising combination – B vitamins and omega-3 – to no avail. Such a trial is badly needed and would cost a fraction of that being spent on amyloid or p-tau.

So. What if a person does everything right – enough B vitamins to keep homocysteine low, sufficient omega-3, low sugar, high fibre diet, enough vitamin D (Alzheimer’s is four times less likely in those with sufficient vitamin D), and an active physical, intellectual and social lifestyle, plus good sleep and not too much stress? 

The only ongoing study and database that assesses all these risk factors as well as including blood tests of four critical biomarkers, homocysteine, omega-3 index, vitamin D and HbA1c, which measures glucose control, is our COGNITION Biobank. We describe it as ‘citizen science’ because anyone can get involved doing a free online Cognitive Function Test, filling in a questionnaire about their diet, lifestyle and medical history, and sending in a blood sample from our home test kit available for purchase. 

So far, over 400,000 people have done our test. But, unlike the £10 million trial, funded by the People’s Lottery, the Gates Foundation, ARUK and the Alzheimer’s Society, it gets no funding. It is literally funded by our citizen scientists who chip in £50 a year and pay for their own tests. Their message is simple: prevention is better than cure – don’t jump.

Action:

A world-class group of Alzheimer’s prevention experts are launching Alzheimer’s Prevention Day on May 15th. See alzheimersprevention.info.

(The 3-minute Alzheimer’s Prevention Check goes live on May 1st).

References & Info

These are key papers regarding stated facts in this article.

Donanemab review in the British medical Journal: BMJ 2023;382:p1852 

Health economics of B vitamins: Tsiachristas A, Smith AD. B-vitamins are potentially a cost-effective population health strategy to tackle dementia: Too good to be true? Alzheimers Dement (N Y). 2016 Aug 11;2(3):156-161. doi: 10.1016/j.trci.2016.07.002. PMID: 29067302; PMCID: PMC5651357.

Omega-3 and B vitamin interactions and studies: Smith AD, Jernerén F, Refsum H. ω-3 fatty acids and their interactions. Am J Clin Nutr. 2021 Apr 6;113(4):775-778. doi: 10.1093/ajcn/nqab013. PMID: 33711096.

Less brain shrinkage and cognitive decline with B vitamins and sufficient omega-3: Jernerén F, Elshorbagy AK, Oulhaj A, Smith SM, Refsum H, Smith AD. Brain atrophy in cognitively impaired elderly: the importance of long-chain ω-3 fatty acids and B vitamin status in a randomized controlled trial. Am J Clin Nutr. 2015 Jul;102(1):215-21. doi: 10.3945/ajcn.114.103283. Epub 2015 Apr 15. PMID: 25877495; see also  Oulhaj A, Jernerén F, Refsum H, Smith AD, de Jager CA. Omega-3 Fatty Acid Status Enhances the Prevention of Cognitive Decline by B Vitamins in Mild Cognitive Impairment. J Alzheimers Dis. 2016;50(2):547-57. doi: 10.3233/JAD-150777. PMID: 26757190; PMCID: PMC4927899.

NIH Alzheimer’s prevention review: Beydoun MA, Beydoun HA, Gamaldo AA, Teel A, Zonderman AB, Wang Y. Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 2014 Jun 24;14:643. doi: 10.1186/1471-2458-14-643. PMID: 24962204; PMCID: PMC4099157.

Meta-analysis of 396 studies favouring homocysteine-lowering B vitamin treatment: Prof Yu study Yu JT, Xu W, Tan CC, Andrieu S, Suckling J, Evangelou E, Pan A, Zhang C, Jia J, Feng L, Kua EH, Wang YJ, Wang HF, Tan MS, Li JQ, Hou XH, Wan Y, Tan L, Mok V, Tan L, Dong Q, Touchon J, Gauthier S, Aisen PS, Vellas B. Evidence-based prevention of Alzheimer’s disease: systematic review and meta-analysis of 243 observational prospective studies and 153 randomised controlled trials. J Neurol Neurosurg Psychiatry. 2020 Nov;91(11):1201-1209. doi: 10.1136/jnnp-2019-321913. Epub 2020 Jul 20. PMID: 32690803; PMCID: PMC7569385.

Further info

Interview: The What & How of Alzheimer’s Prevention – Two Researcher’s Explain

If you ask the man on the street what’s driving Alzheimer’s, they’ll probably say it’s in the genes or that it is just what happens when you age. 

Now, neither of these statements are strictly true. 

Alzheimer’s is a largely preventable disease. 

The big question though is WHAT exactly needs to be done and HOW do we do this?

This is why Patrick recently interviewed two experts in these areas who are also members of our Scientific Advisory Board:

Dr. Tommy Wood is an Assistant Professor of Pediatrics and Neuroscience at the University of Washington in Seattle. His research program focuses on factors associated with brain health and function across the lifespan. He received his undergraduate degree in Natural Sciences from Cambridge in 2007, a Medical Degree from Oxford in 2011, and a PhD from the University of Oslo in 2017. Alongside his academic training, Tommy has provided Performance Consulting for Olympians and world champions in a dozen different sports. He is a founding trustee of the British Society of Lifestyle Medicine and associate editor for the journal Lifestyle Medicine.

Dr Kristina Curtis is an Expert in Digital Behaviour Change Interventions (DBCIs). She has a multidisciplinary background spanning across industry, research, teaching, training and consultancy. Her primary research interests are in the development and evaluation of mHealth (mobile health) interventions, in particular how the convergence of behavioural science and UX design promotes effective engagement.

(Want to learn more about the Citizen Science Research Team? Click here to find out more)

Interview:

Diagnosis & the difference between Alzheimer’s, dementia and mixed dementia.

Patrick Holford (PH)

My guests today are tackling the two fundamental questions. 

  1. Firstly, what are the positive and negative behaviours, diet lifestyle and environment that both either drive dementia or prevent it?
  2. And then the big question is, how do you encourage people to change those behaviours? 

So we have a system Professor, Tommy Wood from the University of Washington about the ‘what’.  Then to Dr. Kristina Curtis, a behavioural scientist and honorary lecturer at the University College London who heads the applied behaviour change team about how to affect behaviour change. 

Now, your background in relation to the brain is broad I see, from your time at Cambridge and Oxford University then Norway and now as assistant professor of Paediatrics and Neuroscience at the University of Washington. I believe you’ve also brain-trained Formula One drivers. Tell us about your background and how you became involved in this challenge to prevent Alzheimer’s.

Tommy Wood (TW)

I essentially fell into neuroscience initially, around 20 years ago when I was an undergraduate at Cambridge. I spent a summer in the neonates neuroscience lab looking at brain injury in babies. This is still partly what I do 20 years later.  

In between, I then went to medical school where I trained as a doctor and I also developed a lot of interest in other neurodegenerative conditions. For instance, I spent a lot of time looking at a systems approach to multiple sclerosis because my step brother was diagnosed with multiple sclerosis when he was a similar age to me in his mid 20s.  

Then, as I worked through my PhD in my early formal academic career as a professor, I worked increasingly with athletes as a performance consultant. So anything related to their cognitive and physical performance which could be sleep, diet and other stresses that they are frequently exposed to.  So, as this story of my career comes together, I work with brain injury at the beginning of life, then as I work with athletes, I do more around concussions and traumatic brain injury. And then you think, well, there were all these factors that start early in life, probably even before you’re born, that create this trajectory of how your brain functions. And that continues as you get older. So then, that makes me think about, how do we intervene at any life stage to ensure that we have cognitive function that lasts as long as possible, ideally preventing significant cognitive decline and dementia in old age. Then you start to see that these same risk factors are important at every stage so that you can start to build this idea of what the brain needs, and then you can figure out how you might want to intervene. 

PH 

I was just interviewing Professor Michael Crawford, age 93, and using some sort of quantum physics, he’s worked out how the photons that hit our eye turn into the image that we actually see. And I remember at the same age of 93, filming Linus Pauling on his theory of lipoprotein A. So I’ve witnessed people well into their 90s as sharp as a razor.

But before that, a little bit of background, what is the difference between Alzheimer’s and dementia overall, and we also hear about vascular dementia?

TW  

Dementia is essentially a catch-all diagnosis for when an individual has reached a point of cognitive decline where they are no longer able to perform regular daily tasks or usually look after themselves. So it’s a clinical diagnosis based on overall cognitive functioning. 

Then you might ask, Well, what’s causing this dementia in an individual and then we we have the sub categories, so Alzheimer’s dementia, which, if you asked Alzheimer himself, apparently he was unsure whether they should all be classified as the same thing, but that’s a sort of semantic argument.

But what we would call Alzheimer’s clinically makes up maybe 60 to 80% of dementia. Vascular dementia, which is more directly focused on blood supply to the brain, makes up something like 5 to 10%. Then there are other dementias that have very special effects on very specific parts of the brain but overall, their effect on broad cognitive function eventually ends up in a similar place. 

So with Alzheimer’s, dementia is often thought to be this continuous, gradual decline in function. Whereas with vascular dementia, what is often thought to happen is you have these very small strokes that happen throughout the brain. And each time that happens, you lose a portion of function, so you have more of this step change over time. However, in reality, there tends to be lots of overlap between say vascular and Alzheimer’s dementia, because blood supply to the brain is also important, for Alzheimer’s and sometimes it can be difficult to differentiate between the two. 

PH

And how is Alzheimer’s diagnosed as you know, in that form of dementia?

Usually, it’s going to involve some cognitive function tests. So there are lots of standardised tests like the MACA, MMSE appeal  – you may have heard of these. But there’s a whole range of tests that you’re usually going to do in person with a neurologist or an old age psychiatrist and part of it is going to be a diagnosis of exclusion. So you want to make sure that somebody doesn’t have something else going on, like a very significant vitamin deficiency or other things that can be significant like depression as they can look like significant cognitive decline or dementia, but they aren’t necessarily the same thing. So part of it is going to be excluding these other causes. Then you will probably do some brain scans and look at how the brain looks either on a CT scan or an MRI and then that, in conjunction with cognitive function, and some part of the medical history is going to tell you this is likely Alzheimer’s dementia. Often, we hear of someone being diagnosed with mixed dementia. 

PH

Is that mainly part Alzheimers, part vascular? 

TW

Yes, that’s the most common combination, but if you think about Lewy body dementia, or Frontotemporal dementia, these can also occur in different combinations in different people. But usually, because of the overlap in terms of the risk factors, Alzheimer’s with some vascular component is relatively common. 

Preventing Alzheimer’s

PH

Now, if a person could change all their circumstances, and we’re sort of talking from early life as well, – their diet, their lifestyle, the environment that they’re born into, and their education, to what extent could we say that Alzheimer’s is a preventable disease?

TW  

It depends on how you want to try and tackle the question. But if you can change everything about an individual’s circumstances other than their genetics, then the vast majority is preventable. Depending on who you ask, some will say that it’s maybe 40 to 50%. Others will say that it’s up to maybe 70 to 80%. In some populations around the world, usually hunter-gatherer or indigenous populations, dementia is almost entirely unheard of. So it’s definitely possible that there are some combinations of environment and genetics where dementia just doesn’t occur and in that scenario, it is entirely preventable. 

PH

Now, do these same prevention steps, which obviously we’re going to go into, also prevent vascular dementia? And if so, if we put Alzheimer’s and vascular and a chunk of mixed dementia together, are we talking about 80% of dementia for example, being potentially 80% preventable?

TW  

Yes. So, as I mentioned briefly earlier, there’s a lot of overlap between the risk factors for vascular dementia. And those are also related to cardiovascular disease risk factors. So things that affect your body’s ability to move blood to the places that you want it to move to, the health of your blood vessels. There is a lot of overlap between those risk factors or things that affect negatively and those are risk factors for Alzheimer’s disease.

In fact, cardiovascular disease and poor vascular health are risk factors for Alzheimer’s dementia more directly. So if we think about the upper end of the subcategories of dementia that, 80% is Alzheimer’s disease, 10% is vascular dementia, which based on estimates could be up to 90% then yes, up to 90% of dementia is probably at least 70 ish to 80 ish percent preventable.

Test Your Cognitive Function Now green banner.
How important a role do genes play?

PH

It’s often said that early onset Alzheimer’s, which is defined as before the age of 65, is that small genetic part, but a study that came out earlier this year questioned that. It was on the basis of data from the UK Biobank and it actually said that many of the same factors that are driving dementia or Alzheimer’s later in life are also present in those who develop a diagnosis before 65. So that sort of de-emphasises the genes to some extent. 

Is this true, that early onset is much the same phenomena that we’re looking at.

TW  

Yes and no. 

So traditionally, early onset Alzheimer’s, is thought to be almost entirely genetic, and driven by single significant, high penetrance genetic mutations that result in early cognitive decline. In Alzheimer’s dementia, which is thought to be more similar to what Alzheimer himself was describing when he first described the disease, it was thought to be maybe five to 10% of dementia. Now, as Alzheimer’s diseases become more prevalent,  it’s maybe around 1% of cases. However, I certainly know clinicians who have patients who have one of these mutations in a presenilin gene, or the amyloid precursor protein gene and by attending to lifestyle factors, they managed to maintain good cognitive function late into life. So even if you have some of these mutations, which are thought to almost definitely lead to Alzheimer’s disease, there does seem to be an interaction with lifestyle and other health related factors. 

Then, at the same time, we’re seeing earlier diagnosis of non-monogenic Alzheimer’s disease, which is what this paper you described, was talking about. And that’s probably because the health of the population is declining, such that we’re seeing pre-diabetes earlier, we’re seeing people that are less physically active, maybe they’re less cognitively stimulated.  All these other risk factors are adding up and they’re affecting our brains earlier in life. So now there’s more of a mix, in early onset Alzheimer’s disease, as those risk factors become prevalent earlier in life. 

Diagnosed with Alzihemrs at age 19?  A growing tsunami of cognitive decline 

PH

I saw a report from China, of a man aged 19 diagnosed with Alzheimer’s, it said it was non-genetic, so presumably, they tested and there wasn’t the Apoe gene or the pre Senlin gene, I can’t confirm that. But can it really happen that fast, this cognitive decline that we are seeing that is so prevalent?

TW  

If you think about cognitive function as a trajectory, over time, there are three or four different components to that. 

So first of all, as you get older, cognitive function generally peaks on average, towards the end of your formal period of education. So if that education extends into university or maybe a graduate degree, then that’s going to peak sometime in your 20s or early 30s. But if you don’t even complete secondary school or high school, then it’s going to peak much earlier, and it’s going to have a much lower peak. After the peak, then you have a period of decline, and the speed of that decline depends on a number of factors, the majority of them related to ongoing stimulus to the brain as well as a whole host of health-related and nutritional factors, as you know very well. So there’s certainly a possibility where if you had a low peak of cognitive function, and that may even be based on something like maternal nutrition and epigenetics related to the health of your parents, so you had a low peak, and you have poor overall health, you’d have a more rapid decline. It’s certainly possible that this could happen very early in life, though, thankfully, at least right now, that’s very rare.

PH  

Yeah, we’ve seen the youngest with type two adult onset diabetes age three, so quite extraordinary. 

So is Alzheimer’s, just the tip of the iceberg of a growing tsunami of cognitive decline that is likely to start happening earlier?

TW  

Yes and no.

I say no, because having had lots of conversations, including with one of your close colleagues and mentors, David Smith. When you look at the specific prevalence of Alzheimer’s disease, it has not increased over time. And in fact, in some populations, it’s decreased.  It’s probably decreased a little bit more in men, because we focus very heavily on cardiovascular disease risk factors, which are more important in men in terms of causes of death.

And that has come with some improvement in terms of age-specific incidence of Alzheimer’s disease, when the reason why Alzheimer’s disease is becoming more prevalent, and it’s going to double or triple in the next few decades, is because we’re living longer. So there’s a combination of we’re living longer, and in general, our health is declining. 

So you could say, there’s this oncoming wave of Alzheimer’s disease, and that is expected. But we know that if we target specific risk factors, that doesn’t have to be the case. So I don’t think it’s all bad news.

A green Citizen Scientist badge, with the quote "optimum nutrition is the future of medicine".
(Donations solely fund our research please donate to fund our Citizen Science)
Our Citizen Science Research Team

PH  

Now, you’re the principal investigator at Food for the Brain heading, the research and the science there. So what does that involve? 

What’s your goal as a principal investigator?

TW  

One of the most important tools that we have when we’re looking at diseases or specific functions or health of the population are our population datasets, and there are lots of these. 

Governments around the world organise them, there’s Haynes in the US, there’s the UK Biobank in the UK that people have heard of, and you collect lots of data from lots of people, and at that kind of scale, you can start to maybe pick up relationships that you couldn’t otherwise. 

When we think about the risk factors for cognitive decline, and dementia, specifically, none of the datasets that exist so far are really designed to focus on that. So one of the most important ideas is to collect data, specifically related to risk factors for Alzheimer’s, dementia, and hopefully those that are modifiable. So it’s kind of a citizen science idea, right?  We’re going to people who are interested in this or maybe interested in this for their loved ones.  They are providing their data and part of it is to help understand their own risk, but then allowing us to look at a wide variety of risk factors. 

There are over a hundred questions in a questionnaire that look at different risk factors and we have the cognitive function test and blood tests. So then, when you have very large datasets like this, we can start to look for complex interactions between risk factors, and we can figure out which risk factors are most important. These are things that still need to be done as it pertains to most Alzheimer’s disease. I think, hopefully, Food for the Brain is going to be in a good position to help people understand that.

Test Your Cognitive Function Now green banner.
Figuring out the perfect food and lifestyle combo – what matters more!

PH

So what’s your ultimate goal from this data set – to find the sort of perfect diet lifestyle combo?

TW 

I think that there are two main things. In reality, I think that we know what is going to be best for most people.  If we look across all the evidence, we probably know that already we can have a good guess of what you should aim for.

When you say, here are the 50 things you need to fix to improve your brain health. There’s just an overwhelming amount of information – you don’t know where to start, what should I do? 

First, what’s most important to me, what’s most impactful? So figuring out which factors an individual should focus on first, which gives the biggest bang for their buck is what’s going to be a big, big part of this. Then the million dollar question is how do you actually change a person’s often highly entrenched behaviour, especially if we want to reach hundreds of 1000s across a digital platform?

PH 

So Dr. Kristina Curtis, welcome. 

You’re a behaviour change expert and an associate of UCLA Centre of Behaviour Change and founder of Applied Behaviour Change, which focuses on digital health programmes to help prevent and manage chronic conditions. 

Can you explain a bit about your background and the reason you are interested and involved in this Alzheimer’s prevention project? 

Khristina Curtis KC

After my psychology degree, I had a few years out working in industry because I hadn’t found the area of psychology that I wanted to specialise in. And so this led me to return to studies to specialise in health psychology, which is all about health behaviours. And then immediately afterwards, I then started a PhD, which really culminated my experience back then, which was web to technology, with my academic knowledge of health psychology at the Institute of Digital Healthcare at Warwick University.  

My PhD was really focused on how we would embed behaviour change models into mobile health apps and digital health interventions. And really, I feel passionate about preventing chronic conditions and particularly Alzheimer’s disease, as there are a lot of misconceptions about it. And we’ve talked a lot about them today. And in terms of many people think it’s a symptom of ageing, and largely down to our genes. Whereas, as we’ve heard, we can do a lot to reduce our risk by adopting healthier habits. 

How do we implement these ‘risk-reducing’ behaviours and habits?

PH

And what are you doing in the cognition project at Food for the Brain? What’s your game plan? 

KC

Let’s talk about the kinds of preventative behaviours. 

For example, increasing physical activity, eating a healthier diet, social interaction, brain training, might all help to reduce our risk of developing things like Alzheimer’s and dementia. One of the issues here is that actually sustaining these long term changes and making them long term habits is extremely challenging. 

There is quite a good evidence base on which behaviour change techniques work but we’re still really in the early stages of understanding how to implement these techniques in a way that engages different groups of people. There is strong evidence which suggests that we should have a tailored approach.

We are a small but mighty team and charity running on donation alone – please donate to our continued research here.

A green Citizen Scientist badge, with the quote "optimum nutrition is the future of medicine".

Also, you can learn more about our Citizen Science Research Team here.

Further info
Early Dementia Prevented by Our 8 Domains, Shows UK BioBank Study

Early-onset dementia, often talked about as ‘genetic’, has been linked to exactly those factors that our Dementia Risk Index questionnaire, part of the Cognitive Function test, assesses. 

In other words, what you do and how you live protects you from losing cognitive function at any age.

This study from the UK Bio Bank’s data defined young-onset dementia (YOD) as a diagnosis before the age of 65, but many people experience degrees of cognitive decline at younger and younger ages. This report (1) from China even confirms a 19-year-old man, with no causative Alzheimer’s genes being diagnosed with Alzheimer’s!

Thankfully there is lots you can do to reduce your risk and prevent the loss of your mind and memories.

This UK BioBank study (2) identified 485 people out of 356,000 who developed dementia before the age of 65. The estimate is that 70,000 people in the UK suffer from young-onset dementia. It identified 15 risk factors, many of which we already address within our 8 domains

Particularly predictive were a person’s vitamin D level, diabetes and depression. (The 15 identified risk factors were lower formal education, lower socioeconomic status, carrying 2 apolipoprotein ε4 allele, no alcohol use, alcohol use disorder, social isolation, vitamin D deficiency, high C-reactive protein levels, lower handgrip strength, hearing impairment, orthostatic hypotension, stroke, diabetes, heart disease, and depression.)

Vitamin D is vital to supplement in the winter. Those who do have a 40% lower incidence of dementia according to a recent study. A study in France those with low vitamin D levels, below 50 nmol/L, had a nearly three-fold increased risk of Alzheimer’s. Over sixty per cent of people in the UK have lower levels than this. This is why we are now offering vitamin D testing to everyone who has taken the Cognitive Function Test.

Diabetes, and pre-diabetes, is best identified from a blood test for HbA1c which determines glucose control. Levels above 6.5% indicate diabetes while adolescents with levels above 5.4% have been shown to have a degree of cognitive impairment. In young adults having the early signs of poor glucose control is a future predictor of dementia.

The incidence of depression goes up substantially in those with low vitamin D, poor glucose control as well as a lack of omega-3 (now included in the tests we offer.) It may also reflect lack of stimulation for example from loneliness, unemployment, lack of mental stimulation through education and lack of opportunity.

Diet wasn’t sufficiently investigated, nor homocysteine, because the UK Biobank questionnaire doesn’t ask sufficient questions to go close up, nor is homocysteine part of the blood test data. That is why Food for the Brain’s growing data bank – the result of people like you taking the time to do the test – is going to prove so invaluable. (This is one of the reasons we have launched our highly accurate, affordable, at-home Homocysteine test kits which will be back in stock later this week.

Prof Llewellyn, one of the study authors, said the study “reveals that we may be able to take action to reduce risk of this debilitating condition”.

Even with this data gap, this study shows that a lot of the risk factors for early-onset dementia are preventable. At the end of January, we are launching the DRIfT (Dementia Risk Index Functional Test) home test, measuring both vitamin D, omega-3, HBA1c and homocysteine with a home test kit.

When you address these factors, which is what our Cognitive Function Test and follow-up COGNITION program is designed to do, you can mitigate your risk of dementia.

While we have had over 400,000 do the test and see many people’s dementia risk index decrease and Cognitive Function Score increase, this research confirms our work and mission.

As our founder and CEO Patrick Holford says:

Take the Cognitive Function Test today, learn your current brain health status and take our easy at-home blood tests (like vitamin D) so that you know exactly how to reduce your risk and prevent dementia at any age.

Test Your Cognitive Function Now green banner.
References

1 – https://pubmed.ncbi.nlm.nih.gov/36565128/

2 – https://pubmed.ncbi.nlm.nih.gov/38147328/

Further info
Omega-3 cuts dementia risk by a third

The largest study of its kind, involving over a quarter of a million people (267,000) from the UK Bio Bank, has reported 30 per cent less risk of dementia in those with a higher omega-3 status in their blood (1). 

One of the study authors, Professor Bill Harris from Stanford University’s Department of Medicine in South Dakota, says “There is now overwhelming evidence from no less than four studies this year that increasing your intake and blood levels of omega-3 is strongly associated with reducing future dementia risk. Ideally a person wants to get their blood omega-3 index above 8%”.

This UK study confirmed the results of a US study (2) earlier this year that found a 49 per cent reduced risk for dementia in those with the highest omega-3 DHA level (top fifth) in their red blood cells versus the lowest (bottom fifth). Oily fish and fish oil supplements contain two kinds of omega-3 fat called DHA and EPA. DHA is the main fat found in brain cells of all animals.

What’s more a meta-analysis of 48 studies in the American Journal of Clinical Nutrition in 2023 (3) also concludes that ‘a moderate-to-high level of evidence suggested that dietary intake of omega-3 fatty acids could lower risk of all-cause dementia or cognitive decline by about 20 per cent, especially for DHA intake’. 

Each 100mg increment of DHA was associated with an 8–10 per cent lower risk of dementia. 

But it also predicts the actual size of your brain.

A recent study by psychologists at the Linda Loma University in California and published in the journal Brain Sciences (4), reported that the higher a person’s omega-3 index was in their blood, the more white matter there was in their brain meaning they had more brain volume, and the better they performed on cognitive tests that predict less risk for dementia.

This is why we have launched our omega-3 campaign and offer our home test kits to measure the omega-3 index from a pinprick of blood, the measure used in this research. Alongside the blood test, you are invited to complete a free online Cognitive Function Test and a Dementia Risk Index questionnaire that not only calculates your risk but tells you what to do to lower it. 

We hope to enrol hundreds of thousands of people interested in protecting their brains and willing to have a yearly pinprick blood test and assess their memory with a validated online test. 

This is ‘citizen science’ with the research results shared back to everyone involved. 

Less than one per cent of Alzheimer’s is caused by genes. This is a largely preventable disease and getting your omega-3 level up by eating oily fish and taking supplements is likely to cut risk by a third. We need to both research and educate people to take prevention action from their 30s.

Test Your Cognitive Function Now green banner.
References

1 Sala-Vila, A.; Tintle, N.; Westra, J.; Harris, W.S. Plasma Omega-3 Fatty Acids and Risk for Incident Dementia in the UK Biobank Study: A Closer Look. Nutrients 2023, 15,4896. https://doi.org/10.3390/ nu15234896

2 Sala-Vila, A.; Satizabal, C.L.; Tintle, N.; Melo van Lent, D.; Vasan, R.S.; Beiser, A.S.; Seshadri, S.; Harris, W.S. Red Blood Cell DHA Is Inversely Associated with Risk of Incident Alzheimer’s Disease and All-Cause Dementia: Framingham Offspring Study. Nutrients 2022, 14, 2408. https://doi.org/10.3390/ nu14122408

3 Wei BZ, Li L, Dong CW, Tan CC; Alzheimer’s Disease Neuroimaging Initiative; Xu W. The Relationship of Omega-3 Fatty Acids with Dementia and Cognitive Decline: Evidence from Prospective Cohort Studies of Supplementation, Dietary Intake, and Blood Markers. Am J Clin Nutr. 2023
4 Loong, S.; Barnes, S.; Gatto, N.M.; Chowdhury, S.; Lee, G.J. Omega-3 Fatty Acids, Cognition, and Brain Volume in Older Adults. Brain Sci.2023,13,1278. https://doi.org/ 10.3390/brainsci13091278

Further info
Medicinal Mushrooms Help Fight Cognitive Decline & Protect Your Brain

 By Sophie Barret – Hifas da Terra & Patrick Holford

Two medicinal mushrooms are particularly relevant when it comes to optimising your brain health, here we discuss Reishi (Ganoderma Lucidum) and Lion’s Mane (Hericium erinaceus); in terms of their potency and use in both Alzheimer’s and Dementia as well as the studies and clinical research into both these significant strains.

Alzheimer’s disease is the most common form of dementia and, according to the WHO, accounts for 60-70% of cases. It is a progressive neurological disorder that involves a steady decline in thinking, behaviour and social skills that affects a person’s ability to live independently. Although age is the main risk factor for dementia, the disease is not an inevitable consequence of ageing. This type of dementia does not exclusively affect older people. Early-onset dementia (onset of symptoms before the age of 65) accounts for up to 9% of cases. Regular physical and mental exercise, avoiding cigarette smoke and alcohol, controlling weight and blood pressure, as well as following a healthy diet and premium quality supplementation can reduce the risk of Alzheimer’s or even slow down the process.

The application of Mycotherapy for Alzheimer’s focuses on the use of pure, standardised, organic extracts of Lion’s Mane (Hericium erinaceus) and Reishi (Ganoderma lucidum), the supplementation of which has been associated in clinical studies with a reduction in the likelihood of mild cognitive impairment and in vivo with anti-dementia activity in cognitive deficits.

The neurodegenerative mushroom: lion’s mane

Lion’s Mane, (Hericium erinaceus) is a medicinal mushroom with diverse pharmacological activities in the prevention of many age-associated neurological dysfunctions, including Alzheimer’s disease and Parkinson’s disease. (5). Supplementation of H. erinaceus has been shown to improve cognitive function and memory in people with mild cognitive impairment (4) and slow cognitive decline and dementia. Its extract is highly recommended in the treatment of neurodegenerative diseases.

The action of Lion’s Mane is based both on its ability to regenerate damaged nerve axons and to enhance myelinization. This is thanks to the rich content of hericenones found in Lion’s mane extract that act as a Nerve Growth Factor (NGF) enhancing agent.

European Biotech, Hifas da Terra, conducted the Neurofood study in people using a unique Lion’s Mane strain. The results showed significant improvements in participants’ attention, memory, concentration, processing speed and visuospatial skills.

The neuroprotective mushroom: reishi

Reishi has demonstrated neuroprotective capacity due to its potent antioxidant properties. Thanks to the antioxidant capacity of G. lucidum’s active biomolecules, especially terpenes such as ganoderic acid, it can improve the reduction of age-related oxidation linked to impaired cognitive function (12,13,14), alleviating neuronal damage and inhibiting apoptosis in Alzheimer’s disease (15).

Several studies and reviews have demonstrated its preventive and therapeutic effect on neuronal damage and cognitive impairment (9).

The antioxidant effect of G. lucidum, thanks to the ability of its active ingredients to scavenge free radicals, may enhance the reduction of age-related oxidation linked to cognitive function decline. (10).

What about ‘magic mushrooms’ & psychedelics ?

One of the hottest areas of brain research is the effects of various hallucinogenic compounds, notably psilocybin – a hallucinogenic substance in certain types of mushrooms, but also LSD and the Amazonian plant potion Ayahuasca, a rich source of DMT, on mental health and brain function. These compounds are tryptamines and share a quality of activating a key receptor site in the brain for serotonin, called 5-HT2 receptors.  As a group, they are all shown to be potential promoters of neuroregeneration and neuroplasticity, helping make neuron connections and perhaps new neurons. They also stimulate brain-derived neurotrophic factor (BDNF), a key brain signaller that stimulates growth. 

With many studies (13) now showing the potential of psychedelics to help those with treatment-resistant depression, drug addiction and also anxiety in terminal patients, much attention is being focussed on what they actually do in the brain. On a psychological level, breakthroughs in debilitating depression and anxiety seem to occur through the experience of patients ‘exorcising the demons’ of early traumas through psychotherapy assisted trips. But there may be more going on at a biological level. Also, studies are underway testing less heroic doses – microdoses – of these agents. It is too early to say whether they could have a helpful role in those with early cognitive decline and brain shrinking but it is certainly plausible and an area of ongoing research. It’s a case of ‘watch this space’.

In summary, the application of Mycotherapy for any type of dementia seeks to provide a neuroprotective effect, improving quality of life. It focuses also on the use of pure, standardised organic extracts of Lion’s Mane (Hericium erinaceus) and Reishi (Ganoderma lucidum), the supplementation of which has been associated in clinical studies with a reduction in the probability of suffering mild cognitive impairment (MCI) and in vivo with anti-dementia activity in cognitive deficits.

Lion’s Mane, (Hericium erinaceus) is a medicinal mushroom with a variety of pharmacological activities in preventing many age-associated neurological dysfunctions, including Alzheimer’s and Parkinson’s (1). As mentioned, supplementation of H. erinaceus (Lion’s Mane) has been shown to improve cognitive function and memory in people with mild cognitive impairment (2) and is therefore highly recommended in the integrative treatment of neurodegenerative diseases.

The action of H. erinaceus is based both on its ability to regenerate myelin and to regenerate new synapses thanks to its content of hericenones and erinacines, which act as Nerve Growth Factor (NGF) enhancing agents, both at the level of expression and secretion. This contribution of Hericium erinaceus has been shown to both prevent (5) and slow cognitive decline and dementia, as well as showing neuroprotective effects.

Several studies and reviews have also demonstrated as mentioned the neuroprotective capacity of Reishi, (Ganoderma lucidum), as well as its preventive and therapeutic effect on neuronal damage and cognitive impairment (9). While other studies have demonstrated its antioxidant effect concluding that, thanks to the ability of its active ingredients to scavenge free radicals, can enhance the reduction of age-related oxidation linked to the (10)

If you are going to consider two medicinal mushrooms for both these conditions these are the two medicinal mushrooms with the most scientific research behind them.

Want to learn more about how medicinal mushrooms can support you brain and mental health? Join us for the Mushrooms & the Mind webinar!


References

1. Li IC, Chang HH, Lin CH, et al. Prevention of Early Alzheimer’s Disease by Erinacine A-Enriched Hericium erinaceus Mycelia Pilot Double-Blind Placebo-Controlled Study. Front Aging Neurosci. 2020;12:155. Published 2020 Jun 3. doi:10.3389/fnagi.2020.00155.

2. Mori K, Inatomi S, Ouchi K, Azumi Y, Tuchida T (2009) Improving effects of the mushroom Yamabushitake (Hericium erinaceus) on mild cognitive impairment: a double-blind placebo-controlled clinical trial. Phytotherapy Research 23, 367-372.

3. Kim, Y. O., Lee, S. W., & Kim, J. S. (2014). A comprehensive review of the therapeutic effects of Hericium erinaceus in neurodegenerative disease. Journal of Mushroom, 12(2), 77-81.

4. Mori K, Obara Y, Hirota M, Azumi Y, Kinugasa S, Inatomi S, Nakahata N (2008) Nerve growth factor-inducing activity of Hericium erinaceus in 1321N1 human astrocytoma cells. Biologicaland Pharmaceutical Bulletin 31, 1727-1732.

5. Li IC, Lee LY, Tzeng TT, et al. Neurohealth Properties of Hericium erinaceus Mycelia Enriched with Erinacines. Behav Neurol. 2018;2018:5802634. Published 2018 May 21. doi:10.1155/2018/5802634.

6. Kawagishi, H., Zhuang, C., & Yunoki, R. (2008). Compounds for dementia from Hericium erinaceum. Drugs of the Future, 33(2), 149.

7. Ma BJ, Shen JW, Yu HY, Ruan Y, Wu TT, Zhao X (2010) Hericenones and erinacines: stimulators of nerve growth factor (NGF) biosynthesis in Hericium erinaceus. Mycology 1,

8. Moldavan M, Grygansky AP, Kolotushkina OV, Kirchhoff B, Skibo GG, Pedarzani P (2007) Neurotropic and trophic action of Lion’s Mane mushroom Hericium erinaceus (Bull.: Fr.) Pers. (Aphyllophoromycetideae) extracts on nerve cells in vitro. International Journal of Medicinal Mushrooms 9, 15-28.

9. Yu, N., Huang, Y., Jiang, Y., Zou, L., Liu, X., Liu, S., … & Zhu, Y. (2020). Ganoderma lucidum triterpenoids (GLTs) reduce neuronal apoptosis via inhibition of ROCK signal pathway in APP/PS1 transgenic Alzheimer’s disease mice. Oxidative medicine and cellular longevity,

10. Huang, S., Mao, J., Ding, K., Zhou, Y., Zeng, X., Yang, W., … & Pei, G. (2017). Polysaccharides from Ganoderma lucidum promote cognitive function and neural progenitor proliferation in mouse model of Alzheimer’s disease. Stem cell reports, 8(1), 84-94.

11. Klaus AS, Kozarski MS, Nikšić MP (2011) Antioxidant properties of hot water extracts from carpophore and spores of mushroom Ganoderma lucidum. Proceedings for Natural Science, Matica Srpska Novi Sad 120, 277-286.

12. ozarski MS, Klaus AS, Nikšić MP (2011) Extract from wild strain of mushroom Ganoderma lucidum as natural antioxidant. Proceedings for Natural Science, Matica Srpska Novi Sad 120, 287-295.

13. Saeger HN, Olson DE. Psychedelic-inspired approaches for treating neurodegenerative disorders. J Neurochem. 2022 Jul;162(1):109-127. doi: 10.1111/jnc.15544. Epub 2021 Dec 5. PMID: 34816433; PMCID: PMC9126991.

Further info

Is Vitamin D Deficiency Driving Dementia?

Everyone knows that vitamin D is vital for healthy bones and a stronger immune system but could low levels also be a major driver of Alzheimer’s and  age-related cognitive decline?

What new research is saying

New research suggests they could, and that levels of vitamin D commonly found in the UK are accelerating cognitive decline and increasing the risk of a dementia diagnosis (1). Supplementing vitamin D, especially in the winter, may reduce future dementia risk.

And it’s not just the UK. A study in France showed that those with low vitamin D levels, below 50nmol/l, had a nearly three-fold increased risk of Alzheimer’s (2). In the UK, over 60 percent of people aged 11 and over have lower levels than this (3).

Supplements also help ward off dementia, according to a large-scale study earlier this year involving over 12,000 dementia-free 70+ year olds (4). More than a third (37%) took supplements of vitamin D and had a 40% lower incidence of dementia. Professor Zahinoor Ismail, of the University of Calgary and University of Exeter, who led the research, said: “We know that vitamin D has some effects in the brain that could have implications for reducing dementia, however so far, research has yielded conflicting results. Overall, we found evidence to suggest that earlier supplementation might be particularly beneficial, before the onset of cognitive decline.”

Did you know we just launched our at-home vitamin D blood tests and MIND Vitamin D Research Project? Will you join our research project and test and track your own vitamin D with us?

If you’re not supplementing vitamin D in the winter they are heading for cognitive decline…

Vitamin D expert and Director of the Sunlight, Nutrition and Health Research Center in San Francisco and a member of our Scientific Advisory Board, Dr William Grant, says we’ve vastly under-estimated the importance of vitamin D on the brain and how much you need.

 “All the evidence for bone and immune health shows that you need a blood level of vitamin D above 75nmol/l to be healthy, and the same is proving true for the brain. This optimal level is impossible to achieve without supplementation in the winter. I recommend every adult and teenager supplement 3,000iu a day from October to March. The government’s recommendation of 400iu (10mcg) is not enough for optimal brain health. Supplementing 800iu (20mcg) a day for 12 months has already been shown to improve cognitive function but you need more than this to achieve anything close to an optimal level.” says Dr Grant. “If you’re not supplementing vitamin D in the winter they are heading for cognitive decline.” Yet only eight percent of UK adults take vitamin D in the winter, says the British Nutrition Foundation (6).

Under the direction of Dr Grant, we have launched a research project to test both vitamin D levels, using a home test kit, and cognitive function, with a free online Cognitive Function Test.

“We have tested over 400,000 people’s cognitive function and now we want to discover their vitamin D levels. This will establish how much vitamin D you really need to stay free from dementia” says Dr Grant.

If you’d like to take part in this research and discover your vitamin D level and cognitive function click here . The free online Cognitive Function test also works out what’s driving future dementia risk and tells you what to do about it


Did you know we just launched our at-home vitamin D blood tests and MIND Vitamin D Research Project? Will you join our research project and test and track your own vitamin D with us?

Thank you for reading!
Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.

References

1 Chai B et al. Vitamin D deficiency as a risk factor for dementia and Alzheimer’s disease: an
updated meta-analysis. BMC Neurol. 2019 Nov 13;19(1):284. doi: 10.1186/s12883-019-
1500-6. PMID: 31722673; PMCID: PMC6854782.


2 Jia J et al. Effects of vitamin D supplementation on cognitive function and blood Aβ-related
biomarkers in older adults with Alzheimer’s disease: a randomised, double-blind, placebo-
controlled trial. J Neurol Neurosurg Psychiatry. 2019 Dec;90(12):1347-1352. doi:
10.1136/jnnp-2018-320199. Epub 2019 Jul 11. PMID: 31296588.


3 https://www.ncbi.nlm.nih.gov/pmc/articles/PMC7353432/pdf/nutrients-12-01868.pdf
4 Ghahremani M et al. Vitamin D supplementation and incident dementia: Effects of sex,
APOE, and baseline cognitive status. Alzheimers Dement (Amst). 2023 Mar 1;15(1):e12404.
doi: 10.1002/dad2.12404. PMID: 36874594; PMCID: PMC9976297.


5 Płudowski P et al Guidelines for Preventing and Treating Vitamin D Deficiency: A 2023
Update in Poland. Nutrients. 2023 Jan 30;15(3):695. doi: 10.3390/nu15030695. PMID:
36771403; PMCID: PMC9920487.

6 Ames BN, Grant WB, Willett WC. Does the High Prevalence of Vitamin D Deficiency in
African Americans Contribute to Health Disparities? Nutrients. 2021 Feb 3;13(2):499. doi:
10.3390/nu13020499. PMID: 33546262; PMCID: PMC7913332.


7 Engelsen O. The relationship between ultraviolet radiation exposure and vitamin D status.
Nutrients. 2010 May;2(5):482-95. doi: 10.3390/nu2050482. Epub 2010 May 4. PMID:
22254036; PMCID: PMC3257661.


8 Ekwaru JP et al The importance of body weight for the dose response relationship of oral
vitamin D supplementation and serum 25-hydroxyvitamin D in healthy volunteers. PLoS
One. 2014 Nov 5;9(11):e111265. doi: 10.1371/journal.pone.0111265. PMID: 25372709;
PMCID: PMC4220998.
9 Feart C et al.. Associations of lower vitamin D concentrations with cognitive decline and
long-term risk of dementia and Alzheimer’s disease in older adults. Alzheimers Dement.
2017 Nov;13(11):1207-1216. doi: 10.1016/j.jalz.2017.03.003. Epub 2017 May 16. PMID:
28522216.


10 https://apigateway.agilitypr.com/distributions/history/4db5dd81-e4c6-4503-b961-
ca44baed4423

Further info

The Shrinking Brain. Are we dumbing down?

Both brain size and IQ are falling in modern humans, coinciding with a big increase in mental illness.

What we eat is to blame, says Professor Michael Crawford, author of a new book ‘The Shrinking Brain’ and Sir David Attenborough is convinced he is right.

The Falling IQ

IQ scores have also been steadily falling for the past few decades. Norwegian researchers, headed by Ole Rogeberg, a senior research fellow at the Ragnar Frisch Center for Economic Research in Norway, analysed the IQ scores of Norwegian men born between 1962 and 1991 and found that scores steadily decreased among those born after 1975 (1). “Similar studies in Denmark, Britain, France, the Netherlands, Finland and Estonia have demonstrated a similar downward trend in IQ scores” says Rogeberg. “The decline is due to environmental factors,” 

This coincides with a change in Western diet away from fat, towards carbohydrates and sugar, based on the mistaken belief that it was fat, not sugar, that was causing heart disease and that we should all eat a low-fat diet. Since then, our IQ scores have been dropping by about 7 per cent per generation. 

“We are heading for an idiocracy” says Professor Crawford who is Director of the Institute of Brain Chemistry and Human Nutrition. Currently one in five of the world’s children and adolescents have a mental health condition (2).’  If this trend continues, by 2080 he predicts that more than a third of the world’s population will have a mental disability.

The World Health Organisation report says ‘there has been a 13% rise in mental health conditions. One in eight now suffers from mental illness. The incidence of depression is through the roof. Last year in the UK there were over 100 million prescriptions for antidepressants. 

Crawford is convinced it is the modern-day diet that is causing us to dumb down. “Our genome is adapted to eating the wild foods we ate during our species’ evolution. Today’s diet bears no resemblance to this.”

Key nutrients from land & sea

In his book, The Shrinking Brain, he says “Our ancestors evolved a unique 1,600cc brain evolving from our ancestral 350cc brain of the chimpanzee, despite our genome only differing by 1.5% (3). This could only have happened by providing brain-specific building nutrients from land and sea. There is incontrovertible evidence of early Homo sapiens exploiting the marine food web in coastal Africa.” In other words, we were the waterside ape who became smart, with bigger brains, by eating mussels, oysters, crabs and fish. 

Professor Crawford discovered, in 1971, that the brains of all mammals are rich in omega-3 DHA. Their brain size varied according to their dietary supply of DHA found in seafood. A dolphin, for example, has a 1,700cc brain, slightly larger than ours, while a lion has a 320cc brain about that of a chimpanzee. “The mix of wildland and aquatic foods powered by the encephalization of the brain from the 340cc of the chimp to the 1,500-1,700 of cro-magnon. DHA is not only involved in signalling but it stimulates gene expression in the brain so the rich aquatic food sources constantly, every day, would have powered the increase in brain size and function.” says Crawford.

“Today’s diet contains less than a tenth of the omega-3 fats that our ancestors ate and this is having dire consequences on mental health. Increased rates of depression, autism, ADHD and dementia are all strongly linked to lack of seafood. Increased intake from eating fish or supplementing omega-3 fish oils reduces dementia risk by 20 per cent (4). While a plant-based diet has many benefits, those who eat no fish, are especially vulnerable and must supplement omega-3 DHA, derived from algae. The only way to be sure you have enough is to get a blood test to specifically test your levels.” Says our CEO and founder Patrick Holford.  

This is why we have just launched a simple ‘do it at home’ pin-prick test that can give you a clear indication of your Omega-3 levels, which done alongside our Cognitive Function Test, can help identify what’s driving future risk and show you how to dementia-proof your diet and lifestyle. 

Canadian neuroscientist and brain expert Professor Stephen Cunnane at the University of Sherbrook in Canada agrees “A shore-based diet, i.e., fish, molluscs, crustaceans, frogs, bird’s eggs and aquatic plants, provides the richest known dietary sources of brain selective nutrients.” says Cunnane. “Change in diet away from marine foods is the likely explanation for this decrease in brain size.”  

Sir David Attenborough, a supporter of the waterside ape theory, agrees “Gathering molluscs is far easier than chasing elephants and wildebeests across the savannah.” 

Children & omega-3

Today, under 5 per cent of children achieve the basic requirement for omega-3 from seafood (5).

Professor Michael Crawford, who is a visiting professor at Imperial College’s Chelsea & Westminster campus and on our Scientific Advisory Board, was part of the team that has recently established that, if a pregnant woman lacks omega-3 DHA she produces a substitute fat, oleic acid, to fill the baby’s brain. But it doesn’t work. Levels of oleic acid in a pregnant woman’s blood predicted preterm birth which carries the highest risk of developmental brain problems and mental deficits in their offspring, as well as a risk of learning and cognitive disabilities. Low omega-3 and B vitamins in mothers increase risk for lower IQ, learning and emotional problems in children (6).

A new study shows that the higher the omega-3 index and DHA, the greater both the brain size and the cognition of older people (7). Brain size predicts cognitive abilities, which is why we have started offering these vital tests – which are both easy and affordable to do at home.

Brain size is worked out from skull capacity. Homo sapiens skulls dating back to 29,000 years ago had a brain capacity of 1,660cc. By 10,000 years ago it was around 1,500cc or 1.5 kilograms. The average brain size today is a fifth smaller, at 1,336cc. Brain size may have started to shrink from 10,000 years ago, coinciding with mankind developing more land-based agriculture and eating less marine food along rivers and coasts.

 So we are inviting you to join our ‘citizen science’ study to track the impact of diet and Omega-3 on cognitive function over time.

Our brains and mental health are suffering as a result of our dietary changes.

So if you are concerned about your levels of Omega-3 and how it might be impacting your brain, body and life – you can now test your levels with our Omega-3 hometest kit here, which is offered alongside the free Cognitive Function Test, which assesses how well your diet is supporting your brain health.

Buy Blood test here button.

Thank you for reading!
Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.

Supporting Research

IQ FALLING

Bratsberg B, Rogeberg O. Flynn effect and its reversal are both environmentally caused. Proc Natl Acad Sci U S A. 2018 Jun 26;115(26):6674-6678. doi: 10.1073/pnas.1718793115. Epub 2018 Jun 11. PMID: 29891660; PMCID: PMC6042097.

DECREASE IN BRAIN SIZE

Cunnane SC, Crawford MA. Energetic and nutritional constraints on infant brain development: implications for brain expansion during human evolution. J Hum Evol. 2014 Dec;77:88-98. doi: 10.1016/j.jhevol.2014.05.001. Epub 2014 Jun 11. PMID: 24928072.

MENTAL HEALTH RISING

https://www.who.int/publications/i/item/9789240049338

OMEGA-3 PREDICTS COGNITIVE PROBLEMS IN CHILDREN

Montgomery P, Burton JR, Sewell RP, Spreckelsen TF, Richardson AJ. Low blood long chain omega-3 fatty acids in UK children are associated with poor cognitive performance and behavior: a cross-sectional analysis from the DOLAB study. PLoS One. 2013 Jun 24;8(6):e66697. doi: 10.1371/journal.pone.0066697.

OMEGA-3 PREDICTS RISK FOR DEMENTIA AND COGNITIVE DECLINE

Wei BZ, Li L, Dong CW, Tan CC; Alzheimer’s Disease Neuroimaging Initiative; Xu W. The Relationship of Omega-3 Fatty Acids with Dementia and Cognitive Decline: Evidence from Prospective Cohort Studies of Supplementation, Dietary Intake, and Blood Markers. Am J Clin Nutr. 2023 Jun;117(6):1096-1109. doi: 10.1016/j.ajcnut.2023.04.001. Epub 2023 Apr 5. PMID: 37028557; PMCID: PMC10447496.

OMEGA-3 LEVELS PREDICT BRAIN SIZE IN OLDER PEOPLE

Loong, S.; Barnes, S.; Gatto, N.M.; Chowdhury, S.; Lee, G.J. Omega-3 Fatty Acids, Cognition, and Brain Volume in Older Adults. Brain Sci.2023,13,1278. https://doi.org/ 10.3390/brainsci13091278 

References

1 Bratsberg B, Rogeberg O. Flynn effect and its reversal are both environmentally caused. Proc Natl Acad Sci U S A. 2018 Jun 26;115(26):6674-6678. doi: 10.1073/pnas.1718793115. Epub 2018 Jun 11. PMID: 29891660; PMCID: PMC6042097.

3 Cunnane SC, Crawford MA. Energetic and nutritional constraints on infant brain development: implications for brain expansion during human evolution. J Hum Evol. 2014 Dec;77:88-98. doi: 10.1016/j.jhevol.2014.05.001. Epub 2014 Jun 11. PMID: 24928072.

4 Wei BZ, Li L, Dong CW, Tan CC; Alzheimer’s Disease Neuroimaging Initiative; Xu W. The Relationship of Omega-3 Fatty Acids with Dementia and Cognitive Decline: Evidence from Prospective Cohort Studies of Supplementation, Dietary Intake, and Blood Markers. Am J Clin Nutr. 2023 Jun;117(6):1096-1109. doi: 10.1016/j.ajcnut.2023.04.001. Epub 2023 Apr 5. PMID: 37028557; PMCID: PMC10447496.

5 Kranz, S.; Jones, N.R.V.; Monsivais, P. Intake Levels of Fish in the UK Paediatric Population. Nutrients 2017, 9, 392. https://doi.org/10.3390/nu9040392

6 Montgomery P, Burton JR, Sewell RP, Spreckelsen TF, Richardson AJ. Low blood long chain omega-3 fatty acids in UK children are associated with poor cognitive performance and behavior: a cross-sectional analysis from the DOLAB study. PLoS One. 2013 Jun 24;8(6):e66697. doi: 10.1371/journal.pone.0066697. Erratum in: PLoS One. 2013;8(9); see also Veena SR, Krishnaveni GV, Srinivasan K, Wills AK, Muthayya S, Kurpad AV, Yajnik CS, Fall CH. Higher maternal plasma folate but not vitamin B-12 concentrations during pregnancy are associated with better cognitive function scores in 9- to 10- year-old children in South India. J Nutr. 2010 May;140(5):1014-22. doi: 10.3945/jn.109.118075. Epub 2010 Mar 24. PMID: 20335637; PMCID: PMC3672847; see also McNulty H, Rollins M, Cassidy T, Caffrey A, Marshall B, Dornan J, McLaughlin M, McNulty BA, Ward M, Strain JJ, Molloy AM, Lees-Murdock DJ, Walsh CP, Pentieva K. Effect of continued folic acid supplementation beyond the first trimester of pregnancy on cognitive performance in the child: a follow-up study from a randomized controlled trial (FASSTT Offspring Trial). BMC Med. 2019 Oct 31;17(1):196. doi: 10.1186/s12916-019-1432-4. PMID: 31672132; PMCID: PMC6823954.

7 Loong, S.; Barnes, S.; Gatto, N.M.; Chowdhury, S.; Lee, G.J. Omega-3 Fatty Acids, Cognition, and Brain Volume in Older Adults. Brain Sci.2023,13,1278. https://doi.org/ 10.3390/brainsci13091278 

Further info

How to cut your dementia risk by three quarters.

Developing dementia is the second biggest health fear, after cancer. But what can you do about it? 

The conventional view is that genes play a big part and that factors under our control, including diet, lifestyle and health status, account for up to 40% of risk and therefore up to 40% of dementia cases could be prevented or delayed. Genes actually account for less than 1% of Alzheimer’s cases. But a new study from the UK BioBank, following 344,000 people over 15 years, estimates that “up to 73% of cases could be prevented” by targeting risk factors largely under our control. 

The authors of the study, published in the Nature Human Behaviour journal (1), investigated 210 modifiable risk factors. They found that increased hand grip strength (a good reflection of physical strength), increasing leisure or social activities or time spent in sports clubs or gyms, spending less time watching TV or on a computer, having better dental health, drinking more water, not dozing off in the day and sleeping between 7 to 9 hours a night, not smoking or being exposed to smoke and having better lung function were all associated with less risk of Alzheimer’s. Being unemployed, having a low income, having diabetes, high blood pressure or having had a stroke or brain injury all increased risk. Inheriting the so-called ‘Alzheimer’s gene’, ApoE4, didn’t make any significant difference to overall risk.

However, even this figure of 73% may be an underestimate as this study excluded blood test measures. “We have under-estimated the power of prevention,” says Professor David Smith from the University of Oxford, one of the study authors. “Even this figure of up to 73% of cases preventable could be higher if a person’s omega-3 and B vitamin status, measured by a blood test for homocysteine that any GP can do, were taken into account.”

While the BioBank study didn’t include blood test measures of either homocysteine or omega-3, scientists at the US National Institutes of Health have attributed 22% of the risk of Alzheimer’s to raised blood homocysteine and 22% to a lack of omega-3 (2). “These have been shown to predict risk but were beyond the scope of this study.” confirmed the study author, Professor Jin-Tai Yu from Shanghai’s Fudan University. “Homocysteine-lowering treatment with B vitamins, especially B12, is one of the most promising interventions for dementia prevention.” 

The Impact of B Vitamins & Omega-3

Professor Smith’s group at Oxford University tested the effects of giving B vitamins (B6, B12, folate) versus placebo to those with pre-dementia and found that the 10p a day supplements halved the rate of brain shrinkage in one year and virtually stopped further memory loss (3). “The greatest effect we found in our trial was in those in the top third of DHA blood levels (an omega-3 found in fish or fish oil supplements). Those with high DHA reduced their rate of brain shrinkage by 73%, down to the level normally seen in older people with loss of cognitive function. They also had virtually no further memory loss and almost a third ended the trial with no clinical dementia rating at all.”

The benefit of omega-3 was also confirmed in a major study this year of over 100,000 people, finding that increased omega-3 cut the risk of dementia or cognitive decline by around 20%. An increase in intake of omega-3 DHA of 200 mg decreased risk by almost a fifth (4). 

And here at Food for the Brain, we take prevention seriously.

Alzheimer’s is preventable, but not curable

We developed the free online Cognitive Function Test,  which includes a Dementia Risk Index questionnaire assessing your diet, omega-3 and B vitamin status, and lifestyle and an optional home-test kit for pinprick blood tests that will be available soon.

“Over 400,000 people have taken our validated Cognitive Function Test, which not only shows a person their cognitive status right now but also their future risk based on our Dementia Risk Index questionnaire, the factors driving future risk and what they can easily do right now to lower it. If all modifiable risk factors are taken into account, including B vitamins and omega-3, it is highly likely a person could reduce risk by over 80%.” says our CEO, Patrick Holford.

“The government has pledged £160 million a year for dementia prevention research but we are not seeing any of this going into easy prevention wins. Most seem to be fueling drug research for an apparent ‘cure’.

Alzheimer’s is preventable, but not curable. You cannot reverse holes in the brain. With over 200,000 people diagnosed every year with dementia, if prevention were taken seriously we could halve the number of people developing this terrible, but preventable disease.”

Test Your Cognitive Function Now green banner.

—-

Thank you for reading!
Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.

———

References
Further info

Study Finds Mediterranean and MIND Diets Are Linked to Fewer Alzheimer’s Brain Changes

Study Finds Mediterranean and MIND Diets Are Linked to Fewer Alzheimer’s Brain Changes

“People who scored highest for adhering to the Mediterranean diet had average plaque and tangle amounts in their brains similar to being 18 years younger than people who scored lowest.”

Foods commonly included in the MIND diet for Alzheimer's disease and the Mediterranean diet, including salmon, vegetables, olive oil, nuts, whole grains and berries. These foods are associated with healthy eating patterns studied for brain health and amyloid plaques.

Research suggests these eating patterns may help support long-term brain health

Following a Mediterranean or MIND diet has consistently been associated with better cognitive health. In recent years, the connection between the mind diet, Alzheimer’s disease and overall brain health has become a focus of research. Research also suggests that people who adhere more closely to these dietary patterns have fewer of the brain changes associated with Alzheimer’s disease.

One study published in Neurology found that people who most closely followed the Mediterranean or MIND diet had fewer amyloid plaques and tau tangles, the two hallmark features of Alzheimer’s disease. They also had lower overall Alzheimer’s pathology at autopsy.

Although this research cannot prove that diet prevents Alzheimer’s disease, it adds to a growing body of evidence linking healthy dietary patterns with better brain health as we age.

Key Findings

  • A 2023 study found that people who more closely followed Mediterranean or MIND diets had fewer Alzheimer’s related brain changes, including lower levels of amyloid plaques.
  • Participants with the highest adherence to the MIND diet had levels of Alzheimer’s pathology comparable to those seen in people around 12 years younger than those with the lowest adherence.
  • Even meeting the recommended intake for just one food group, such as vegetables or fruit, was associated with lower amyloid pathology, equivalent to around four years less brain ageing.
  • Higher consumption of green leafy vegetables showed one of the strongest associations with lower Alzheimer’s disease pathology.
  • Mediterranean and MIND diets, rich in vegetables, berries, whole grains, olive oil, fish, legumes, and nuts, were associated with lower Alzheimer’s disease pathology.

One of the study’s most striking findings was that participants with the highest adherence to the MIND diet had levels of amyloid plaques and tau tangles comparable to those seen in people around 12 years younger than those with the lowest adherence. This comparison reflects differences in Alzheimer’s-related brain pathology rather than actual biological age.

The researchers also found that even meeting the recommended intake for a single food group, such as vegetables or fruit, was associated with lower amyloid pathology, equivalent to around four years less brain ageing. The strongest association was seen with green leafy vegetables, with people eating the most greens showing substantially fewer Alzheimer’s-related brain changes than those eating the least.

What are amyloid plaques and tau tangles?

Amyloid plaques are deposits of beta amyloid protein that accumulate between brain cells. Tau tangles are abnormal bundles of tau protein that build up inside neurons.

Both are considered hallmark features of Alzheimer’s disease and are commonly found in the brains of people with dementia.

However, Alzheimer’s disease is complex. Scientists now recognise that inflammation, vascular disease, genetics, insulin resistance and other lifestyle factors all contribute to the disease process. Amyloid and tau are important, but they are only part of the story.

Can diet reduce amyloid plaques?

There is currently no evidence that any diet can remove existing amyloid plaques.

However, research suggests that people who consistently follow dietary patterns such as the Mediterranean and MIND diets tend to have fewer Alzheimer’s-related brain changes and a lower risk of cognitive decline.

Rather than reversing Alzheimer’s disease, these diets appear to support long-term brain health through multiple mechanisms, including reduced inflammation, improved vascular health and better overall nutrition.

Why might diet influence brain health?

Researchers believe several mechanisms may explain these findings.

Healthy dietary patterns are rich in nutrients that may help:

  • reduce chronic inflammation
  • improve blood flow to the brain
  • protect brain cells from oxidative stress
  • support healthy nerve cell function
  • maintain cardiovascular health, which is closely linked to brain health

Rather than relying on a single nutrient, these dietary patterns combine many foods that work together over time.

Why were leafy greens highlighted?

Among all the foods analysed, green leafy vegetables showed one of the strongest associations with lower Alzheimer’s pathology.

Leafy greens provide several nutrients that support normal brain function, including:

  • folate
  • vitamin K
  • lutein
  • magnesium
  • dietary nitrates

Although researchers cannot say that leafy greens alone reduce Alzheimer’s risk, regularly eating them is consistently associated with better cognitive ageing across multiple studies. The findings from this study suggest that increasing the intake of foods such as leafy greens, berries, whole grains, olive oil and fish as part of an overall healthy dietary pattern may help support long-term brain health.

How strong is the evidence?

This study was observational, meaning it identified associations rather than proving cause and effect.

That means researchers cannot conclude that the Mediterranean or MIND diet directly prevented Alzheimer’s disease.

However, these findings are consistent with many previous studies linking healthy dietary patterns with better cognitive health and a lower risk of dementia.

Taken together, the evidence suggests that diet is likely to be one important part of maintaining brain health, alongside regular physical activity, quality sleep, social engagement and management of cardiovascular risk factors.

What this research means?

This study adds another piece to the growing evidence that long-term dietary habits may influence how the brain ages.

Rather than focusing on individual “superfoods,” the findings support the importance of an overall healthy eating pattern that includes plenty of vegetables, healthy fats, legumes, whole grains and other minimally processed foods.

While more research is needed, studies suggest that the Mediterranean and MIND diets may help reduce Alzheimer’s disease related brain changes and support long term brain health when followed consistently as part of a healthy lifestyle.

Practical takeaways

Research suggests that long-term eating habits can help support brain health and may reduce the risk of cognitive decline. Rather than focusing on individual foods, aim to build an overall healthy eating pattern. Simple habits that align with current evidence include:

  • Eat green leafy vegetables several times a week.

  • Include fish in your diet regularly, particularly oily fish rich in omega-3 fats.

  • Choose extra virgin olive oil as your main cooking fat.

  • Eat plenty of vegetables, legumes and whole grains.

  • Enjoy berries and a handful of nuts regularly.

  • Limit highly processed foods, sugary drinks and foods high in saturated fat.

  • Combine healthy eating with regular physical activity, quality sleep and good cardiovascular health.

The greatest benefits are likely to come from following these habits consistently over many years, rather than relying on short-term dietary changes or individual foods or supplements.

Want to learn more? Explore our guide to the Mediterranean and MIND diets to discover how these eating patterns compare and how to incorporate them into your daily routine.


Further info
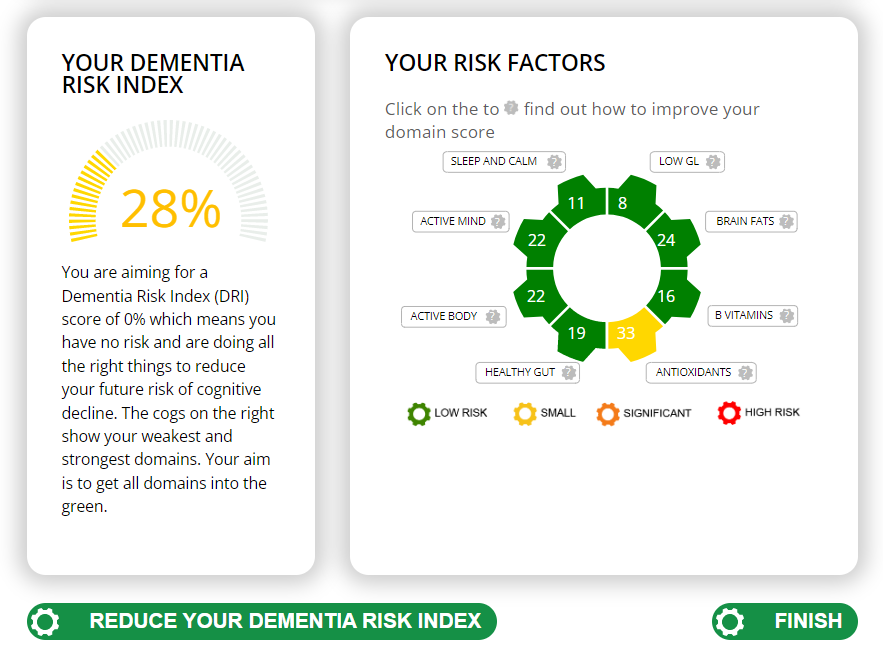
Supplementing vitamin D helps reduce Alzheimer’s disease and dementia risk

By Patrick Holford

Taking vitamin D supplements may help ward off dementia, according to a new, large-scale study involving over twelve thousand dementia-free 70+ year olds in the US. More than a third (37%) took supplements of vitamin D. After adjusting for baseline age, sex, education, race, cognitive diagnosis, depression, and APOE4 status, exposure to prescribed vitamin D supplements was associated with 40% lower incidence of dementia during a ten-year period.

The study, carried out by researchers from the University of Calgary’s Hotchkiss Brain Institute in Canada and the University of Exeter in the UK, has been published in the journal Alzheimer’s & Dementia. The team found that taking vitamin D was associated with living dementia-free for longer, and they also found 40 per cent fewer dementia diagnoses in the group who took supplements.

Professor Zahinoor Ismail, of the University of Calgary and University of Exeter, who led the research, said: “We know that vitamin D has some effects in the brain that could have implications for reducing dementia, however so far, research has yielded conflicting results. Our findings give key insights into groups who might be specifically targeted for vitamin D supplementation. Overall, we found evidence to suggest that earlier supplementation might be particularly beneficial, before the onset of cognitive decline.”

One of the problems in relation to vitamin D and cognition is the use of variable amounts of vitamin D, and the lack of reporting regarding blood levels at baseline and conclusion of trials. This study has the same issue. We do not know the dose taken nor the starting and end blood levels of those supplementing or not.

A review by Dr William Grant, Director of Sunlight, Nutrition and Health Research Center, who is the expert on our Scientific advisory Board shows that the higher the blood level of vitamin D (25-hydroxyvitamin D [25(OH)D] is the form measured in the blood serum) the lower is the risk of developing Alzheimer’s as well as dementia in general. The mechanisms identified as potentially explaining its benefit include reduced brain aging, cellular senescence, mitochondrial dysfunction and oxidative stress as well as higher high-density lipoprotein (HDL). Observational study findings indicate that blood levels above 30 ng/mL (75 nmol/L) reduce dementia risk by about 40% and Alzheimer’s risk by about 30% compared to those with blood levels below 12 ng/mL (30 nmol/L) which is broadly consistent with the scale of benefit reported in this trial. You can read Dr William Grant’s full review entitled “The role of vitamin D in reducing risk of Alzheimer’s disease” here.

 “In this study, while Vitamin D was effective in all groups, the team found that the beneficial effects were significantly greater in females, compared to males. Similarly, effects were greater in people with normal cognition, compared to those who reported signs of mild cognitive impairment – changes to cognition which have been linked to a higher risk of dementia.

Dr William Grant says “It is unlikely that vitamin D supplementation is of much use for treating advanced stages of these diseases, although it would be useful in reducing risk of other vitamin D-sensitive adverse health outcomes.” Overall, he says “The evidence regarding vitamin D satisfies the criteria for causality in a biological system for reducing risk of cognitive function, Alzheimer’s and vascular dementia. Thus, vitamin D supplementation can be recommended as an additional way to reduce risk of these diseases. It should also be useful for reducing the rate of progression of these diseases.”

The mechanism(s) for explaining the beneficial effects of vitamin D are not yet clear, however one interesting finding was that the effects of vitamin D were also significantly greater in people who did not carry the APOEe4 gene, known to present a higher risk for Alzheimer’s dementia, compared to non-carriers. The authors suggest that people who carry the APOE4 gene absorb vitamin D better from their intestine, which might reduce the vitamin D supplementation effect due to higher baseline vitamin D levels. However, no blood levels were drawn to test this hypothesis.

Co-author Dr Byron Creese, at the University of Exeter, said: “Preventing dementia or even delaying its onset is vitally important given the growing numbers of people affected.  The link with vitamin D in this study suggests that taking vitamin D supplements may be beneficial in preventing or delaying dementia, but we now need clinical trials to confirm whether this is really the case.  The ongoing VitaMIND study at the University of Exeter is exploring this issue further by randomly assigning participants to either take vitamin D or placebo and examining changes in memory and thinking tests over time.”

Dr Linus Pauling, the only person ever to win two unshared Nobel Prizes, and the father of modern chemistry, together with Dr Abram Hoffer, who inspired us to set up the Food for the Brain Foundation, first conceptualised ‘orthomolecular medicine’, also called ‘optimum nutrition’ and ‘functional medicine’ as the new paradigm in medicine with nutrition at the centre. He was Patron of the Institute for Optimum Nutrition. Each lived healthily into their 90’s with minds as sharp as razors until the end.

At Food for the Brain those taking the Cognitive Function Test also answer questions about their use, and level of vitamin D, if known. We hope, soon, to start offering vitamin D testing to further research the effects of vitamin D in relation to cognitive decline to be able to track progress both cognitive changes against vitamin D blood levels and intake, to help determine an optimal daily intake or blood level. We are also working with the charitable Grassroots Health Nutrient Research Institute who have tested thousands of people’s blood vitamin D level and are now encouraging them to take Food for the Brain’s Cognitive Function Test. You can join their Vitamin D action group here.

Listen to Patrick Holford’s podcast explaining the role of vitamin D in Alzheimer’s disease here.

Further info

What’s driving Alzheimer’s and vascular dementia?

By Patrick Holford

How does cognitive decline happen?

One theory was that it was to do with the accumulation of amyloid protein, producing amyloid plaque that interferes with brain cell communication. But, despite over 30 clinical trials, lowering amyloid protein has had close to zero clinical effect. But, even if this was part of the problem, one would have to ask why?

There are plenty of left-field theories. One, for example, is that it’s an auto-immune disease whereby the brain starts to destroy itself. There are plenty of diet and lifestyle diseases that tip over into auto-immune diseases. For example, type-2 diabetes can convert to type-1 diabetes and osteoarthritis can convert to rheumatoid arthritis. But even so, one would have to ask why? What would be driving this?

Risk Factors for Alzheimer’s – what do they have in common?

There are over 20 known risk factors that predict future risk for cognitive decline, dementia and/or Alzheimer’s. These include:

  • Anon-adherence to Mediterranean diet principles
  • Cardiovascular disease, and high blood pressure
  • Depression/social isolation/loneliness
  • Diabetes
  • Genes (such as senilin) and predisposing genes (eg ApoE4)
  • Head trauma
  • High blood homocysteine (a measure of B vitamins)
  • Insulin resistance
  • Lack of antioxidants/polyphenols in plant foods
  • Lack of cognitive stimulation
  • Lack of exercise and muscle mass – frailty
  • Lack of folate, B12 and B6
  • Lack of sleep
  • Low education level
  • Low phospholipid and choline intake (in eggs and fish)
  • Low seafood consumption and a lack of omega-3
  • Low sunlight exposure
  • Low vitamin C, D and E intake
  • Low zinc levels
  • Medication – antiacids, metformin, diuretics
  • Metabolic syndrome
  • Poor gut health and dental health
  • Poor hearing
  • Smoking
  • Stress
  • Strokes and TIAs (transient ischemic attacks )
  • Too much sugar, refined, processed, carb-rich foods

So far researchers have looked at individual known risk factors for Alzheimer’s, then tried to change them with some success. The nutritionists have tried to change diet, or give supplements. The pharmacologists have tried to give drugs to lower, for example, high blood pressure or insulin levels. The psychologists have tried to increase cognitive stimulation and address depression and isolation, and insomnia. The sports physiologists have tried to increase exercise. But what do all these factors have in common? Is there a way of looking that ties all these risk factors together into an understanding as to what is actually driving dementia?

The old, but still dominant mindset in science is ‘reductionism’. The idea is to look at one thing, or one risk factor, then change it in a randomised placebo-controlled trial. The idea is that if everyone does this then you could pool all the interventions together to produce a cure. This reminds me of a comment made in the G8 summit on dementia in 2010, in London, when we succeeded in getting a discussion on dementia prevention added to the agenda. The pharma representative said words to the effect of ‘we will solve dementia with multiple drugs, just like we solved AIDS’. The reality is studies giving drugs[1] to lower blood sugar for diabetics, lower blood pressure with anti-hypertensive drugs, lower cholesterol with statins, even lower amyloid protein, have failed. The official cost of all this research is $42.5 billion to date.[2] This is five times more than the cost of the James Webb telescope. This approach clearly isn’t working. The only ‘drugs’ that have worked are homocysteine lowering B vitamins and omega-3 fish oils – and the recent discovery is that they work together, in cooperation.

There’s a new emerging way of doing science which is called ‘systems-based’ science. The physicist, Fritjof Capra, has explained this way of doing science in his book ‘The Web of Life’. He says “Systems thinking emerged from a series of interdisciplinary dialogues among biologists, psychologists, and ecologists, in the 1920s and ’30s. In all these fields, scientists realized that a living system—organism, ecosystem, or social system—is an integrated whole whose properties cannot be reduced to those of smaller parts. The “systemic” properties are properties of the whole, which none of its parts have. So, systems thinking involves a shift of perspective from the parts to the whole. The early systems thinkers coined the phrase, “The whole is more than the sum of its parts.”[3]

Us humans are a complex adaptive system. What’s also been learnt about complex adaptive systems is that they have a certain amount of ‘resilience’ which you can think of as the credit in your health deposit account. When that runs out, disease occurs. Many leaders in the field of nutritional and naturopathic medicine consider that many of the same underlying processes are going wrong in our bodies, which then cause the emergence of a ‘disease’ depending on the organ it strikes – so heart disease, diabetes, arthritis and dementia have similar contributing factors.

At Food for the Brain, we can organise all these risks above into eight domains shown below. It is certainly true that these eight domains of ‘risk’ cover much of what we know about the risks for heart disease, diabetes and arthritis, for example. This partly, but not fully. answers the question about what is actually driving dementia.

The Eight Domains of Dementia Risk

Another understanding within systems-based thinking is well illustrated by asking the question ‘what is the difference between an inanimate object, like a bicycle, and an animate organism, such as us?’ A bicycle has ‘parts’ and the parts related to each other, as in functioning together. So do we. But also, there is ‘life’ running through us. You can imagine your brain’s neural network lighting up, with ‘energy’ or signals shooting this way and that. If you have healthy parts, all functioning, but no signals, you’re kind of ‘switched off’.

We call the parts – structure; the relationship of the parts – function; and the life running through the neural network – utilisation. These are shown visually below in a way to illustrate that they are integral, with each dependent on the other.

Now, let’s reorganise all those risk factors accordingly into whether they are primarily required for the structure or function of the neural network, or send messages across it.

Protecting the Structure of Your Brain

If you’ve watched the short animated film ‘how to keep building brain cells at any age‘ you’ll know that the membrane of every brain cell is made by binding omega-3 DHA, rich in seafood, to phospholipids and especially Phosphatidylcholine, rich in eggs and fish, to produce what called ‘phosphorylated DHA’. You need this to have a functioning brain. It actually makes up more than 90 per cent of the structure of your brain.

You’ll also know that the ‘binding’ of these two parts depends on B vitamins, which drive a process called methylation. So, without enough B vitamins your brain and nervous system fall apart. The best measure of methylation, and whether you are getting enough B vitamins, is your blood homocysteine level.  If your homocysteine level is high, you’ve got a problem. Above 11mcmol/l and you’ve got a shrinking brain. More than half of all people over 70 have a homocysteine level above this. It should, therefore, be no surprise to find that, if you have a raised homocysteine level, and are given B vitamins, if you also have a low omega-3 DHA intake or blood level, the B vitamins won’t work. Conversely, if you supplement omega-3 fish oils, but have a raised homocysteine level or lack of B vitamins, the omega-3 won’t work. The full story of the dynamic duo of Omega-3 and  B vitamins is explained here.

It is likely that choline deficiency, which is especially common in those who rarely eat fish or eggs, may also create a similar structural problem in the brain. In animals supplementing choline prevents Alzheimer’s related brain changes.[4]

Protecting the Function of Your Brain

There are many aspects of ‘function’ of the brain. Using a simple car analogy, one thinks of the need for fuel and the need for oil to lubricate the parts. The two main fuels of brain cells are either glucose, derived from carbs, or ketone derived from fat.

If you’ve watched the animated film ‘how to fuel your brain for better memory’, you’ll know about the need for slow-releasing carbs and ketones from a type of fat called a medium chain triglyceride (MCT) and specifically C8 oil.

Too much sugar, and especially fructose and high fructose corn syrup (now used by the food industry to sweeten foods), and too much refined carbohydrates interferes with fuel supply to brain cells by making you ‘insulin resistant’. Insulin receptors, embedded in neuronal membranes, transport glucose into brain cells. If these receptors, which are like doors, are largely shut down, the brain starves of clean fuel. Read professor Robert Lustig’s article “Is sugar killing your brain?’ for the full story.

The alternative brain fuel – ketones, which neurons actually prefer, can be made in the liver from a type of fat called C-8 (caprylic acid triglyceride) which makes up 7 per cent of coconut oil. In a study giving people with memory problems two tablespoons of C8 oil, their brains produced 230 per cent more energy from ketones and their memory improved. The article ‘Is fat the best brain fuel?’ gives you the full story.

The lubricating ‘oil’ in a car analogy would be both dealing with the ‘exhaust fumes’ of the brain’s energy production, namely oxidants. These are mopped up by antioxidants and polyphenols rich in plant foods. That where food such as blueberries and cacao, or vitamin C and E, come in. It’s also why smoking is such a big risk factor.

Another part of ‘function’ is circulation – anything that improves circulation helps the function. Many of the things we’ve mentioned –  lowering homocysteine with B vitamins, omega-3, antioxidants, polyphenols – also help circulation.

Another part of ‘function’ is inflammation. Behind all those ‘metabolic’ diseases -diabetes, heart disease, arthritis to name a few – lies inflammation which doesn’t just affect the specific organ, be it heart of joint, but also the brain.

Use it or Loss it – Why Your Brain Needs Stimulation

One of our experts, Tommy Wood, assistant research professor at the University of Washington in Seattle, focussing on neuroscience, has developed an excellent model for understanding the ‘use it or lose it’ principle. He’s big into exercise.

‘Exercise is important because it makes the brain do things that keep it healthy, such as growth and repair and maintaining temperature and weight,’ he says. ‘When they aren’t stimulated, the health of brain tissues deteriorates with a knock-on effect on memory and thinking.’

And it’s not just physical exercise that does this, we also benefit from the mental exercise involved in likes of solving puzzles or learning a new language. ‘For many people the worst thing they can do for their brain is to retire’, says Wood. ‘They lose much of the stimulation that kept it healthy.’

Sleep as a brain protector also fits in here. It’s vital for recovering from both physical and intellectual exercise and to store and organise what you have learnt in the day.

‘But sleep and exercise aren’t enough on their own,’ Wood continues. ‘All that repair and maintenance needs a good supply of nutrients.’

Taken from J.Turknett & T.Wood, Cells 2022, 11, 2789, used with permission.

Stress also fits in here because stress, as well as environmental and dietary ‘pollution’ be it from drinking and smoking, dirty air, moulds, even allergens like gluten with can induce ‘brain fog’ often experienced by those with coeliac disease, promote inflammation and inhibit repair and regeneration.

A Unified Model for the Drivers of Cognitive Decline

This systems-based approach to what’s potentially driving cognitive decline makes it obvious that there will never be a single drug or single factor that stops a person developing dementia. Instead, if a person has enough ‘interference’ with the structure, function or utilisation of their brain then there will, inevitably be cognitive decline with age.

At Food for the Brain, when you complete your Cognitive Function Test, you know objectively how you are doing and how much room for improvement there is. Then you are invited to complete the Dementia Risk Index questionnaire, which not only gives you a score out of 100% (you are aiming for a score closer to 0%) but also shows you in which domain you have the most room for improvement.

Cognitive Function Test Dashboard

You are then invited to join COGNITION, which is an interactive brain upgrade programme that targets your weakest areas and shows you the simplest changes that will make the biggest difference to reduce your risk.

The goal is to turn all your reds, oranges and yellows into green, then reassess your cognitive function. By joining you are becoming part of a group of hundreds of thousands of citizen health scientists helping to discover what really works to dementia-proof your diet and lifestyle.


References

[1] Peters R, Breitner J, James S, Jicha GA, Meyer PF, Richards M, Smith AD, Yassine HN, Abner E, Hainsworth AH, Kehoe PG, Beckett N, Weber C, Anderson C, Anstey KJ, Dodge HH. Dementia risk reduction: why haven’t the pharmacological risk reduction trials worked? An in-depth exploration of seven established risk factors. Alzheimers Dement (N Y). 2021 Dec 8;7(1):e12202. doi: 10.1002/trc2.12202. PMID: 34934803; PMCID: PMC8655351.

[2] Cummings JL, Goldman DP, Simmons-Stern NR, Ponton E. The costs of developing treatments for Alzheimer’s disease: A retrospective exploration. Alzheimers Dement. 2022 Mar;18(3):469-477. doi: 10.1002/alz.12450. Epub 2021 Sep 28. PMID: 34581499; PMCID: PMC8940715.

[3] Fritjof Capra (2009) The New Facts of Life: Connecting the Dots on Food, Health, and the Environment, Public Library Quarterly, 28:3, 242-248, DOI: 10.1080/01616840903110107

[4] Velazquez R, Ferreira E, Knowles S, Fux C, Rodin A, Winslow W, Oddo S. Lifelong choline supplementation ameliorates Alzheimer’s disease pathology and associated cognitive deficits by attenuating microglia activation. Aging Cell. 2019 Dec;18(6):e13037. doi: 10.1111/acel.13037. Epub 2019 Sep 27. PMID: 31560162; PMCID: PMC6826123.


Further info

Diet, not genes, is driving dementia says British Medical Journal

A hugely significant study in the British Medical Journal into age-related cognitive decline and dementia has stated that changing your diet and lifestyle from bad to good cuts your future risk of developing dementia by a massive nine times [1]

The study shows, significantly, that whether or not you inherit the ApoE4 ‘Alzheimer’s gene’ that one in five people carry, it makes no difference to the positive reduction in risk achievable by simple diet and lifestyle changes [2].

Eating a healthy diet was also the most important prevention step, followed by an active lifestyle, with one’s intellectual life, then physical activity, then social interactions being the next most important steps. Eating a healthy diet was about twice as important as exercise in predicting cognitive decline.

This study, published on 25th January 2023, followed over 30,000 people over a decade and found that those with a healthy diet were about seven times less likely to have age-related cognitive decline or dementia than those with an ‘average’ diet and about nine times less likely to develop dementia than those with an unfavourable diet.

The assessment of a healthy diet was based on intake of fish, eggs, fruits, vegetables, legumes, nuts and tea, among other foods known to predict lower risk.

Increasing evidence that Alzheimer’s and Dementia are preventable

“These results provide an optimistic outlook, as they suggest that although genetic risk is not modifiable, a combination of more healthy lifestyle factors are associated with a slower rate of memory decline, regardless of the genetic risk,” wrote the study authors.

This study has been warmly welcomed by charity Food for the Brain, as it backs up their own research and the work they have been actively carrying out for 10  years, to help people reduce their risk of age-related cognitive decline.

Food for the Brain offers a free online assessment of a participant’s diet and lifestyle, called the Dementia Risk Index, which works out a person’s overall risk. The assessment also includes a cognitive function test to assess your memory. This charitable ‘citizen science’ action group have also just launched COGNITION, an interactive, personalised ‘brain upgrade’ programme that then shows you, week-by-week, how to make positive changes to bring your risk closer to zero.

Indeed, the on-line test assesses all the same risk factors the British Medical Journal study has shown impact a person’s future risk – diet, active physical, intellectual, social lifestyle, smoking and drinking habits.  

According to Professor David Smith from the University of Oxford, one of the charity’s scientific advisors, “Genes can only exert effects via non-genetic mechanisms and these mechanisms are often susceptible to modification by, for example, improving one’s diet. This study shows that diet and lifestyle are much more important than inheriting a gene variant such as ApoE4. Less than 1% of Alzheimer’s is directly caused by genes. With no clinically effective drugs, and minimal role of genes, this study confirms that the focus must be on making diet and lifestyle changes that reduce risk of developing dementia, as foodforthebrain.org are doing. It also shows that switching from an average to a healthy lifestyle, with positive diet changes being key, can dramatically reduce a person’s future risk of developing cognitive decline and dementia.” 

Another member of the science team, Dr Celeste de Jager Loots, Research Associate at Imperial College’s  AGE Unit where she researches risk factors and prevention of Alzheimer’s and dementia, explains that “While having inherited certain genes can be used to predict risk of dementia, that risk is changed by making positive diet and lifestyle changes. The emphasis needs to be on changing diet and lifestyle, especially since one cannot change one’s genes. The earlier one starts with a healthy lifestyle the better the chance of preventing effects of genetic risk.”

Risk for dementia can be detected from the age of 35 and subtle changes, picked up by Food for the Brain’s cognitive function test, can be seen up to 40 years before a diagnosis. The charity wants anyone over 35 to take the test and start making positive diet and lifestyle changes. “The average person can cut their future risk by three quarters just by making simple diet and lifestyle changes.” says Patrick Holford, who is directing the Alzheimer’s prevention project. “This prevention approach, if we reach enough people, could cut cases of dementia in the UK by a third. That’s why we are urging everyone over 35 to tell everyone they know to take the free and scientifically – validated and free Cognitive Function Test. Alzheimer’s dementia, which accounts for the vast majority of dementia, is irreversible. But it is preventable, as this study shows.”

Two thousand people every month are joining this campaign, assessing and reducing their risk. Over 380,000 people have now taken the test.

References

Jia, J. et al. (2023) “Association between healthy lifestyle and memory decline in older adults: 10 year, population based, prospective Cohort Study,” BMJ [Preprint]. Available at: https://doi.org/10.1136/bmj-2022-072691. [1]

The evidence that only 1% of Alzheimer’s is caused by genes is here: Bekris, L.M. et al. (2010) “Review article: Genetics of Alzheimer Disease,” Journal of Geriatric Psychiatry and Neurology, 23(4), pp. 213–227. Available at: https://doi.org/10.1177/0891988710383571. [2]

Useful links

For more information on the citizen science campaign see ‘Alzheimer’s is Preventable – A Manifesto for Change’.

Patrick Holford, founder of Food for the Brain and voluntary director of the Alzheimer’s Prevention Project and Jessica Ferrari-Wells, Chair of the Board of trustees are available for interview, as are members of the the Scientific Advisory Board are available for interview and comment. 

Further info

The Origin of Alzheimer’s Disease

By Patrick Holford

Brain shrinkage left, normal brain right

Why Dementia rates are higher in the west

In some countries, for example India and China, that proportion appears to be less than half that occurring in Britain. When people in one country suffer much more from a disease than people of a similar age in another country, this is a sure sign that the difference has something to do with diet, lifestyle or other environmental factors – or genetic variance. We can rule out genetic differences as the major factor, particularly because Chinese and Indian people who emigrate to Britain soon acquire a similar risk for developing dementia. In any event only one in a hundred cases of Alzheimer’s is caused by genes.2

How many people get diagnosed with dementia?

A decline in memory and concentration is not the same thing as a diagnosis of dementia or probable Alzheimer’s, although it does mean your chances of developing these conditions are higher. Every year roughly 10 million people are diagnosed with dementia – that is one person every 3 seconds3 . Currently, around 900,000 people in the UK have dementia.4 By 2050 this will be over 1.53 million. Globally over 50 million have dementia. By 2050 this is expected to increase to 152 million.5

Two in three people diagnosed with dementia will end up diagnosed with probable Alzheimer’s, while 17 per cent will be given a diagnosis of vascular dementia, caused by constricted blood flow to the brain due to blocked arteries, and 10% will be given a ‘mixed’ diagnosis, which is usually part Alzheimer’s, part vascular dementia. But the risk factors, and prevention treatments, for Alzheimer’s and vascular dementia are the same. So, combined, well over 80% of all dementia diagnoses should be preventable.

Brain regions

What is dementia?

There are other forms, such as dementia with Lewy bodies, fronto-temporal dementia and dementia caused by a stroke, a bleed in the brain or a brain tumour. But as Alzheimer’s is the most widespread, let’s look at it in depth.

Dementia – including Alzheimer’s – is an insidious condition. In the early stages, sufferers have increasing symptoms of absentmindedness, low mood and an inability to learn new things. Judgement, and their ability to function intellectually and socially, begin to go awry. The person may repeatedly forget to turn off the iron, or may not recall which medicines they took in the morning. They may start to show mild personality changes, such as a lack of spontaneity or a sense of apathy and a tendency to withdraw from social interactions.

Later on, there will be a loss of logic and memory, disorientation and poor coordination. Speech deteriorates and paranoia may appear. At this point, a diagnosis of probable Alzheimer’s disease may be given. Why ‘probable’? Because Alzheimer’s is properly diagnosed, not simply by symptoms, but by the presence of a specific kind of degeneration in a specific part of the brain – and this is difficult to see without the aid of expensive scans.

How was Alzheimer’s discovered?

The German neuropathologist Alois Alzheimer discovered this characteristic degeneration in the brain back in 1906. Using a technique known as silver stain, he examined the brain cells of a woman who died prematurely at 55 with signs of dementia, and found a tangled mess of proteins and clusters of degenerating nerve endings, called neurofibrillary tangles. This condition is associated with a gradual dying-off of neurons and poor communication between neurons. There is also often a build-up of something called beta-amyloid plaque, a protein-like substance that shouldn’t be there.

Since that time, research into Alzheimer’s has continued apace. Largely thanks to the pioneering work of Professor David Smith and colleagues in the University of Oxford’s pharmacology department, we now know that Alzheimer’s is a specific disease process, not just a random, gradual decline in brain cells, and that it originates in a particular brain region. Their Optima (Oxford Project to Investigate Memory and Ageing) study has been running since 1988 and has proved, among other things, that the damage leading to Alzheimer’s begins in a central part of the brain known as the medial temporal lobe.6-7

Pinpointing the problem area

The medial temporal lobe is vital for both mood and memory. Even though this lobe accounts for only 2 per cent of the brain’s total area, it is essential for the processing of everything we sense, feel or think.

Precisely because it’s in the middle of the head, it’s a difficult region to scan. This is also where there are more neurofibrillary tangles and beta-amyloid plaques – the hallmarks of Alzheimer’s. These indicate damage and chaos to the normal network of neurons and their connections.

Since information is passed from and to the medial temporal lobe from other parts of the brain, as this area becomes more damaged, fewer signals are sent to other parts of the brain. These then also start to decline, becoming more and more disconnected, with ever-decreasing blood flow. The beginning of damage is estimated to occur as early as 40 years before a person is diagnosed with dementia. That is why it is important to start your prevention plan young.

So far we’ve talked about the spread of damage seen in Alzheimer’s, starting with the medial temporal lobe, and radiating out to other areas of the brain, which are in effect starved of signals, much as a muscle atrophies through lack of use. Other indicators of Alzheimer’s are neurofibrillary tangles (p’tau), the lack of blood flow in the brain, and the presence of beta-amyloid plaques. There is also the presence of high levels of homocysteine in the blood.

Exactly which of these factors ‘causes’ Alzheimer’s, or kickstarts the process of damage, is the subject of much debate and ongoing research.

Clues to curbing the epidemic

Omega 3 fish oil soft gels

At the other end of the spectrum, scientists have been looking for ways to prevent Alzheimer’s disease, and are conducting more and more studies revealing the specific dietary and lifestyle factors that greatly increase or decrease risk. Around half of the risk can be prevented.8For example, having a high intake of omega-3 fats and B vitamins appears to reduce risk, while consuming a lot of sugar increases the risk. The National Institutes of Health attributes 22% of Alzheimer’s to high homocysteine and 22% to low omega-3/seafood consumption.9 What’s more people with pre-dementia with good omega-3 status, given extra B vitamins have a 73% less brain shrinkage than those on placebo.10

Somewhere in the middle, scientists are discovering how changes in diet could cause changes in the brain. An example of this is the discovery of an enzyme that both regulates insulin – the key hormone for keeping your blood sugar in balance – and beta-amyloid.  There are, however, many other ways, and growing evidence, that sugar and high carb diet driven by eating junk food damages the brain.

The most exciting discovery is the role of B vitamins and how too little can lead to increases in homocysteine in the blood. Since neither beta-amyloid nor those neurofibrillary tangles can be measured before its too late, the discovery that levels of a simple chemical in your blood could be the best predictor of all is the most welcome news – and it should, in our opinion, have revolutionised the early diagnosis and preventative treatment of those most likely to develop Alzheimer’s. There is good evidence that homocysteine, a measure of faulty methylation, is a primary driver of Alzheimer’s for a number of reasons:

  • Giving people with raised homocysteine and pre-dementia (mild cognitive impairment or MCI) extra homocysteine lowering B vitamins has been shown to reduce the rate of shrinkage of the medial temporal regions by nine fold.
  • Amyloid blocking drugs have little to marginal effects on the actual disease. A meta-analysis of these drugs that did effectively lower amyloid found virtual no significant cognitive benefit from doing so.11 Measures of Clinical Dementia Ratings show that both homocysteine-lowering B vitamins and Omega-3 fish oil supplements surpass anti-amyloid drugs. (See our newsletter)
  • The formation of neurofibrillary tangles, associated with p-tau proteins, could be a consequence of faulty methylation (eg raised homocysteine). When p-tau is high so is homocysteine. There are three known ways whereby raised homocysteine would raise p-tau.
  • Homocysteine is found in the regions of brain damage and is capable itself of causing brain damage.
  • A raised homocysteine increases the risk of cerebral vascular dysfunction by a remarkable 17 times.11
  • Every study that has effectively lowered homocysteine in people at risk, eg with MCI or mild Alzheimer’s, has shown benefit, except in the later stages of the disease which may just be too late.

An International Consensus Statement in 2018 concluded that moderately raised plasma total homocysteine (>11mcmol/L), found in half of those over age 70 12, is a main cause of age-related cognitive decline and dementia.13 Two major meta-analyses of hundreds of studies conclude that raised homocysteine is one of the best evidenced risk factors for AD and accounts for around a fifth of all risk 14, 15.

The key to prevention is to understand the contributing factors and to do something about them as soon as possible. Right now, because the thought of Alzheimer’s is so terrifying, most people avoid even seeing their doctor and are usually diagnosed only in the late stages, usually reported by a relative who has found their partner becoming unmanageable. That’s why it is critical to look for the earliest possible signs of cognitive decline, then there’s time to reverse the trend.

The Cognitive Function Test

The Food for the Brain Foundation offer an excellent free online Cognitive Function test and a simple Dementia Risk Index questionnaire which also works out your risk factors and which simple changes will have the most effect. Do please do this yourself and encourage everyone you know over 50 to do the test as well. Prevention, in this case, is the only likely ‘cure’ for this terrible disease.

For more on Alzheimer’s see our article on Preventing Alzheimer’s Disease


Help support Food for the Brain

Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.


References

  1. Rowe J., Kahn R., ‘Human ageing: usual and successful’, Science, 237 (4811): 143-9 (1987).
  2.  Bekris, L et al., ‘Genetics of Alzheimer disease’ Journal of Geriatric Psychiatry and Neurology 2010, 23(4) 213-227).
  3. Smith A.D., ‘Homocysteine, B vitamins and cognitive deficit in the elderly’, American Journal of Clinical Nutrition, 75:785-6 (2002).
  4. World Alzheimer Report. (2018). Available online at: https://www.alzint.org/resource/world-alzheimer-report-2018
  5. Bradley K.M. et al., ‘Cerebral perfusion SPET correlated with Braak pathological stage in Alzheimer’s disease’, Brain, 125:1772-81 (2002); see alsp Jobst K.A. et al., ‘Detection in life of confirmed Alzheimer’s disease using a simple measurement of medial temporal lobe atrophy by computed tomography’, Lancet, 340:1179-83 (1992).
  6. Jobst K.A. et al., ‘Association of atrophy of the medial temporal lobe with reduced blood flow in the posterior parietotemporal cortex in patients with a clinical and pathological diagnosis of Alzheimer’s disease’, J Neurol  Neurosurg Psychiat, 55:190-4 (1992); see also Jobst K.A. et al., ‘Rapidly progressing atrophy of medial temporal lobe in Alzheimer’s disease’, Lancet, 343:829-30 (1994).
  7. Smith,D., Jaffe,K. ‘Dementia (Including Alzheimer’s Disease)can be Prevented: Statement Supported by International Experts’ Journal of Alzheimer’s Disease 38 (2014) 699–703
  8. M. Beydoun et al, ‘Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis BMC Public Health 2014, 14:64 [http://www.biomedcentral.com/1471-2458/14/643]
  9. Jernerén F, Elshorbagy AK, Oulhaj A, Smith SM, Refsum H, Smith AD. Brain atrophy in cognitively impaired elderly: the importance of long-chain ω-3 fatty acids and B vitamin status in a randomized controlled trial. American Journal of Clinical Nutrition. 2015;102:215-21.
  10. Teng Z, Feng J, Liu R, Ji Y, Xu J, Jiang X, Chen H, Dong Y, Meng N, Xiao Y, Xie X, Lv P. Cerebral small vessel disease mediates the association between homocysteine and cognitive function. Front Aging Neurosci. 2022 Jul 15;14:868777. doi: 10.3389/fnagi.2022.868777. PMID: 35912072; PMCID: PMC9335204.
  11. Smith AD Effect of reductions in amyloid levels on cognitive change in randomized trials: instrumental variable meta-analysis BMJ 2021;372:n156
  12. Smith AD, Smith SM, de Jager CA, Whitbread P, Johnston C, Agacinski G, et al. Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment. A randomized controlled trial. PLoS ONE. 2010; 5: e12244.
  13. Smith AD, Refsum H, Bottiglieri T, Fenech M, Hooshmand B, McCaddon A, et al. Homocysteine and dementia: An international consensus statement. J Alzheimers Dis. 2018; 62: 561-70
  14. Beydoun MA, Beydoun HA, Gamaldo AA, Teel A, Zonderman AB, Wang Y. Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 2014; 14: 643.
  15. Yu JT, Xu W, Tan CC, Andrieu S, Suckling J, Evangelou E, et al. Evidence-based prevention of Alzheimer’s disease: systematic review and meta-analysis of 243 observational prospective studies and 153 randomised controlled trials. J Neurol Neurosurg Psychiatry. 2020; 91: 1201-9
Further info

New evidence on how 4 simple changes can halve your risk of dementia shared at international conference

By Patrick Holford

A global conference of leading world experts in dementia prevention has today identified four easy ways that could reduce risk of dementia by half and eight that could cut your risk by two thirds. 

The research was shared, for the first time, at the Alzheimer’s Prevention Conference, organised by the charitable foundation Food for the Brain. 


The new research showed that there are four easy ways to cut your risk of dementia in half:

1. Supplementing omega-3 fish oils

According to a new study of almost half a million participants of the UK’s Biobank supplementing fish oils cuts dementia risk.[i] This new research was presented at the conference by China’s leading dementia prevention expert from Shanghai’s Fudan University, Professor Jin-Tai Yu, “Our current research, using data from the UK Bio Bank, shows that having a higher blood levels of omega-3, and supplementing fish oils, is associated with less risk of dementia.”

Other studies reported by Dr Simon Dyall, clinical neuroscientist at the University of Roehampton, showed that a higher intake of fish was associated with cutting risk of Alzheimer’s disease by a third.[ii] “Half your brain is fat, and a type of omega- 3 called DHA has a very important role in the communication between brain cells.” said Dyall.


2. B Vitamins

According to Professor Yu, another very promising prevention treatment is B vitamins.[i] “Lowering blood homocysteine levels, an established indicator of Alzheimer’s risk, with B vitamins is a most promising treatment.” Raised homocysteine is found in one in two people over 70.

In a trial at Oxford University by Professor David Smith, who was presenting at the conference, giving high dose B vitamins versus placebos, resulted in 52% less brain shrinkage and little further memory loss.[ii]

Combining omega-3 and vitamin B. The discovery of the synergistic role of omega-3 led the Oxford Professor to reanalyse blood samples taken at the start of the trial for omega-3. They found that those with low omega-3 DHA blood levels, one of the main nutrients found in fish and fish oil supplements, had no benefit from the B vitamins, while those with high omega-3 DHA had 73% less shrinkage and almost nine times less shrinkage of the Alzheimer’s related areas of the brain.[iii]

Furthermore, another study in Sweden, that had given omega-3 fish oil supplements, reanalysed their results and found those with good B vitamin status substantially reduced their dementia risk.[iv]

A third study in the US, called ‘B proof’, that had given B vitamins with marginal improvements, reanalysed their results and found that those with higher omega-3 levels also had a much greater improvement.[i]

“Research shows that you get impressive results if you give omega-3 and B vitamins together rather than on their own.” Says Professor Smith. 

While US National Institutes of Health researchers attributed 22% to lack of seafood or omega-3 and another 22% to the B vitamin factor they also attributed 32% of risk to inactive lifestyle.[ii]


3. Exercise

“For many people the worst thing they can do for their brain is to retire”

Keeping your brain active. Another expert at the conference, Tommy Wood, Assistant Professor at the University of Washington, showed that your muscle mass predicts brain volume. “Exercise, especially resistance exercise, is important because it makes the brain do things that keep it healthy, such as growth and repair.” he says. “When they aren’t stimulated, the health of brain tissues deteriorates, with a knock-on effect on memory and thinking.”

And it’s not just physical exercise that does this, we also benefit from the mental exercise involved in activities like solving puzzles or learning a new language. “For many people the worst thing they can do for their brain is to retire”, says Wood. “They lose much of the stimulation that kept it healthy.” 


4. Sugar

“Sugar levels at age 35 predict Alzheimer’s risk later in life”

While it has long been known that diabetics have a much higher risk for dementia, a recent study at Boston University School of Medicine, found that higher blood sugar levels at age 35, but still in the ‘normal’ non-diabetic range, predict Alzheimer’s later in life.[i] Talking at the conference Professor Robert Lustig, from the University of California, said, ”A high level of sugar and insulin in the blood – linked with a high carbohydrate diet – is definitely a driver for Alzheimer’s.” 

The conference, hosted by the UK charity foodforthebrain.org, identified eight domains of risk, in other words, four more actions you can take to reduce your risk of dementia: eating antioxidants from fruit and veg; having a healthy gut; sleeping well; and controlling stress. 


Targeting all eight risk factors earlier in life may reduce risk by two thirds. 

But how do you know what your risk is and what and how to change to reduce your risk? That’s what the charity, the Food for the Brain Foundation has been working on for a decade. On their website, foodforthebrain.org, you can do a free Cognitive Function Test. Almost 380,000 people have taken the test and, according to research by NHS and University College London researchers, 88% find it useful. You then complete a questionnaire that works out your future dementia risk index. It also tells you exactly what’s driving your risk up and what to do about it. By downloading the COGNITION app you can tack your progress, get advice on how to reduce your risk further, and get support to help you dementia-proof your diet and lifestyle.

Do the test now and reduce your risk!


Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research bybecoming a Friend of Food for the Brain.


References:

[1] Yu JT et al, Circulating polyunsaturated fatty acids, fish oil supplementation, and risk of incident dementia: a prospective cohort study of 440,750 participants, BMC medicine (pending publication)

[2] Wu S, Ding Y, Wu F, Li R, Hou J, Mao P. Omega-3 fatty acids intake and risks of dementia and Alzheimer’s disease: a meta-analysis. Neurosci Biobehav Rev. 2015 Jan;48:1-9. doi: 10.1016/j.neubiorev.2014.11.008. Epub 2014 Nov 21. PMID: 25446949.

[3] Yu JT, Xu W, Tan CC, Andrieu S, Suckling J, Evangelou E, Pan A, Zhang C, Jia J, Feng L, Kua EH, Wang YJ, Wang HF, Tan MS, Li JQ, Hou XH, Wan Y, Tan L, Mok V, Tan L, Dong Q, Touchon J, Gauthier S, Aisen PS, Vellas B. Evidence-based prevention of Alzheimer’s disease: systematic review and meta-analysis of 243 observational prospective studies and 153 randomised controlled trials. J Neurol Neurosurg Psychiatry. 2020 Nov;91(11):1201-1209. doi: 10.1136/jnnp-2019-321913. Epub 2020 Jul 20. PMID: 32690803; PMCID: PMC7569385.

[6] Jernerén F, Cederholm T, Refsum H, Smith AD, Turner C, Palmblad J, Eriksdotter M, Hjorth E, Faxen-Irving G, Wahlund LO, Schultzberg M, Basun H, Freund-Levi Y. Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. J Alzheimers Dis. 2019;69(1):189-197. doi: 10.3233/JAD-181148. PMID: 30958356.

[7] van Soest, A.P.M., van de Rest, O., Witkamp, R.F. et al. DHA status influences effects of B-vitamin supplementation on cognitive ageing: a post-hoc analysis of the B-proof trial. Eur J Nutr (2022). https://doi.org/10.1007/s00394-022-02924-w

[8] Beydoun MA, Beydoun HA, Gamaldo AA, Teel A, Zonderman AB, Wang Y. Epidemiologic studies of modifiable factors associated with cognition and dementia: systematic review and meta-analysis. BMC Public Health. 2014 Jun 24;14:643. doi: 10.1186/1471-2458-14-643. PMID: 24962204; PMCID: PMC4099157.

[9] Zhang X, Tong T, Chang A, Ang TFA, Tao Q, Auerbach S, Devine S, Qiu WQ, Mez J, Massaro J, Lunetta KL, Au R, Farrer LA. Midlife lipid and glucose levels are associated with Alzheimer’s disease. Alzheimers Dement. 2022 . doi: 10.1002/alz.12641. Epub ahead of print. PMID: 35319157.

Further info

Alzheimer’s: Why prevention is better than drugs – but less profitable

By Patrick Holford

After 40 failed trials for drugs injecting anti-amyloid antibodies (AAAs) one, Lecanemab[i], has finally shown a modest benefit on cognitive function in those with early-stage Alzheimer’s. But they come with a terrible cost – adverse effects that include brain swelling and haemorrage which occurred in one in five trial participants.. When a similar drug, Aducanumab, was conditionally approved by the US FDA last year, despite nine out of ten of their experts voting against it, many resigned in protest[ii]. Yet the pressure on pharma to get an amyloid drug to market, having spent over $42 billion[iii], is immense.


Let’s consider the alternative 

Prevention with simple, doable changes to diet, lifestyle and supplementation with B vitamins and omega-3 fish oils.

The two most relevant measures of success of any treatment are reduction in the rate of brain shrinkage and a reduction in clinical dementia symptoms which lead to a diagnosis.

In relation to brain shrinkage the best AAAs have achieved is 2% less brain shrinkage. In a landmark trial by Professor David Smith and colleagues at the University of Oxford, B vitamin supplements, given to those with pre-dementia (mild cognitive impairment) have achieved a reduction in the rate of brain shrinkage of 52%, up to 73% in those with sufficient omega-3.[i] This effect was shown in those with raised blood levels of homocysteine, a marker for B vitamin status that is raised in approximately half of pre-dementia patients and many more with Alzheimer’s. We now know that B vitamins need omega-3 to make the biggest difference, and vice versa.[ii]

Chart, waterfall chart

Description automatically generated

Clinical Dementia Rating (CDR) with B vitamins and Omega 3’s

What about actual clinical improvement, called Clinical Dementia Rating (CDR), which is what counts for the person concerned? A CDR score of zero means no clinically significant cognitive impairment. In the Oxford trial on B vitamins  65% of participants on B vitamins with higher omega-DHA status ended the 2 year trial with a clinical dementia rating of zero compared with 25% receiving placebo.[i] It was more than twice as effective as the recent drug. In a Swedish omega-3 trial those with sufficient B vitamin status, also had a marked reduction in clinical dementia rating, which was reduced by 1.5 points compared with placebo after 6 month’s treatment with omega-3.[ii] The improvement in clinical dementia rating reported for Lecanemab, which was a modest 0.45 point reduction. This was marginally better than a 0.39 difference for Aducanumab, compared to placebo.[iii] [iv] In other words, no AAA drug has even reduced  a CDR score by 1 point but both B vitamins and omega-3 have.

Chart, waterfall chart

Description automatically generated

A trial in Holland, called B-proof, which had shown no significant effects overall in those supplementing B vitamins, recently reported that those with higher Omega-3 levels had a significant improvement in cognitive function. A French[i] and Chinese study[ii] reported a similar finding – the combination of B vitamins and omega-3 shows clear improvements in cognitive function – better than achieved by AAA drugs, without adverse effects.

So, on all three counts – brain shrinkage, cognitive function and clinical dementia rating – B vitamins plus omega-3 – wins out at a fraction of the cost since nutrients cannot be patented which is the requirement for the scale of profitability required by pharma.


Blood Sugar Levels and their impact

But, there’s two other points to make. Firstly, B vitamin and omega-3 status are but two of eight known actions that reduce risk or improve these critical criteria. Others are sugar, antioxidant rich fruit and veg, vitamin D, exercise, cognitive stimulation, gut health, sleep and stress.[i] Having a high blood sugar level from age 35 predicts Alzheimer’s risk.[ii] Being diabetic or having high insulin levels, which is a consequence of eating too many refined sugar and carbs, doubles risk.[iii] Having a high carb intake is associated with increasing amyloid plaques in the brain – so why not tackle the upstream cause? One study reported that “Those who ate the healthiest diet had an 88% decreased risk of developing dementia and a 92% decreased risk of developing Alzheimer’s disease.”[iv] Increasing lean muscle mass with resistance exercise is associated with better cognitive function and brain volume.[v] The charity foodforthebrain.org have a free, validated online Cognitive Function Test, followed by a Dementia Risk Index questionnaire, that not only measures your cognitive function, but also shows you exactly what your risk is and how to reduce it by targeting your ‘weakest links’ in these eight known prevention steps.

Then, there’s the issue of side-effects. For each of these prevention steps there are none. Or rather, there are plenty – less risk for diabetes, heart disease, arthritis, premature ageing, better energy, sleep and weight control to name a few.

For the AAA drugs the side-effects are potentially devasting. Since one in five can be expected to experience brain swelling and microbleeds, regular brain scans will be necessary to monitor for these frequent complications. Is it right to expose an older person with cognitive decline to this scale of risk and medical intervention for such a modest benefit? The annual cost of treatment is expected to be above $10,000 but that doesn’t include the cost of medical monitoring or the cost of treatment when things go wrong. The cost benefit equation just doesn’t add up.


Early Intervention

Writing in the Financial Times last year Professor Smith says “ Your editorial is correct in saying ‘A resurrection of the amyloid approach must not divert resources and attention away from other ways to tackle dementia, which are in earlier stages of research and might give better results.’ These alternative approaches include identifying and then treating modifiable risk factors for dementia, of which about a dozen are already known. These account for about half of the cases of Alzheimer’s disease .” The high price proposed for the drug is disturbing, especially when a very much cheaper alternative treatment is available: high-doses of B vitamins and omega-3 from seafood or supplements. He estimates that early intervention , targeting all the prevention steps recommended by the Food for the Brain Foundation could cut a person’s risk by two thirds. 

For more details on Alzheimer’s prevention visit: https://brainhealthcheck.foodforthebrain.org/preventing-alzheimers-disease/

Alzheimer’s Is Preventable – LEARN more now

WE currently have 2 events on sale so that you can take a deep dive on this topic:
⭐️ MASTERCLASS – 4 hour conference with world leading experts on Alzheimer’s – Practitioner level. Book tickets here: https://brainhealthcheck.foodforthebrain.org/aipmasterclass/


🧠 Upgrade Your Brain – 8 steps to reduce your Alzheimer’s risk with with Patrick Holford – A condensed version of the masterclass that is 90 minutes long and aimed at the general public. Book your tickets here: https://www.eventbrite.co.uk/e/upgrade-your-brain-tickets-415953948457

Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.


References:

[1] Oulhaj A, Jernerén F, Refsum H, Smith AD, de Jager CA. Omega-3 Fatty Acid Status Enhances the Prevention of Cognitive Decline by B Vitamins in Mild Cognitive Impairment. J Alzheimers Dis. 2016;50(2):547-57. doi: 10.3233/JAD-150777. PMID: 26757190; PMCID: PMC4927899.

[2]  Jernerén F, Cederholm T, Refsum H, Smith AD, Turner C, Palmblad J, Eriksdotter M, Hjorth E, Faxen-Irving G, Wahlund LO, Schultzberg M, Basun H, Freund-Levi Y. Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. J Alzheimers Dis. 2019;69(1):189-197. doi: 10.3233/JAD-181148. PMID: 30958356.

[3] Cummings JL, Goldman DP, Simmons-Stern NR, Ponton E. The costs of developing treatments for Alzheimer’s disease: A retrospective exploration. Alzheimers Dement. 2022 Mar;18(3):469-477. doi: 10.1002/alz.12450. Epub 2021 Sep 28. PMID: 34581499; PMCID: PMC8940715.

[6] Oulhaj A, Jernerén F, Refsum H, Smith AD, de Jager CA. Omega-3 Fatty Acid Status Enhances the Prevention of Cognitive Decline by B Vitamins in Mild Cognitive Impairment. J Alzheimers Dis. 2016;50(2):547-57. doi: 10.3233/JAD-150777. PMID: 26757190; PMCID: PMC4927899.

[7] Jernerén F, Cederholm T, Refsum H, Smith AD, Turner C, Palmblad J, Eriksdotter M, Hjorth E, Faxen-Irving G, Wahlund LO, Schultzberg M, Basun H, Freund-Levi Y. Homocysteine Status Modifies the Treatment Effect of Omega-3 Fatty Acids on Cognition in a Randomized Clinical Trial in Mild to Moderate Alzheimer’s Disease: The OmegAD Study. J Alzheimers Dis. 2019;69(1):189-197. doi: 10.3233/JAD-181148. PMID: 30958356.

[9] Awaiting actual Lecanemab, trial – see press release ref 1 above

[10] Maltais M, de Souto Barreto P, Bowman GL, Smith AD, Cantet C, Andrieu S, Rolland Y. Omega-3 Supplementation for the Prevention of Cognitive Decline in Older Adults: Does It Depend on Homocysteine Levels? J Nutr Health Aging. 2022;26(6):615-620. doi: 10.1007/s12603-022-1809-5. PMID: 35718871.

[11] Li M, Li W, Gao Y, Chen Y, Bai D, Weng J, Du Y, Ma F, Wang X, Liu H, Huang G. Effect of folic acid combined with docosahexaenoic acid intervention on mild cognitive impairment in elderly: a randomized double-blind, placebo-controlled trial. Eur J Nutr. 2021 Jun;60(4):1795-1808. doi: 10.1007/s00394-020-02373-3. Epub 2020 Aug 28. PMID: 32856190.

[13] Zhang X, Tong T, Chang A, Ang TFA, Tao Q, Auerbach S, Devine S, Qiu WQ, Mez J, Massaro J, Lunetta KL, Au R, Farrer LA. Midlife lipid and glucose levels are associated with Alzheimer’s disease. Alzheimers Dement. 2022 Mar 23. doi: 10.1002/alz.12641. Epub ahead of print. PMID: 35319157.

[15] Eskelinen MH, Ngandu T, Tuomilehto J, Soininen H, Kivipelto M. Midlife healthy-diet index and late-life dementia and Alzheimer’s disease. Dement Geriatr Cogn Dis Extra. 2011 Jan;1(1):103-12. doi: 10.1159/000327518. Epub 2011 Apr 27. PMID: 22163237; PMCID: PMC3199886.

Further info

How We Became Sapiens?

By Patrick Holford

What makes us humans so different to other apes is our larger brain, especially the cortex. It is three times larger than a chimpanzee. How did this happen? How did Homo Sapiens evolve our level of intelligence despite sharing almost the same genes? 

The brain’s origin, for all species, is from the ocean. It had to be as that is where life began. Millions of years ago the rudimentary eye cell, dinoflagellate, which is a type or marine phytoplankton, used a specific fat – the omega-3 fat docosahexanoic acid (DHA) – to convert solar photon energy into the first nerve impulse or twitch – a twitch towards food. That is the origin of the nervous system and brain.

Back in the ‘80’s, when zoologist Professor Michael Crawford analysed the types of fat in different animal’s organs and muscles they varied according to their dietary environment, except the brain. He discovered that the brain is always rich in DHA. The more DHA the brighter the animal, with the sea mammals and us humans having exceptionally high levels.

Recently it has been proven that DHA (docosahexanoic acid) has a unique structure involving six double bonds, arranged in a horseshoe shape, which actually makes it a semi-conductor with unique electrical properties. Its close cousins, ALA (alpha linolenic acid) in chia or flax, and EPA (eicosapentanoic acid) don’t have this potential. It’s all about DHA. While some EPA converts into DHA less than 1 per cent of ALA in plant-based sources of omega-3 such as chia seeds converts to DHA, the richest source of which is marine-based food from rivers and the sea.

Over 6 million years ago our hominid ancestors split from other apes (chimps, gorillas and bonobos), culminating in Homo Sapiens around 100,000 years ago. It clearly wasn’t genes that made us different. We share 98.5% of the same genome. It had to be the environment our ancestors exploited. During this time brain size steadily increased up to 1.45kg 10,000 years ago, roughly three times the size of a chimpanzee, at 384g.

Homo Aquaticus

We have over twenty profound anatomical, physiological and biochemical differences apart from our vastly different psychological advancement as in intelligence and language. More than anything, it is this, illustrated by our brain size, that makes us different. But, before looking closely at the circumstances, and diet, that almost certainly drove our gain in brain size and intelligence, let’s take a look at the fundamental differences we have. These have been so clearly delineated in an excellent book, The Waterside Ape, by Peter Rhys-Evans, and ear, nose and throat surgeon. He explores why we:

  • Stand upright
  • Have (virtually) no body hair
  • Have a layer of sub-cutaneous fat
  • A waxy, waterproof layer, the vernix, at birth
  • A diving reflex at birth, meaning we are able to swim before we can walk, and hold our breath underwater
  • A descended larynx, a precursor of being able to have complex language/speaking
  • Enlarged sinus cavities
  • A nose shape that is good for keeping the water out while swimming
  • Ears that actually form a protective boney protusion in those who spend a lot of time diving
  • Different kidneys, in how they filter salt and water 
  • Manual dexterity
  • Crinkly fingers when in water for a few minutes

Of course, the story we’ve all been told is that we came out of the trees, into the savannah and stood upright for better hunting. Anyone who has been on safari will know that a) you don’t stand a chance catching anything by standing upright – you crawl; and b) all the good hunters can sprint much faster than man (lion 80kph, leopard 60kph, cheetah 100kph, man under 30kph) precisely because four legs are better than two. But, can you explain any one of these other changes, let alone our increase in intelligence, by moving from the trees into the savannah for hunting? If so, how did we suddenly develop manual dexterity, tools and spears overnight to even survive? Also, why do certain ‘sea nomad’ tribes exist, such as the Moken and Bajou, who can hold their breath for up to 10 minutes under water, spending up to five hours a day in the sea, giving birth in the sea? Their spleen is adapted to oxygenate tissue, as it is in dolphins, to enable long dives. Where did that evolutionary adaptation come from?

The only logical explanation that I have encountered, which eloquently fits all these adaptations, in that our hominid ancestors exploited the waterside – wetlands, swamplands, rivers, estuaries and coasts. In the process of so doing, became upright, and started to eat a diet high in marine foods, providing the essential nutrients for brain development, that is omega-3 DHA, phospholipids, plus vitamin B12, iodine, and all those other essential elements from magnesium to selenium. From this perspective let’s briefly examine all the changes listed above, between us and other apes:

  • Stand upright – better for wading in water, so gradually our anatomy adapts but, even so, we are prone to the problems of uprightness, eg hips and knees because it is  anatomically inferior to walk on all fours, with better weight distribution.
  • Have (virtually) no body hair and a layer of sub-cutaneous fat – consistent with semi-aquatic mammals better for floating and insulation
  • A waxy, waterproof layer, the vernix, at birth – found in no land mammals, only other semi-aquatic mammals such as seals and chemically identical
  • A diving reflex at birth, meaning we are able to swim before we can walk, and hold our breath underwater
  • A descended larynx, a precursor of being able to have complex language/speaking – being upright, and diving, could have led to this vital adaptation. This, by the way, only occurs after a year or so, before which a baby’s language cannot develop the complexity of sounds and voice control only we have
  • Enlarged sinus cavities, which help to keep the head above water, but still have drainage holes in the ‘wrong’ place, eg good if on all fours but bad if upright, which is why we are prone to sinus problems.
  • A nose shape that is good for keeping the water out while swimming
  • Ears that actually form a protective boney protusion in those who spend a lot of time diving
  • Manual dexterity – if we were wading, and swimming, not walking on all fours, we have ‘free’ hands. Opening shells would develop manual dexterity.
  • Crinkly fingers when in water for a few minutes – perfect for catching fish.

Part of the idea of the ‘savannah’ theory is that food became scarce with climate changes so we switched to hunting. But the water’s edge was, until recently, abundant with easily accessible food. Even 200 years ago, in 1706, Daniel Dafoe wrote this regarding the Firth of Forth. “Off the Pentland Firth the sea was one third water and two thirds fish; the operation of taking them could hardly be call’d fishing, for they did little more than dip for them into the water and take them up.” Our estuaries were packed with mussels, oysters and crabs.

Historically, wherever early man is found so too is evidence of seafood consumption, with remains of shells, fish bones etc. from Pinnacle Point in South Africa, where early remains are found together with sea shells, to Wales. When a 40,000 year old Homo sapiens was found in the Gower peninsular DNA evidence showed that a quarter of their diet was seafood.

A marine food diet high in critical brain building nutrients, especially DHA, phospholipids and B12, is the best explanation for our cerebral expansion. “Docosahexaenoic acid (DHA), the omega-3 fatty acid that is found in large amounts in seafood, boosts brain growth in mammals. That is why a dolphin has a much bigger brain than a zebra, though they have roughly the same body sizes. The dolphin has a diet rich in DHA. The crucial point is that without a high DHA diet from seafood we could not have developed our big brains. We got smart from eating fish and living in water.” says Crawford.

The dry weight of the brain in 60 per cent fat and DHA makes up over 90 per cent of the structural fat of neurons (brain and nerve cells). The intelligent membrane that makes up all neurons is composed of phosphorylated DHA – that is DHA attached to phospholipids. The most abundant phospholipid is phosphatidyl choline, found predominantly in fish, eggs and organ meats. These are bound together by a process called methylation, itself dependent on vitamins B12, folate and B6. While folate and B6 is found in both plant foods and seafood, B12 is only found in foods of animal origin, and is especially high in all marine foods.

The evidence that exists suggests we were eating a diet rich in marine food, as well as  plant foods along the water’s edge, enjoying the ‘fruité del mare’. We would have eaten much more than we do today – at least double the calories. Today’s convenience world has dramatically reduced the calories we need to expend hunting and gathering food, travelling and staying warm.

The idea that we were eating twice as much and at least a quarter from marine foods makes sense of what we know about the optimal intake of both omega-3 fats rich in DHA, phospholipids and vitamin B12, lack of which are the main drivers of today’s endemic dementia. This would be equivalent to at least half our diet today needing to be from marine foods rich in fats.

Optimal amounts of omega-3 from seafood is estimated at 2 grams a day by Joseph Hibbeln at the US National Institute’s of Health, while choline is estimated at 400mg to 800mg. An optimal intake of B12 is probably 10mcg. None of these can easily be achieved even by eating seven servings of oily fish a day. (Choline is rich in all fish, but DHA is only rich in oily fish, fish roe and liver.)

In the chart below the last column combines EPA and DHA and shows the amount provided in an 85g serving. None provide 2,000mg, although they do get close, suggesting that we would have needed to eat at least a serving of fish or seafood a day, if not more. 

Fish and Seafood (per 85g)EPAmg DHAmgEPA+DHAmg
Atlantic Salmon (farmed) 58712381825
Atlantic Herring 7739391712
Atlantic Salmon (wild) 34912151564
Bluefin Tuna 3099701279
Mackerel (canned) 3696771046
Sockeye Salmon (wild) 4515951046
Rainbow Trout (farmed) 284697981
Sardines (canned) 402433835
Albacore (or white) Tuna (canned) 198535733
Shark (raw) 267444711
Swordfish 117579696
Sea Bass 175473648
Pollock 77383460
Flat Fish (Flounder/Sole) 207219426
Halibut 77318395
Oysters (farmed) 195179374
Dungeness Crab 23996335
Scallops 141169310
Mixed Shrimp 145122267
Clams 117124241
Yellowfin Tuna 40197237
Catfish (wild) 85116201
Catfish (farmed) 42109151
Cod 3131134
Mahi-Mahi (dolphin fish) 2296118
Tilapia 4111115

Brain size remains reasonably constant from 100,000 to 10,000 years ago, then starts to shrink, perhaps coinciding with the birth of agriculture and diets based more on meat, milk and plants than marine foods. Today, average brain size is 1.35kg. 

The evolution of intelligence and self-awareness

Apart from brain size and, more pertinently, brain to body size ratio, what sets us apart from other animals is self-awareness. Animals have the equivalent of thoughts and feelings but humans are relatively unique in being able to witness one’s own thoughts and feelings, that is self- awareness. This is not an easy thing to measure, but some other mammals, notably dolphins, gorillas and chimpanzees, also have a degree of self-awareness. Other contenders for higher cognition include octopuses and elephants, all large brained creatures. However, it isn’t just size that counts. In essence, there are three evolutions of the brain. First, the reptilian brain located on the brain stem, which programmes basic survival needs. Then there’s the mammalian brain, with more cognitive and emotive functions (think dog), then the neo-cortex, associated with higher cognition. But, while elephants have larger brains they have smaller neo-cortexes. It’s the neo-cortex that starts to grow in our hominid ancestors.

An indication of an advancing intelligence could be supposed from the earliest evidence of ancient rock art, as well as use of complex tools and adornments.  The earliest rock art is found in South Africa, dating back 77,000 years ago, and in Western Europe about 37,000 years ago, and possibly in Australasia (Sulawesi) around that time.

The richest concentration of ancient rock art over 6,000 years ago, however, is found in sub-Saharan Africa, the Nile Valley and Red Sea hills, then a green belt with vast lakes, rivers and wetlands, hence abundant marine foods, which lasted until about 3,500 years ago when much of Egypt is becoming a desert. Whether the drying up of the Sahara was linked to the Younger Dryas (see below), a change in the Earth’s tilt or over grazing is a subject of debate.[i]

Meanwhile, groups of our early ancestors who had left Africa, living in Europe as far west as Ireland, north as Scandinavia, East as China and Australia, were also struck by cataclysmic weather changes. In Europe the Magdalenian culture, with advanced stonework, exists from 17,000 years ago, coinciding with the end of the Ice Age, until 12,000 years ago, coinciding with the Younger Dryas, a period of extreme cooling which lasted for circa 1,000 years, possibly triggered by a meteor shower[i]. One theory has ancestors migrating south, towards warmer climates with available water, possibly carrying with them the sticky grains they had previously gathered, and may have planted them in moist soil as a means to survive, thus giving birth to the agricultural age whereby mankind moves away from a hunter gatherer lifestyle towards an agricultural lifestyle. This also makes sense as these two pockets of humanity, in Mesopotamia (now Iraq), between the Tigris and Euphrates river, and Egypt, becoming more densely populated with the need for stored food, supplied by grains and domesticating animals. This stable food supply would have allowed expansion of these populations. (There is another evolutionary hotspot in Asia and China[i].)

Early Enlightenment

The likely existence of an ‘enlightened’ culture, Atlantis, is eluded to in the writings of Plato, possibly existing around the fertile region of the then much smaller Black Sea, which is thought to have flooded across the Bosphorus peninsular when the Mediterranean sea levels rose to a critical mass, dated back to around 7,000 years ago. This may also be the origin of the Flood myth, which occurs in ancient Sumerian lore dating back 5,000 years and later Hebrew lore.

Thus we have this triangle between the Black Sea to the North, Egypt to the South, and Mesopotamia to the East, all with evidence of evolved culture, including monotheism. The Sumerian culture appears over 6,000 years ago in the fertile crescent of Mesopotamia. Later, circa 2,500 years ago, we have the enlightened Zoroastra in Mesopotamia forming the Parsi culture in what is now Iran. Also,The Aryan-(Dru)Vedic culture, sometimes located east of the Black sea, migrated into the Indus valley in northern India as the main influence of the now Hindu culture, and the start of the Greek culture, considered to be the origin of our Western culture. The earliest hint of a Druidic culture dates back to this time. One stream of ancient druidic lore talks of a cataclysmic event, stones pouring from the sky, raising the possibility that early stone structures and barrows were built effectively as ‘bomb shelters’.[i] While the meaning of the word ‘dru’ is associated with oak (those who meet by the oak) and truth, it also may also mean worshippers of the red Sun (du rua). Sun and fire worship is shared by the early Egyptians (Ra), (dru)vedic culture (Agni and Surya), Zoroastrian culture(Mithra) and even Sumerian culture (Utu). The use of fire started much earlier, with it’s discovery a million years ago, and widespread use from 500,000 years ago, which expanded humanity’s ability to derive energy from previously indigestible carbohydrates, as evidenced in the DNA with the emergence of multiple variations in carbohydrate- digesting amylase enzymes. This is also linked to an expansion in brain size.[ii]

Is Homo Sapiens devolving?

Globally, there is an increase in mental illness which is fast becoming the biggest health threat, according to the World Health Organisation. There is also evidence that our brain size has reduced by 10 per cent, from 1.45kg 10,000 years ago[1] to an average now of 1.35kg, coinciding with a more land-based food supply. According to Scandinavian research, our IQ is also falling by 7 per cent a generation. Global rates of depression and dementia, suicide and stress-related disorders of anxiety and insomnia are escalating. One in six children in the UK are classified with ‘special educational needs’ (SEN). Suicide, globally, has become the most cause of violent deaths, ahead of all wars and murders. In the UK 790 people a day, nine double decker buses worth, are diagnosed with dementia. Global incidence will top 100 million this decade, already costing over 1% of GDP.

On the assumption that our brains still require at least the same supply of nutrients that our semi-aquatic ancestors were able to eat during the period of maximum brain evolution – although one could argue that the digital age has put more stress on our brain function, hence we might even need more nutrients – and the fact that we are simply not achieving anything like the same intake of the brain’s essential fats, phospholipids and micronutrients, is it any wonder that mental health is in sharp decline? With a growing population and declining available seafood, coupled with contamination with heavy metals, PCBs and micro-plastic particles, matters are likely to get much worse.

High sugar intake, in animals, has been shown to lead to shrinking of the brain’s hippocampal region. This is where the nucleus accumbens, the seat of the brain’s dopamine-based ‘reward’ system, stimulated by sugar, caffeine and tech addiction, (especially that based on variable rewards such as the ‘like’ button) resides. Marketeers have learnt how to create addiction to their products by stimulating the reward system, selling short-term pleasure, the dopamine-based feeling, in the guise of happiness. The happy hour, the happy meal, happiness in a bottle etc. Over-stimulation of the reward system ultimately leads to dopamine depletion and brain cell death, coupled with a decline in serotonin, the tryptamine associated with happiness, connection, love, empathy and other essential qualities of a harmonious society – and the very qualities that make us human.

We are therefore witnessing the devolution of the brain, the decline and fall of mental health and harmonious society, a situation that is likely to get worse as population expands, unless we rapidly find a way to optimally nourish the brain.

Building Healthy Brains

The emphasis in human nutrition has, for too long, been on the body. With more protein, meat and dairy products, we have grown taller, but not smarter. As director of the Institute of Brain Chemistry at the Chelsea and Westminster Hospital, Professor Michael Crawford has been able to accurate predict which pregnant women are most likely to have pre-term babies, with an increased risk of cognitive delay or impairment. This is based on determining the supply, by analysing the pregnant woman’s blood, of DHA. In its absence levels of a surrogate fat, oleic acid, rises to fulfil the requirement of the neonatal brain, when DHA is in short supply. It is, however, an inadequate substitute and thus cognitive development is impaired. Babies born of mothers with low blood DHA levels, compared to those supplementing DHA, have smaller brains.[2]

According to Crawford, with a growing population and shrinking fish supply, we must develop marine agriculture on a massive scale to survive and protect the brain. In the same way that man moved from hunter gatherer on the land to peasant farmer, we too must move from hunter gatherer in the oceans to marine farmer. In Japan he has been instrumental to the creation of artificial reefs in the estuaries to attract back the marine food web, from mussels to crustaceans, and fish, as well as farming seaweed on a massive scale. By processing seaweed it is possible to create DHA, the critical brain fat that is crucially lacking in a plant-based diet. As Crawford says “We now face a world in which sources of DHA – our fish stocks – are threatened. That has crucial consequences for our species. Without plentiful DHA, we face a future of increased mental illness and intellectual deterioration. We need to face up to that urgently.”

At the other end of the lifecycle, more and more older people are slipping into dementia, which is a preventable but not reversible condition. At the University of Oxford, Professor David Smith has shown that inadequate omega-3 fats (DHA and EPA) and B vitamins, especially vitamin B12, are the principle drivers of cognitive decline. Yet, by providing these nutrients to those with pre-dementia, further memory decline and brain shrinkage can be arrested. B12 is only found in animal foods and is especially rich in seafood. A plant-based diet alone does not provide sufficient DHA, B12 or phospholipids require for optimal brain development.

Therefore, it is vital that the needs for optimal brain function are put at the top of the health agenda to prevent the decline of our mental health and potentially the fall of Homo Sapiens. Without our fully functioning brains humanity will neither have the insight nor cooperation to face and resolve the challenges we face with a growing population, reducing food supply, increasing pollution, climate changes and ever-increasing energy demands.

Food for the Brain is a non-for-profit educational and research charity that offers a free Cognitive Function Test and assesses your Dementia Risk Index to be able to advise you on how to dementia-proof your diet and lifestyle.

By completing the Cognitive Function Test you are joining our grassroots research initiative to find out what really works for preventing cognitive decline. We share our ongoing research results with you to help you make brain-friendly choices.

Please support our research by becoming a Friend of Food for the Brain.


References

[1] https://www.astrobio.net/news-exclusive/how-earths-orbital-shift-shaped-the-sahara/; see also https://phys.org/news/2019-01-sahara-swung-lush-conditions-years.html; see also https://www.ncdc.noaa.gov/abrupt-climate-change/End%20of%20the%20African%20Humid%20Period

[2] https://en.wikipedia.org/wiki/Younger_Dryas_impact_hypothesis

[3] https://www.nature.com/news/how-china-is-rewriting-the-book-on-human-origins-1.20231

[4] https://www.youtube.com/watch?v=t9Zjd0TIHsY

[5] K. Hardy et al., ‘The importance of dietary carbohydrate in human evolution’, Quarterly Review of Biology(2015), vol 90(3):251–268.

[6] https://www.discovermagazine.com/planet-earth/the-human-brain-has-been-getting-smaller-since-the-stone-age

Ogundipe E, Tusor N, Wang Y, Johnson MR, Edwards AD, Crawford MA.

Prostaglandins Leukot Essent Fatty Acids. 2018 Nov;138:6-13. doi: 10.1016/j.plefa.2018.09.001. Epub 2018 Sep 21.

PMID:

30392581

Further info

Post-Viral Chronic Fatigue and Mental Health; How to prevent long-term symptoms of viral infections

Estimated reading time: 9 mins

Chronic fatigue syndrome (CFS) is a debilitating condition that is otherwise known as myalgic encephalomyelitis (ME). Due to the diverse set of seemingly unrelated symptoms that people with this condition present with, it is commonly misdiagnosed and can often be confused with other conditions such as depression. 

Typical symptoms of CFS can be: 

  • Sleep problems
  • Muscle and joint pain
  • Headaches
  • Memory and concentration problems
  • Flu-like symptoms
  • Feeling dizzy or nauseous
  • Low mood

A mysterious illness 

CFS has long been stigmatised and ignored by many doctors due to its mysterious aetiology, often leaving many physicians baffled. This has commonly led to doctors concluding that it is purely a psychiatric illness, rather than a disease of some kind. Sadly, this means that many patients go through years of seeing various doctors before they get a proper diagnosis. 

According to the National Institutes of Health, CFS impacts 15 million to 30 million people worldwide, and leaves 75% of those affected unable to work and 25% homebound or bedridden. Although the aetiology of CFS is unclear, the condition commonly arises following a viral illness, in particular Epstein-Barr virus, herpes and mononucleosis. Since the coronavirus outbreak, there has been a large number of reports of people suffering with long-term symptoms that are akin to those of CFS. This has led to a new line of research opening, to examine the biochemical mechanisms that are leading to symptoms, such as debilitating fatigue, low mood and brain fog, headaches and more in those who have been infected with COVID-19.

A new angle to understanding COVID-19?

According to a report1 published by the Centers of Disease Control and Prevention, more than a third of those who have tested positive for COVID-19 and have symptoms don’t feel like they’re fully recovered, even weeks and months later. Why might this be occurring at such alarming rates? Some researchers, such as Mady Hornig, Immunologist at Colombia University, have proposed that this may be due to inflammation levels going haywire in the body. COVID-19 patients exhibit abnormally high levels of inflammatory molecules2, such as certain cytokines like interferon gamma, which are coincidentally the same inflammation driving molecules that are chronically present in CFS patients. This overactivation of the immune system, which has frequently been labelled the ‘cytokine storm’ in the acute phase of COVID-19, may be what is leading to long-term problems.  

Neurovirologists such as Avindra Nath, at the National Institute of Neurological Disorders and Stroke, believe that there should be more attention placed on the long term risks of COVID-19. Nath purported, in an article published in The Scientist, that viruses can seek long-term refuge in organs to hide from the immune system, which can essentially cause a constant trickling of virus particles to escape into the bloodstream leading to a chronic trigger of inflammation. However, the most obvious mechanism by which viruses can cause symptoms related to CFS is autoimmunity. Nath explains how during the acute phase of a viral infection, the body’s immune system can mistake its own proteins with viral proteins, due to an overactivation of inflammation. This, over time, can lead to mitochondrial dysfunction

A defect in the batteries of our cells?

The mitochondria are the battery-like organelles of our cells, which play an important role in a wide range of physiological processes, such as creating APT (the energy currency of our body), as well as neurotransmitter synthesis, production of insulin, iron metabolism, heat production and many more. Damage to the mitochondria can therefore have a global effect on the body, and many chronic diseases such as diabetes, psychiatric conditions and heart disease, are related to poor mitochondrial function. A key example is in the lack of ATP production that can occur in mitochondrial dysfunction – without enough ATP, we begin to experience symptoms of overall malaise, exhaustion, muscle pain, brain fog and low mood. A chronic inflammatory response that can be triggered by acute viral infections, can literally wear down the mitochondria, altering the metabolism and functioning of cells. This can have a far-reaching impact on our body and even lead to problems in normal bodily functions such as sleep. 

An example of this was seen in a case-controlled study3 carried out in 2011 and published in BMC Neurology, which looked at 22 healthcare workers who had been infected in 2003 with SARS-CoV-1 and were left with chronic exhaustion, musculoskeletal pain and sleep disturbances. After performing EEGs (electroencephalogram) on the study participants, they found elevated levels of alpha EEG anomaly and apnea. The alpha-EEG anomaly has been found to interrupt normal restorative aspects of sleep and many studies4 have identified this anomaly as a consistent feature in patients with fibromyalgia, a condition that leads to similar symptoms to CFS. 

The best offence is a good defence 

As the well-known adage goes, ‘the best offence is a good defence’ – the most important thing we can do to protect ourselves from the negative impact of viral infections like COVID-19, as well as prevent potential long term effects, is to optimise our health via nutrition and lifestyle approaches. A key trigger for mitochondrial impairment is oxidative stress5, caused by the following factors:

  • High blood sugar levels/insulin resistance
  • Consumption of inflammatory foods 
  • Chronic stress 
  • Alcohol
  • Cigarette smoking 

Oxidative stress is a term used to describe the impact that reactive oxygen species (ROS) can have on our health, which are chemically reactive unstable molecules that contain oxygen. These molecules scavenge electrons from other molecules, leaving a trail of disruption called free radical damage.  It is well known that under normal conditions, our bodies maintain a healthy balance between ROS and antioxidants, which are molecules that can donate electrons without becoming ‘unstable’ themselves and are therefore able to halt free radical damage. 

Having chronically high blood sugar levels, drinking too much alcohol, smoking, eating too many processed foods and chronic stress, are a recipe for free radical damage and therefore mitochondrial dysfunction. Here are some simple dietary changes to prevent this from happening:

  • Avoid sugar, in all its forms

Sugar can come in many forms, which is why it’s important to read ingredient labels. Food manufacturers often try to sneak sugar in by using other types of sweeteners such as dextrose, maltodextrin, syrups, fructose, sucrose, high-fructose corn syrup, agave, fruit concentrates and honey. Avoid products that contain any added sugars in them, as well as using sugar at home in foods and drinks.

  • Prioritise protein, fibre and healthy fats

To help avoid chronically high blood sugar levels, it’s important to base your diet on wholefoods rich in proteins, fibre and healthy fats. Protein can be found in meats, poultry, fish, eggs and pulses and healthy fats in oily fishes, nuts and seeds, coconut (and its oil), extra virgin olive oil and avocado (and its oil). Aiming for 50g of fibre a day is also incredibly important to help balance blood sugar levels. This means eating various types of vegetables throughout the day in your main meals. You can do this by aiming to dedicate half of your plate to a variety of vegetables at lunch and dinner.

  • Avoid processed foods

Processed, ready-made meals, often contain ingredients that can be detrimental to our health if eaten too often. Hydrogenated oils, sugars and additives feature frequently in packaged foods, which can trigger oxidative stress and can have a negative impact on mitochondrial health. Focus on whole foods and cooking from scratch as much as possible, so that you have control over what’s going into your meals. 

  • Eat a rainbow

The pigments in plants that cause them to have vibrant colours, such as the red in tomatoes, orange in carrots and sweet potatoes and greens in spinach and kale, are rich in antioxidants like polyphenols and flavonoids. These molecules scavenge free radicals from the body’s cells and help mop up any damage left by them. Try to vary your vegetable intake so that you make sure you’re benefitting from a wide variety of antioxidants. 

Nutrients and enzymes to support mitochondrial health

Aside from the above dietary changes, there are a few nutrients and enzymes that have been well researched in the context of supporting mitochondrial function.

  • Enzyme CoQ10

CoQ10 is an important endogenous antioxidant and enzyme that is produced by the body, which plays an important role in something called the electron transport chain, an important process that occurs in the mitochondria, which triggers the production of ATP or energy in simpler terms. CoQ10 is something that is created inside the body, however, we can get small amounts directly from external sources such as our diet. Foods such as organ meats and oily fish have been shown to contain some CoQ10. In addition, deficiencies in cofactor nutrients such as B2, B3 and vitamin E have been shown to play a role in CoQ10 deficiency, as well as the use of statin medication6

  • L-carnitine

Carnitine is an amino acid that’s synthesised from dietary sources of lysine and methionine, also amino acids. It is responsible for the transport of long-chain fatty acids into the mitochondria to be oxidised and used to create ATP. In previous studies, patients with CFS have displayed significantly lower levels of acetyl-L-carnitine, total carnitine, and free carnitine; and those with the lowest levels have shown the worst functional capacity 7. Whilst carnitine deficiency is rare, those on long term restrictive diets, as well as those with poor liver function may have issues synthesising carnitine. Lysine and methionine are widely found in many foods such as meats, poultry, eggs, fish, as well as in nuts and seeds, wholegrains such as oats, brown rice, and finally, in pulses.  

  • Alpha lipoic acid

Alpha lipoic is an important antioxidant that plays an essential role in supporting mitochondrial enzymes involved in glucose metabolism and energy production. In particular, Alpha lipoic acid has been shown to prevent damage caused to the mitochondria by increased levels of a substance called nitrous oxide (NO) in the body. Whilst NO is essential for blood vessel health, too much of it can be detrimental to our cells. This often occurs in acute inflammation, such as during the initial stages of an infection. Alpha lipoic acid has been shown to effectively restore mitochondrial enzyme activities inhibited by excess NO, which has a consequent positive impact on ATP production8

Supplementation with these nutrients has been explored in some studies9. However, it is important to work with a nutritional therapist or a nutritionist to make sure you’re taking the right dose and to investigate potential drug-nutrient interactions, for those taking medication. In the meantime, following the above dietary and lifestyle guidelines can have a profound impact on health and mitochondrial function. 

Sign up to our mailing list

Receive educational articles and latest information on events, campaigns and research

References

1.  Tenforde MW, Kim SS, Lindsell CJ, et al. Symptom Duration and Risk Factors for Delayed Return to Usual Health Among Outpatients with COVID-19 in a Multistate Health Care Systems Network — United States, March–June 2020. MMWR Morb Mortal Wkly Rep 2020;69:993-998. DOI: http://dx.doi.org/10.15585/mmwr.mm6930e1external icon  

3.  Moldofsky, H., Patcai, J. Chronic widespread musculoskeletal pain, fatigue, depression and disordered sleep in chronic post-SARS syndrome; a case-controlled study. BMC Neurol 11, 37 (2011). https://doi.org/10.1186/1471-2377-11-37 

4.  A. M. Drewes, Pain and sleep disturbances with special reference to fibromyalgia and rheumatoid arthritis, Rheumatology, Volume 38, Issue 11, November 1999, Pages 1035–1038, https://doi.org/10.1093/rheumatology/38.11.1035

5.  Guo, Chunyan et al. “Oxidative stress, mitochondrial damage and neurodegenerative diseases.” Neural regeneration research vol. 8,21 (2013): 2003-14. doi:10.3969/j.issn.1673-5374.2013.21.009. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4145906/ 

6.  Kristin Filler, Debra Lyon, James Bennett et al, ‘Association of mitochondrial dysfunction and fatigue: A review of the literature’, BBA Clinical, Volume 1, June 2014, Pages 12-23. https://doi.org/10.1016/j.bbacli.2014.04.001

7.  Sanford H. Levy MD, FACP, ABIHM, in Integrative Medicine (Fourth Edition), 2018. https://www.sciencedirect.com/topics/medicine-and-dentistry/carnitine 

8.  Sylvia Hiller, Robert De Kroon, Eric D.Hamlett et al, ‘Alpha-lipoic acid supplementation protects enzymes from damage by nitrosative and oxidative stress’,  Biochimica et Biophysica Acta (BBA) – General Subjects, Volume 1860, Issue 1, Part A, January 2016, Pages 36-45. https://doi.org/10.1016/j.bbagen.2015.09.001 9.  Kristin Filler, Debra Lyon, James Bennett et al, ‘Association of mitochondrial dysfunction and fatigue: A review of the literature’, BBA Clinical, Volume 1, June 2014, Pages 12-23. https://doi.org/10.1016/j.bbacli.2014.04.001

Further info

Early Diagnosis of Alzheimer’s – Amyloid Protein vs Homocysteine Testing

Worldwide 46.8 million people have dementia. In the UK, 1 in 14 people over 65 have Alzheimer’s, the most prevalent form of dementia; and increasingly dementia sufferers are also struggling with other chronic conditions, such as diabetes and depression. Research on new strategies for earlier diagnosis is among the most active areas in Alzheimer’s science. This is as the majority of cases are diagnosed when irreversible brain damage or mental decline has already occurred. 

The amyloid protein test used for earlier diagnosis

Amyloid beta is a protein found in the brain that is involved in the pathophysiology of Alzheimer’s and cognitive decline. This 2019 study found that a blood test to measure amyloid, is 94% accurate in earlier diagnosis of Alzheimer’s disease. This is specifically when in combination with age and genetics (testing positive for the APOE4 gene) as risk factors. Whilst this is a positive development for future considerations in treating Alzheimer’s, there has been no successful amyloid-lowering drug trial to date.

In addition, it is well-known that the damaging clumps of amyloid protein can begin to develop and lead to brain atrophy decades before an individual even begins to experience symptoms of memory loss and cognitive function, so unless testing is given earlier on in life as a preventative measure, an amyloid-lowering drug when the damage has already been caused may not be very effective. 

Amyloid, a protective mechanism?

To date, the majority of research into the treatment of Alzheimer’s has been focused on the “amyloid hypothesis”. In 2018 alone, the US National Institutes of Health spent $1.9 billion on Alzheimer’s research. However, according to this study, there has been a 99% failure rate in the development of drugs that target this disease. Questions about the reliability of the amyloid protein hypothesis are being posed by scientists, after various studies discovering how amyloid plaques actually function as a type of sticky defence against bacterial invasion, lead to a different hypothesis. In one significant study, where mice that were genetically engineered to make Alzheimer’s proteins had bacteria injected into their brains, researchers found that amyloid plaques engulfed bacterial cells overnight, suggesting a protective mechanism.  

Why we cannot ignore the link between high homocysteine levels and Alzheimer’s 

According to a Consensus Statement released by an international panel of experts on dementia: Research has shown, time and time again, that having high homocysteine (Hcy) levels, and low folic acid and B12 levels in the blood correlate with an increased risk for Alzheimer’s disease.

An earlier review written by Professor David Smith in 2008, highlighted that there are a total of ‘seventy-seven cross-sectional studies on more than 34,000 subjects and 33 prospective studies on more than 12,000 subjects’…that…‘have shown associations between cognitive deficit or dementia and homocysteine and/or B vitamins.’ 

In a meta-analysis published in 2014 by BMC Public Health, raised homocysteine was considered to be one of the three strongest risk factors, along with low education and decreased physical activity.

Two further trials have clearly shown that lowering homocysteine, through the supplementation of B vitamins, reduced age-related cognitive decline in normal ageing and also slowed down both brain atrophy and cognitive decline in people with Mild Cognitive Impairment.

The efficacy of B vitamins to prevent the progression of Alzheimer’s.

In one study, 270 people over 70 with Mild Cognitive Impairment were recruited to trial the efficacy of B vitamins to prevent the progression of Alzheimer’s. MRI scans were done at recruitment and half the participants were given high doses of three B vitamins (B6, B9 and B12), half took a placebo tablet.

After 2 years, participants were scanned again and scientists found that the rate of brain atrophy in those treated with the B vitamins was on average 30% slower than those taking placebo. In addition, in those that had the highest homocysteine levels at baseline, the effect of B vitamin treatment was even more potent, helping to slow down brain atrophy by 53%. This result fits all the criteria for a disease-modifying treatment and so is especially important. There is, therefore, ample evidence to propose that lowering homocysteine by giving appropriate supplemental levels of homocysteine lowering nutrients, including B6, B12 and folic acid, would reduce risk.

In a commission published by the Lancet, 9 modifiable risk factors were outlined, clearly excluding homocysteine:  

Mid-life hearing loss – responsible for 9% of the risk Failing to complete secondary education – 8% Smoking – 5% Failing to seek early treatment for depression – 4% Physical inactivity – 3% Social isolation – 2% High blood pressure – 2%Obesity – 1% Type 2 diabetes – 1% 

Ignoring homocysteine is surprising, since a meta-analysis from the National Institute of Aging estimated that about 22% of Alzheimer’s disease may be caused by raised levels of homocysteine.

Integrating homocysteine testing and inexpensive B vitamin-based treatment into the heart of mainstream health strategies on Alzheimer’s could potentially play a vital role in the prevention of dementia, if caught early enough.

Every 3 seconds, someone in the world develops dementia and the International Alzheimer’s Society estimates that by 2050 there will be 131.5 million people living with this disease. This is not something we can ignore.

Sign up to our mailing list

Receive educational articles and latest information on events, campaigns and research

Further info